
Research article · 2024 · Full text
International Journal of Advanced Chemistry ResearchUnderstanding the biochemical basis of Alzheimer's disease: A clinical chemistry approach
Volume 6(2) · Pages 114–124 · DOI: 10.33545/26646781.2024.v6.i2b.234 ↗
Research areasComputational Drug Discovery MethodsCholinesterase and Neurodegenerative Diseases
Abstract
Author-writtenAlzheimer's disease (AD) is a complex neurodegenerative disorder characterized by progressive cognitive decline and memory loss. This study explores the biochemical underpinnings of AD through a clinical chemistry lens, focusing on the alterations in key biomolecules and metabolic pathways associated with the disease. We examine the roles of amyloid-beta peptides, tau protein hyperphosphorylation, and oxidative stress in neuronal damage, alongside their implications for early diagnosis and therapeutic interventions. By analyzing biomarkers in cerebrospinal fluid and plasma, we aim to enhance the understanding of disease mechanisms and improve diagnostic accuracy. Additionally, this approach highlights the potential of targeted therapies that address specific biochemical pathways, paving the way for more effective treatment strategies. Through a comprehensive review of current literature and ongoing research, this study seeks to contribute to the growing body of knowledge surrounding AD and its biochemical foundations, ultimately aiming to facilitate advancements in clinical practice and patient care.
Summary
Source-checkedPlain-language reading of the full paper, prepared with AI and checked against the text. Each point links to the authors' own words.
Why it matters
- Alzheimer's Disease (AD) is a complex neurodegenerative condition that leads to a progressive loss of memory and cognitive function. View evidence ↗
- AD is the primary cause of dementia, and its prevalence increases with age; it is projected to be the fourth leading cause of death by 2030. View evidence ↗
- Traditional clinical diagnosis of AD is relatively unreliable, with a false positive rate estimated between 10% and 20%. View evidence ↗
The question
- The study aims to investigate the biochemical foundations of AD, specifically focusing on metabolic pathways and changes in key biomolecules using a clinical chemistry approach. View evidence ↗
What they did
- The authors conducted a comprehensive review of existing literature and ongoing research to synthesize the biochemical basis of AD. View evidence ↗
- The review focuses on the analysis of biomarkers found in plasma and cerebrospinal fluid (CSF) to better understand disease mechanisms. View evidence ↗
What they found
- Aβ amyloid, derived from the abnormal cleavage of Amyloid Precursor Protein (APP), is the primary protein component of brain lesions in AD. View evidence ↗
- Neurofibrillary tangles, a hallmark of AD, are primarily composed of fragments of the tau protein. View evidence ↗
- In AD patients, there is a marked decrease in the levels of Aβ peptide and the Aβ42/Aβ40 ratio in the cerebrospinal fluid, likely due to the peptide aggregating and depositing in the brain. View evidence ↗
- The APOE gene is the most significant genetic factor in human neurodegenerative diseases, playing a key role in the metabolism and destruction of amyloid. View evidence ↗
- A major challenge in clinical chemistry for AD is developing methods that can specifically detect target proteins amidst the high abundance of other proteins in the blood. View evidence ↗
- Pharmacological agents designed to bind soluble Aβ showed limited therapeutic effects when administered during advanced stages of AD. View evidence ↗
- Microtubule-stabilizing drugs can reduce the quantity of neurofibrillary tangles by redistributing abnormally phosphorylated tau back to the microtubules. View evidence ↗
What it means
- The authors conclude that a deep understanding of the biochemical basis of AD is essential for improving both diagnostic accuracy and treatment outcomes. View evidence ↗
Visual summary
1 visualsIllustrations explain the paper; they do not show study data.
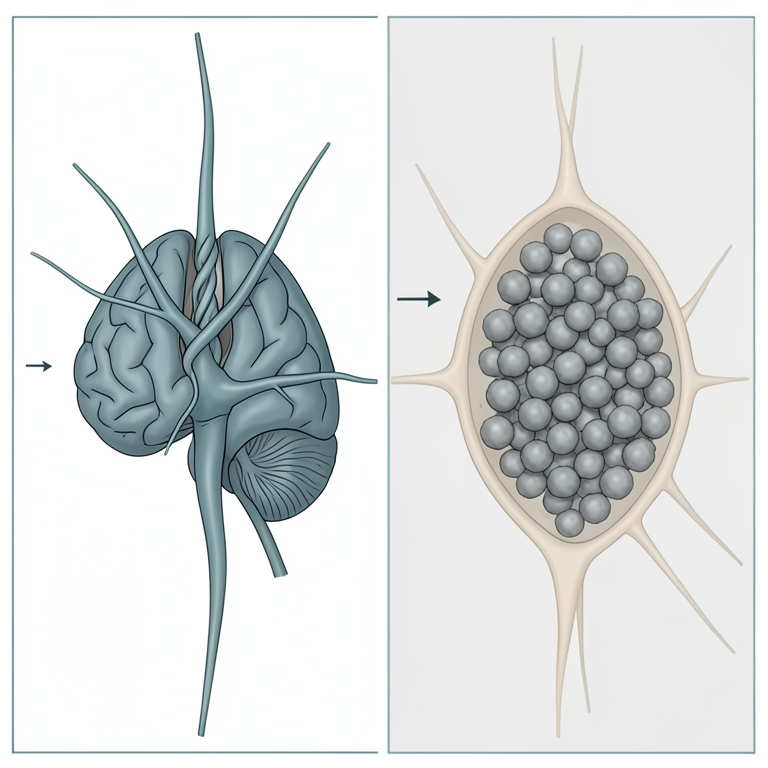
Pathological Hallmarks of AD
AI-generated conceptual illustration (human brain neurons and extracellular space). It explains the idea and does not show study data.
View source evidence ↗Introduction
Alzheimer's Disease (AD) is currently ranked as the sixth leading cause of death in the United States. To date, there are no treatments that can stop or reverse its progression. The biochemical understanding of the triggering and negative changes to the biochemical homeostasis of the body was elucidated after a surprising autopsy finding, where the brain of a woman who had suffered from known disturbances of cerebral function (among them, confusion, alterations of short-term memory, disorientation, hallucinations, and progressive psychiatric symptoms) was examined during autopsy, and it was found to have neurofibrillary tangles, not taken into consideration by the examiner. These tangles were not found in normal age-affected or psychiatric aged individuals. After this discovery, researchers widely studied these entities in the brain. From a biochemical approach, quite some time passed before the biochemical enigma surrounding the onset and development of AD was unraveled (Curtin et al., 2023; Heron., 2021; Liang et al., 2021) [19,34,46] .
Epidemiology and impact
Alzheimer's disease is a progressive and neurodegenerative disorder that significantly affects the cognitive and functional performance of patients. Over the years, the prevalence of dementia has increased strikingly, burdening the quality of life, healthcare services, and the labor market. Dementia is mainly caused by Alzheimer's disease, with a prevalence that increases with advancing age, in such a way that it was estimated to become the fourth leading cause of fatality by 2030. The healthcare status of patients, as well as the subsequent need for caregivers, highlights the socioeconomic consequences of the demographic changes that are expected to evolve. Consequently, research in this field has made significant efforts in the study and treatment of such impairments (Abubakar et al., 2022; Rahman et al., 2024; Biochemical assays have become valuable tools in the assessment of cognition and the functional performance of dementia patients. In addition, they also provide meaningful diagnostic information through the identification and recognition of pathologic hallmarks that are specific to neurodegenerative diseases such as Alzheimer's disease. With various biomarkers available, ranging from the classic diagnostic criteria to the most developed and recent advances in life-imaging technologies and in the field of proteomics, there is hope that further investigations will push towards the discovery of efficient and potential treatments for this overwhelming noncommunicable disease of the brain (Chen et al., 2022; Abubakar et al., 2022; Rahman et al., 2024) [2,17,65] .
Clinical presentation and diagnosis
Alzheimer's disease, the most frequent cause of dementia, is a progressive and fatal neurodegenerative disorder whose onset generally occurs in late adulthood. Alzheimer's disease is characterized clinically by a gradual decline in memory and judgment over a period lasting from several months to many years. Some deficits in language, logical reasoning, problem-solving capabilities, and general intellectual function are present, indicating deterioration from a previous higher level of function (Litvinenko & Lobzin., 2022) [48] . These manifestations result from the progressive and characteristic degenerative changes in the brains of Alzheimer's disease patients. The neurochemical changes of Alzheimer's disease include the accumulation of neurofibrillary tangles, deposition of amyloid plaques, loss of synapses, and presence of dystrophic neuritis in the neuropil. These pathologies appear to correlate with neuronal loss and cognitive impairments (Litvinenko & Lobzin., 2022) [48] . The development of the clinical diagnostic criteria for Alzheimer's disease has been approached only from the patient's clinical manifestations and the patient's progression to dementia. The primary diagnosis of Alzheimer's disease is, thus, based on the exclusion of other types of dementia, although certain neuroimaging and neuropsychological tests help to establish the diagnosis. Such clinical diagnosis is relatively unreliable, generating a false positive diagnosis rate of approximately 10-20 percent. As progress in molecular and cellular biology expands, especially in the fields of functional brain imaging, genetics, and clinical laboratory tests, it has become possible to diagnose the early and preclinical states of Alzheimer's disease from neuropsychological and laboratory assessments (Litvinenko & Lobzin., 2022) [48] . Clearly, as more sensitive and specific diagnostic methods are developed, the earlier the detection of disease onset can be made. In the future, pathologic changes will be detected well before the emergence of cognitive deficits through advances in clinical chemistry, providing an index of ongoing tissue damage that will lead to earlier diagnosis and therapy, enhancing the onset of dementia. Defining the preclinical stage of the disease may also raise the possibility of early therapeutic intervention, which would likely be the most significant opportunity for the prevention of neuropathological changes (Crestini et [18,48,50,61] .
Neurobiology of Alzheimer's disease
Alzheimer's Disease (AD) is the most frequent cause of dementia in elderly people. AD patients rely primarily upon the post-mortem neuropathological examination. Morphological findings include the accumulation of neurofibrillary tangles, extracellular amyloid plaques, and loss of neurons and synapses, particularly in the association areas of the brain, namely the neocortex, entorhinal cortex, and hippocampus. The main proteinaceous component of both types of brain lesions is Aβ amyloid, a peptide derived from the Amyloid Precursor Protein (APP) through abnormal proteolytic cleavage (Sánchez-Juan et al., 2024; Henriques et al., 2020) [15,32] . A fragment of the tau protein is the main component of neurofibrillary tangles. Familial cases of AD occur in individuals who have a mutated gene in one of three proteins: amyloid precursor protein and presenilin 1 or 2. In 95% of AD cases, the disease has a later age of onset and is called sporadic AD. Other factors, such as age, sex, educational level, midlife hypertension, hypercholesterolemia, obesity, diabetes, lack of exercise, and smoking, may also contribute to increasing the risk of sporadic AD. AD is believed to be a complex and multifactorial process (Sánchez-Juan et al., 2024; Henriques et al., 2020) [15,32] . In the extracellular space, Aβ may exert toxic effects, like abnormal activities at various phases over time, including high homotypic and endoplasmic reticulum activities, and may become insoluble fibrils. Aβ can be present in different lengths (39-43 amino acids) and in two different alloforms: Aβ1-40 and Aβ1-42. Among people diagnosed with AD, a pathologic increase in Aβ1-42 and a change in certain factors have been noted. It has been hypothesized that calcium dysregulation might contribute to synaptic dysfunction in AD and that tau might be the protein responsible for abnormal calcium homeostasis. Synaptic Ca 2+ dyshomeostasis could precede neuronal Ca 2+ dyshomeostasis and contribute to the pathogenesis of AD. Metabolomics may, in the future, play a role in disentangling still unresolved causative and associated metabolic alterations in AD pathogenesis (King et [15,40,32] .
Amyloid beta and tau proteins
Amyloid beta and tau proteins are central in Alzheimer's disease pathogenesis, and they are, perhaps, the most focused constructs for Alzheimer's disease owing to the amyloid cascade hypothesis. This theory proposes that the accumulation of amyloid beta in its monomeric, oligomeric, and/or fibrillar forms in the brain culminates in a series of events leading to neuroinflammation and the ultimate demise of neurons over time, causing Alzheimer's disease in affected patients (Muralidar et al., 2020; Ashrafian et al., 2021) [55,27] . Moreover, the formation of insoluble intraneuronal neurofibrillary tangles derived from misfolded tau also independently leads to neuronal death and aggravates the progression of amyloid-beta-driven neuropathology in the brain. The amyloid beta and tau hypothesis forms the basis for current research involving the search for targeted therapies for Alzheimer's disease through diverse biochemical alterations in the life cycle and roles of these proteins in the early diagnosis, prevention, and treatment of Alzheimer's disease (Muralidar et al., 2020; Ashrafian et al., 2021) [55,27] . Amyloid beta represents a family of peptides with molecular weights of 4-5 kDa that derive from the amyloid beta protein precursor through varying cleavage pathways. The peptides with the most importance for Alzheimer's disease are short amino acid sequences containing 40 amino acids and 42 amino acids. Even though the 40 amino acid form is the most abundant form of the amyloid beta peptide and is also responsible, in part, for amyloid plaque formation in the brain, the 42 amino acid form, which is more hydrophobic, tends to aggregate more speedily, forms oligomers more readily than the 40 amino acid form, and is specifically implicated in the early stages of the amyloid cascade leading to the formation of the amyloid plaques that are characteristic of Alzheimer's disease (Muralidar et al., 2020; Ashrafian et al., 2021) [55,27] . Tau represents a family of neuronal microtubule-binding proteins in the large class of microtubule-associated proteins. These are encoded by a single gene expressed mainly by neurons in the human brain and perform functions such as microtubule stabilization, neuritic transport, synapse modulation, and seeding regulation. Such is the importance of these functions that most neurodegenerative diseases are linked to the misfolding of these canonical proteins (Zhang et al., 2022; Muralidar et al., 2020; Ashrafian et al., 2021) [15,55,27] .
Neuro-inflammation and microglia activation
Microglia play a critical role in the inflammatory process in response to Aβ aggregation and are strategically placed around each plaque. They were discovered in 1919 by Pio Del Rio Hortega, who observed them "self-duplicating" in a rodent brain. It was M. J. Bendikt who first used the term "microglia" in 1924. Although still a matter of discussion, the primary source of these cells has been traced back to the yolk sac precursor cells, which are mainly macrophages, with monocytes also being in the periphery of neurovascular units resulting from differentiation between macrophages and monocytes, known as exogenous origins (Du et al., 2021; Shi et al., 2021) [71] . They are essential for maintaining normal brain function, such as providing complex support and neurochemical protection by removing apoptotic neurons, pruning redundant synapses, and releasing neurotrophic factors. They are not resting cells; they have been found to be in an active surveillance state even in the absence of acute inflammation (Du et al., 2021; Shi et al., 2021) [71] . In addition to their role in synaptic connectivity, phagocytosis of cellular debris, and abnormal synaptic patterning, the role of microglia as a support for neurons led to the classic division of these cells into M1 phenotype (classically activated, pro-inflammatory promoting) and the M2 phenotype (alternative activation, anti-inflammatory, and repair promotion). Disturbance of the microglial inflammatory response can sustain the cycle of inflammation and provide a considerable contribution to the progression of AD, mainly by influencing the process of Aβ aggregation and its clearance (Guan et [27,13,71] .
Biochemical markers in Alzheimer's disease
Neurodegenerative diseases include a number of disorders that are common causes of dementia, comprising significant clinical issues in aging populations. One of the most devastating neurodegenerative diseases of late life is Alzheimer's disease. This disease and other related conditions are believed to occur as a result of extracellular deposition of amyloid beta-peptide in parenchymal plaques and cerebral vessels. The core components of the senile plaques are either the 42-residue form or the truncated 40residue form (Inyushin et al., 2020) [35] .
The Cerebrospinal Fluid (CSF) levels of the constituents of amyloidogenic processing have been evaluated as potential markers of the degree of cerebral beta-amyloidosis in the neuropathological scenario of Alzheimer's disease. CSF levels of its production or their catabolic products could potentially reflect and represent the plaque load and be related to the progression of the disease. A low CSF concentration of the peptide Aß1-42 or the 1-42/Aß1-40 ratio appears to be putative markers for prodromal Alzheimer's disease. These biomarkers are released into the extracellular space and eventually cleared by proteolytic proteases, insulin-degrading enzyme, and neprilysin, being the most important. Any alteration in the production or removal/inactivation of these peptides can have significant pathogenic implications. In Alzheimer's disease epidemiology, plasma levels of Aß have been found to be inversely associated with the risk of AD. In accordance with the "Aß clearance theory," the positive role of peripheral Aß levels in Aß brain metabolism is supported by the fact that increasing peripheral Aß diminishes the Aß deposition in the brains. This would suggest that enhancing Aß transport across the blood-brain barrier into the peripheral compartments may have a therapeutic impact of diminishing cerebral Aß load. Consequently, Aß is becoming a potential biomarker for the diagnosis (Abbas. 2021; Gupta et al., 2022; Inyushin et al., 2020) [1,28,35] .
Cerebrospinal fluid biomarkers
Cerebrospinal Fluid (CSF) has shown potential for Alzheimer's Disease (AD) research for two principal reasons. First, due to the anatomical and functional characteristics of the Blood-Brain Barrier (BBB) and the production of CSF in the choroid plexus, the biochemical properties of CSF closely reflect the metabolism of the central nervous system. Second, lumbar puncture for the extraction of CSF is a safe and universally accepted method in clinical routine, and it is a straightforward procedure with generally accepted contraindications. Despite being relatively safe and minimally invasive, lumbar puncture is an expensive, laborious, and therefore poorly accepted procedure. This limits the accessibility of many patients at baseline examination and follow-up (Al-Mekhlafi et al., 2021; Kwon et al., 2022; Blomqvist et al., 2021) [5,10,42] . Although AD pathogenesis is not completely understood, two proteins seem to be considered early markers of the disease due to their important role in the pathologic cascade of AD. Amyloid β-peptide (Aβ) and total tau protein (t-tau) are biomarkers that have shown potential for early diagnosis, as have their ratios due to the patterns of changes in Aβ42, Aβ40, and tau levels. The amyloid cascade hypothesis states that AD is caused by the accumulation and deposition of Aβ peptide in the brain. The levels of this peptide in the CSF present a marked decrease, while the same occurs in the Aβ42/Aβ40 ratio of AD patients, most likely as a consequence of its aggregation and deposition. Tau protein has important functions in neuronal morphogenesis. Due to its hyperphosphorylation, it is involved in cytoskeleton dysfunction and, in severe cases, leads to the formation of neurofibrillary tangles (Rasmussen et [5,10,42] .
Blood-based biomarkers
Considering the use of CSF-based biomarkers in early diagnosis, there has been an increasing interest in the search for blood-based alternative biomarkers that would enable the diagnosis of Alzheimer's disease. The premise behind such a search is that the blood-brain barrier might be permeable to blood-based markers and that, as a result, proteins and other markers from the brain might be found in the blood (Padala & Newhouse., 2023; Feng et al., 2021; Lista et al., 2024) [57,47,21] . Attempts to study cells of the nervous system present in blood have given rise to the area of research known today as neurological series, but the value of the study of cellular pathology for Alzheimer's disease is still under investigation. MicroRNAs are among the different biomarkers that have undergone extensive research. Although the evidence is promising, no definitive blood-based biomarker has emerged to date. With the above limitations in mind, combination analyses have also been under investigation, as have proteomic studies using multiple biomarker groups ( [57,21,47] . It is suspected that a considerable percentage of people who are diagnosed with Alzheimer's disease do not have the disease and may be suffering from other forms of dementia or normal aging. As other markers do not exist, some of the failures in clinical trials can be attributed to misdiagnosis based on the clinical criteria in use. Although other conditions need to be considered, the presence of some plasma-based biomarkers might help in differentiating some of the differentials from Alzheimer's disease. Not potentially having to perform a diagnosis expectation of 6-7 years from the clinical criteria-based current diagnosis, Alzheimer's disease brain levels of certain proteins have been linked with the plasma of individuals. For certain brain-specific proteins at low levels, antibodies made in the central nervous system are present at higher levels. Some of these very important proteins have shown positive results in inflammatory process biomarker studies. [51,57,21,47] .
Role of genetics in Alzheimer's disease
"If you have seen one Alzheimer patient, you have seen one Alzheimer patient." The reason why Alzheimer's disease has long been recognized as a diverse syndrome has become clearer in recent years as many inherited forms of the disease have been elucidated. In this review, we are examining the latest understanding of these forms of the disease. A number of different mutations have been described that are associated with early Aβ amyloid creation. AD mutations are seen to alter the production of the protein from which Aβ amyloid is created and mutations within the gene or the presenilin complex that is associated with early catalysis of the critical first stage of Aβ amyloid creation. Thus, AD inherits a number of metabolic associations that perturbed APP grading can create. Immunotherapy against Aβ amyloid, targeting the amyloid cascade, was the first direct therapeutic route suggested for familial Alzheimer's disease, though this proved a difficult strategy to handle (Frisoni et al., 2022) [23] . A number of antibody fragments, or whole antibodies, that attack Aβ amyloid have, therefore, been examined. Rather than immunotherapy, Aβ amyloid oligomer blockade could prove a more straightforward strategy. Small molecules have been developed and experimentally examined for their capability of blocking the clustering association of individual Aβ amyloid units to create oligomers. This represents a conformational disease approach to drug discovery. Oligomer inhibitors offer new hope for drug discovery both for treating inherited disease and perhaps for wider application (Frisoni et al., 2022) [23] .
APOE gene
The identification of a biological marker that clarifies the role of a genetic or epidemiologic factor in the pathophysiology of neurodegenerative diseases such as Alzheimer's, which can result in cognitive decline and eventual death, would have a wide range of clinical applications. It could be used for the construction of predictive models of disease, or to delay or diminish the risk of its onset. It could also be used in preclinical treatment, in the determination of prognosis, and in the early discovery of neurodegenerative diseases. One of the methods currently used to delay and decrease the risk of neurodegenerative diseases is genetic manipulation. For example, modification of genes that regulate the development of the illness, or phytochemicals, which aim to slow the course of the disease, make the postponement and weakening of the onset of the disease possible (Parhizkar & Holtzman., 2022; Goldman et al., 2021) [59,26] . The most important gene that participates in neurodegenerative diseases in the human brain is the gene encoding apolipoprotein E (APOE), which is involved in amyloid metabolism and destruction. The APOE gene is also known to influence the age of onset. However, the decision to use APOE allele modulation of some sort is a highly personal decision for an Alzheimer's disease patient. It is clear that Alzheimer's disease has a deep impact on the patients and their families; it is a major source of emotional and financial burden. Patients diagnosed with an APOE3 genotype often exhibit symptoms that mimic typical lateonset Alzheimer's disease, but a diagnosis of Alzheimer's can be made only upon autopsy. However, this is often cold comfort to the family, since patients often die from other causes before Alzheimer's disease can be diagnosed through an autopsy ( [22,27,59,26] .
Other genetic risk factors
Other genetic risk factors: SORL1, PLD3, CD33, ABCA7, and HLADRB5 are among the genetic risk factors reported in recent literature. SORL1, encoding the sortilin receptor, was first linked with late-onset Alzheimer's disease. Recent work has also shown protective SORL1 splice site variants. PLD3 was the first reported Alzheimer's disease riskassociated gene discovered through whole-exome sequencing of multigenerational families expressing Alzheimer's disease, in addition to both genome-wide and targeted association studies, which claimed to have discovered the gene surrounding the coding variant at the protein level. Another group linked it to a haplotype on chromosome 19 within a non-coding region (Chen et al., 2022) [17] . CD33 encodes SIGLEC3, which functions as a sialoglycoprotein and a member of the immunoglobulin superfamily. The SNP in CD33 was first discovered using GWAS. The gene product CD33 is an α2-3sialyltransferase-binding protein that inhibits adhesion and activation of microglia and also shows upregulation during Alzheimer's disease-associated pathology. In the most recent Alzheimer's disease genetics mega-analysis, four new Alzheimer's disease risk loci, including three novel variants, were found to be significantly associated with late-onset Alzheimer's disease. The critical variant discovered in this study of high-interest genes is enriched in the microglial enhancers and associated with gene expression levels in the human brain. It is also closely positioned to the genes that encode other microglial cell-surface molecules. The six genetic risk factors were identified to regulate APOE e4 by integrating Alzheimer's disease susceptibility genes with brain imaging datasets (Barthelson et [17,9] .
Clinical chemistry techniques in Alzheimer's research
A variety of proteins have thus far been implicated in Alzheimer's disease, including the enzymes acetylcholinesterase and butyrylcholinesterase, the glycoprotein lipoprotein-related protein, malectin, amyloid precursor protein, apolipoprotein E, the low-density lipoprotein receptor-related protein, sorting nexin 12, Trem2, and others. The real challenge in clinical chemistry is to use methods that specifically detect any protein of interest over the abundant number of other proteins that are found in blood. In this section, we describe clinical chemistry techniques and how the detection of Alzheimer's disease biomarker proteins could be realized. These methods are based on the logical combination of a target's biochemical characteristic with sophisticated signaling to deliver highly sensitive detection of specific biomarkers (Ganguly et al., 2021) [24] . Alzheimer's disease is a progressive neurodegenerative disease that affects adults over the age of 65 most widely and is characterized by cognitive decline. All the biochemical changes leading to specific symptoms of the disease are not clear, which makes a definitive diagnosis of the disease difficult. The pathogenesis of Alzheimer's disease does not solely involve the key biomarkers of amyloid-beta, phosphorylated tau proteins, an increased cholinergic deficit, and the breakdown of the blood-brain barrier (Ganguly et al., 2021) [24] . Any laboratory approaches based on these markers have produced confounding results so far, and therefore the discovery of alternative markers may enable earlier and more accurate diagnosis of the disease. With the major strengths of biochemical analysis being the ability to perform a complex multilevel analysis of biological fluids with speed along with a cost-effective and straightforward protocol, it is a key technique in AD diagnosis. Specifically, clinical chemistry is widely used to analyze blood, urine, and cerebrospinal fluid, which contain a wealth of information (Muralidar et al., 2020; Rahman & Lendel., 2021 Ganguly et al., 2021) [55,24,66] .
Mass spectrometry
In biological samples, different types of information can be obtained by mass spectrometry techniques, including identification of substances and quantitative analysis. The latter can be obtained using stable isotope labeling. The most mature labeling strategy is the use of stable isotopes such as 2H, 13C, and 15N, which are very useful in the MRM technique, to improve selectivity and to quantify relative levels, or 12C/13C, which allows relative quantification of peptides. Only in cases where identification cannot be performed by MS, the so-called Mass Spectrometry Immunoassays are applied, using immunoenrichment of target peptides and proteins, preserving high sensitivity and suspension chromatography format, in a combined immunoenrichment and purification step (Li and Zhan., 2021; Li et al., 2022; Adnan et al., 2024) [3] . Absolute quantification strategies, made possible thanks to highly stable-isotope-labeled peptides, depend on the availability of commercial equipment. In the absence of commercial equipment, the method can also be built inhouse but has to respond according to different parameters. Data processing remains the most important part, splitting the steps of peptide integration to complex LC/MS analysis into distinct parts, which consist of chromatographical peak detection, summing of integrated signal of each ion transition, and background noise estimation to obtain the limit of detection (Li and Zhan., 2021; Li et al., 2022). The limit of detection, in label-free quantification, is expected by observing that the peptide can be positively detected in a run, and an accurate mass and isotopic distribution inferred. For carbohydrate-derived peptides, very useful tools and information are available, but glycated peptides have remained 'undiscovered' for a long time, as a direct result of the lack of methodology able to avoid suppression of formation of product ions; then glycan spectra and locations were guessed from isotopic distribution, considering database search as the only way. Currently, methods involving protease ion source, which are considered more sensitive than CID, do not reflect the pull of negative charge of extracted ions, reducing suppression of peptide ions and, consequently, increasing the glycosidic bond cleavages, but require a high-energy stepping voltage as well as activation time, because of the energy enhancement required to induce high glycosidic bond cleavages, have been used for glycopeptides, as well as those involving top-down approaches, representing the very first online DC-activated EI in LIT configurations. The mass spectrometer plays an essential role in all applications for the measurement of neuroendocrine peptides and other low molecular weight molecules (Anapindi et al., 2022; Li and Zhan., 2021; Li et al., 2022) [6] .
Enzyme-Linked Immunosorbent Assay (ELISA)
Enzyme-Linked Immunosorbent Assay (ELISA) is a sensitive immunoassay in which an enzyme linked to a specific antiserum or monoclonal antibody is used to detect protein produced by cells during the infection of a host. ELISA is used to detect whole virus particles or virusspecific antigens. In the first type of ELISA, the antigencontaining solution is added to a 96-well polystyrene plate that binds the antigen to the plastic surface. This is followed by the addition of the primary antibody, which is present in the patient's serum and binds to the antigen, the addition of a secondary antibody that has an enzyme linked to it and is specific for the primary antibody, the addition of a substrate of the enzyme that changes color, and measurements of the intensity of the colored product to determine the presence of the antigen. Color intensity is directly proportional to the amount of antigen, which thus provides a direct indication of the presence of the infectious agent (Minic & Zivkovic., 2020) [52] . The second type of ELISA is known as a sandwich ELISA and is often used to detect human insulin. The insulin is captured in a well by a mixture of a specific anti-insulin antibody that is pre-absorbed to the walls of the plastic wells. A second enzyme-labeled antibody that recognizes a different insulin epitope is then added to the well and is allowed to form an antigen-antibody-antibody-enzyme complex with the trapped polypeptide. Following substrate addition, the color change is fluorimetrically measured. ELISA can be done quantitatively by measuring the intensity of the color signal to estimate the amount of antigen in the sample being tested. The test is sensitive enough to detect nanograms of antigen per milliliter of sample, qualifying it as a highly sensitive test. Small test kits are available for a wide variety of antigens, which are detected rapidly at low cost (Ito et [52,62,37] .
Therapeutic approaches targeting biochemical pathways
Several strategies have been developed to stave off or alleviate the symptoms of Alzheimer's disease by modulating the cholinergic system, the glutamatergic system, the calcineurin pathway, the serotonergic system, the inflammatory system, the amyloid peptide, or the tau protein pathways. In this review, we focus on the strategies that are directly linked to a biochemical alteration or that may mechanically interfere in the diagnosis of the disease since they are the strategies that clinical pathology can influence. No matter the kind of strategy, any kind of intervention will imply taking into account the variability in the patient's responses to treatment, which results from differences in metabolic activity or the pharmacokinetic or pharmacodynamic variability of drugs. Thus, in the therapeutic approach, the possible role of the AD-modifier risk genes involved in the efficacy of treatments will also be evaluated. In spite of the great effort that has been made in understanding the biochemical and molecular basis of Alzheimer's disease and the generation of technology to design strategies able to palliate this disease, the exact causes and molecular bases responsible for AD have not been elucidated. Therefore, there are no efficient treatments to prevent the development and progression of the disease, and definitive diagnostic tools are also not available. Various studies performed in humans or on animal models emphasize the importance of the integrity of the cellular environment in the initiation of Alzheimer's disease and in these initial functions in AD progression. The challenge in effectively proposing treatments in AD relies on the fact that targeting a single pathway may subsequently alter rather than ameliorate the disease, as a consequence of the significant neurobiological changes in AD brains. Nevertheless, several strategies have been developed by modulating the cholinergic system, the glutamatergic system, the calcineurin pathway, the serotonergic system, the inflammatory system, the amyloid peptide, or the tau protein pathways (Ju & Tam., 2022; Passeri et al., 2022) [39,60] .
Amyloid-targeting therapies
Aβ (and its oligomers) are currently the most important therapeutic "target" in Alzheimer's Disease (AD). Most studies link the presence of Aβ with the progression from cognitive impairment to AD. Several potential strategies have been developed for decreasing the quantity of Aβ that continues to be produced or clearing it from the brain. Importantly, Aβ is normally cleared from the brain interstitium in a process that shows diurnal variations, utilizing an intracellular vesicle trafficking pathway. A1-3 were the first pharmacological agents tested in clinical trials for the treatment of AD (Pardo-Moreno et al., 2022; Jeremic et al., 2021) [58,38] . They are designed to prevent aggregate formations (either oligomers or plaques) that induce neuronal damage, so their main goal was recognizing and binding soluble Aβ. However, their therapeutic effect was found to be limited when applied during advanced stages of AD development, after the emergence and prior to massive accumulation of senile plaques. These findings have driven the pursuit of alternative therapeutic approaches (Pardo-Moreno et al., 2022; Jeremic et al., 2021) [58,38] . There are other targets under investigation located in the cascade that leads to continued Aβ formation: β-secretase, γsecretase, and the alpha-secretase route, which is known to be Aβ non-producing, named APP metabolic pathways. Some inhibitors of beta-and gamma-secretase were also developed. Lifelong loss of synaptic adhesion molecules within the Central Nervous System (CNS) inhibits Aβ plaque deposition, partially rescues pre-existing Aβ-induced memory deficits, and restores synaptic connectivity. The results present a striking demonstration of the far-reaching impact that normal synaptic adhesion processes can have on both the manifestation of Aβ [25,27,38,58] .
Tau-targeting therapies
The theory that abnormal tau is the cause of disease has gained further credence due to the discovery of mutations in tau, which lead to the formation of NFTs and can cause frontotemporal dementia. In order to be most effective, therapeutics of tau must address the underlying malfunction that results in NFT formation. Taken together, the knowledge of tau's hyperphosphorylation, detachment from microtubules, aggregation, and NFT formation forms a roadmap detailing the critical points where treatments should focus. Some approaches to tau targeting include stabilizing the microtubules, using nerve growth factors, reducing tau phosphorylation or insolubility, and conducting tau-based immunotherapy. Collectively, these approaches have been successful in eliminating or decreasing the pathological accumulation of tau in various tauopathies (Mulroy et al., 2020) [54] . One of the first tau-targeting therapeutics introduced was the use of the microtubule-stabilizing drug. Tau becomes excessively phosphorylated when microtubules are destabilized, which leads to aggregation. Microtubule destabilization, specifically in its interactions with tau, forms the biochemical basis of drug-induced hyperphosphorylation of tau found in Alzheimer's disease. To decrease tau aggregation and the accumulation of NFTs, the presence of unstable microtubules must be minimized. In brief, the drug increased the time that the depolymerization of microtubules occurs from tau and decreases the amount of tau involved in fibril formation. In the presence of the drug, abnormally phosphorylated tau redistributed to the stabilized microtubules. Restricted movement as a result of the lack of tubulin release prevented it from being extracted when availability for other reactions was achieved. When the drug was incubated with brain tissue, hyperphosphorylated tau decorrelated with the NFTs and redistributed to the microtubules. In effect, the microtubules were stabilized, which prevented the formation of NFTs with an overall reduction in the structure's quantity (Zhang et al., 2022; Moore et al., 2023; Mulroy et al., 2020) [27, 53, 54] .
Emerging technologies in Alzheimer's research
Thus far, there are no biological fluid-based biomarkers with the clinical sensitivity and specificity of MRI, CT, or inflammatory marker profiles. Emerging technologies may change this. The study of peripheral blood-based gene expression profiles and proteomics represents broad-based strategies to identify and evaluate candidate markers with high diagnostic accuracy and predictive potential. Building on significant discoveries in the brain, biochemical advances using amyloid precursor protein and beta-amyloid assays are being developed for sampling. The development of tau and phosphorylated tau assays may allow a biochemical approach to the differential diagnosis of neurodegenerative diseases. Where gene expression and proteomics series manifest clear diagnostic alleles, DNA array (Agoston & Helmy., 2023; Zetterberg., 2022) [4,10] .
Artificial intelligence and machine learning
Artificial intelligence and especially machine learning are expanding the clinical chemistry capabilities for routine analytical determinations of both well-studied diseases and mainly complex multifactorial pathologies that have been so far difficult to diagnose or prognose early. Despite some important advances in the diagnostic aspects of cognitive impairment and dementia, there is a growing societal need to find new and better methods for achieving comprehensive, dominantly early stage diagnosis, comprehension, and prediction of chronic neurodegenerative pathologies with their typical, though still not completely understood, biochemical abnormalities. Artificial intelligence tools and machine learning may provide completely new or augmented capabilities for improved disease management (Iqbal et al., 2021; Herman et al., 2021) [36,33] . It is of interest to know that the term artificial intelligence was first conceived about eight decades before the scientific foundation for such attempts was laid with the invention of the modern computer. Nevertheless, the term has been reserved for machine implementations of skilled tasks that are intricately characteristic of human beings. Despite many years of impressive demonstrations of efficient implementations, they remained poor imitations of human tasks. In the field of laboratory medicine, analytical chemists achieved to bestow limited artificial intelligence features on analytical determinations not through an embodied computer, but by allowing simple automatic machines to combine a limited set of pre-selected and postprocessed analytical results and using them to suggest further analysis or analyze implications regarding a person's health condition or disease risk assessment. These were based on more or less fundamentally established and everused risk prediction models (Tran et al., 2022; Iqbal et al., 2021; Herman et al., 2021) [36,33] .
Nanotechnology
The design, development, and potential use of nanotechnology in medicine have generated a lot of interest in recent years. Such a new and exciting paradigm has great potential to be used in detecting and treating diseases, including Alzheimer's disease, in a more timely and safe manner. Nanomedicine-based applications for early Alzheimer's disease intervention include the design and discovery of new probes for the early detection of Alzheimer's disease biomarkers. Specifically, metals, metal oxides, nanowires, nanoparticles, quantum dots, and nanoshells are engineered intermittently to recognize and specifically interact with the early Alzheimer's disease indicators, and then identified by various detection methods (Puranik et al., 2023; Cáceres et al., 2023) [64,12] . Quantum dots are one of the interesting options for developing highthroughput perdeutero chemistry, such as microassays to examine large numbers of formalin-fixed Alzheimer's disease patient brain samples. They are bigger than biological molecules, and they do not degrade, which can be desired for long-term sensing. Among the various forms of quantum dots, copper sulfide has characteristics that are well suited for Alzheimer's disease treatment and analysis, especially compared to gold, which entails high material use costs (Puranik et al., 2023; Cáceres et al., 2023) [64,12] . Nanosystems such as micelles are used to enable the transport of small interfering RNA to the brain to help decrease the expression of the amyloid precursor protein, one of the hallmark products of Alzheimer's disease. Nanotechnology-assisted drug delivery provides a mechanism for targeting drugs to the brain, and possibly even selectively to brain regions. This is of the utmost importance in providing a beneficial result for Alzheimer's patients. Nanodrug therapies might also be able to target other detrimental events, such as tangle formation, inflammation, infection, and other toxicities that are implicated in the Alzheimer's disease cascade. The use of nanodrugs for combination therapy can target these specific biological events. There are more supportive roles for nanotechnology in Alzheimer's disease. One such role is the potential of nanoparticles to deliver imaging probes with a dual function. The other potential role is the use of nanoparticles to protect neurons or other brain cells from excessive oxidative stress, infection, or other injury induced by the disease cascade (Cano et [15,64,12] .
Challenges and future directions in clinical chemistry research on Alzheimer's Disease
Clinical chemistry research on Alzheimer's Disease (AD) is critical to identify reliable blood and Cerebrospinal Fluid (CSF) biomarkers for early diagnosis, disease progression, and to assess new treatment strategies. Indeed, these tests would also be more cost-effective alternatives to amyloid brain imaging methods, avoiding radio ligand exposure and the need for highly qualified human resources. Despite the amount of research in this field, the number of reliable tests for AD is still meager. The majority of studies conducted so far were relatively small. There is a need to validate and standardize studies with multiple methods in large multicenter studies. Preanalytical and analytical problems such as differences in sample types, preparation methods, instrumentation, and chemistry reagents are responsible for the variability of results. Improved and standardized strategies will allow better definition of the importance of differences in laboratory results, as much as age, sex, and ethnic differences. Other future challenges are to understand the role of chemicals in AD and how they interfere in biomarker levels, particularly in older people who generally take a cocktail of drugs that could interact with the results (Zetterberg & Blennow., 2021; Budelier and Bateman., 2020; Hansson et al., 2022) [10,29,11] .
Standardization of biomarker assays
The importance of the early diagnosis and cure of dementia diseases, in which Alzheimer's disease is the most representative one, is widely recognized. Numerous studies are being performed in multiple scientific fields to contribute existing efforts to obtain this objective. Anything less than that, the growing number of patients with dementia will cause huge stress on society, and the economic burden will increase year after year. The search for biomarkers in general is key, since a fully specific and accurate association of a particular disease with its corresponding biomarkers can generate the "definitive" diagnosis. Assays are components of medical decision-making, and the first fundamental requirement is harmonization or standardization when samples are exchanged between laboratories. When a blood sample is collected and separated serum or plasma is stored for several weeks or even months, potential loss of the proteins in the samples occurs without preservation of the specimen. Since there are many countries and laboratories, non-standardization in measurement occurs, meaning that it is necessary to introduce highly effective harmonization and standardization methods. Clinical laboratory materials are available through relevant organizations, which have a Liaison Group to the World Health Organization. Data on the lot include expiry dates, container-stopper type and color, and recommended storage conditions. The stored blood supply could be monitored to follow the loss of activity of the analyte. Regular samples may be tested by reference laboratories accepting analytical requests to verify the results of testing stored blood, shipping serum samples to home-based reagent users, and comparing these results with the laboratory's own results if promise is perceived (Ausó et al., 2020; Mahaman et al., 2022; Klyucherev et al., 2022) [8,49,41] .
Translational research and clinical trials
The future of clinical diagnostics is prevention rather than damage control, and as such, we should be able to use new technologies to screen patients who are beginning to develop Alzheimer's disease symptoms before any significant cognitive impairment has occurred. The technologies should be non-invasive, efficient, accurate, cost-effective, easily performed, and acceptable to patients. The translation of biomedical technology from the research environment into the clinic and to the community is difficult and sometimes painstaking work, requiring long-term strategies and persistent efforts. Today, most clinical chemists use research funding to develop new technologies, while antibody-based assays continue to be the gold standard with relatively slow biophase response. The best technology has to be refined and formatted for large-scale use. Healthcare professionals are faced with a myriad of commercially available diagnostic products, and it becomes increasingly important to critically evaluate these technologies based on independent scientific performance data. The concept of diagnostic assays is based on the use of well-founded and specific clinical study criteria and protocols to ensure accurate and meaningful patient results (Porsteinsson et al., 2021; Cammisuli et al., 2022) [63,14] . The clinical use of amyloid imaging in Alzheimer's disease diagnosis is limited to medical research due to regulatory approval. Experiments have demonstrated that sophisticated multi-analyte methods hold great promise when applied in Alzheimer's disease research studies. It is anticipated that autoimmune reagents will have a major impact and make possible practical tests of biomarkers needed to accurately diagnose, predict, and monitor the treatment progress of Alzheimer's disease and other neurodegenerative diseases. Biomarkers can measure and monitor the extent of the disease process, which is important not only in understanding the pathological nature of diseases and the drug discovery process but also are of great importance in patient decision-making, clinical guiding therapy, and monitoring the disease progression. Such information will help improve the use of available drugs that can slow down symptom onset for a period, help identify patients at high risk, and develop prevention therapy in the near future. It is vital for life scientists to understand which routes to focus on when this knowledge and advice is current and growing each day (Sabbagh et al., 2020; Öhman et al., 2021; Porsteinsson et al., 2021, Cammisuli et al., 2022) [63,56,14] .
Conclusion
Understanding the biochemical basis of Alzheimer's disease is essential for advancing both diagnosis and treatment. This clinical chemistry approach underscores the significance of identifying and analyzing key biomarkers associated with the disease, which can facilitate early detection and monitoring of disease progression. By elucidating the roles of amyloid-beta peptides, tau protein, and oxidative stress, we gain valuable insights into the pathophysiological mechanisms driving neurodegeneration. Furthermore, recognizing the potential for targeted therapeutic interventions based on these biochemical findings holds promise for improving patient outcomes. Continued research in this area is crucial, as it not only enhances our comprehension of Alzheimer's disease but also informs the development of innovative strategies for intervention and care. Ultimately, a deeper understanding of the biochemical landscape of AD will contribute to more effective clinical practices and better quality of life for affected individuals and their families.
Funding
Funding
Declaration of competing interest
The authors say they don't have any known personal or financial relationships or financial interests that could have seemed to affect the work in this study.
References
79 in the original paper- Abbas M. Potential role of nanoparticles in treating the accumulation of amyloid-beta peptide in Alzheimer's International Journal of Advanced Chemistry Research https://www.chemistryjournals.net patients. Polymers. 2021. Available from: https://mdpi.com
- Abubakar MB, Sanusi KO, Ugusman A, Mohamed W, Kamal H, Ibrahim NH, et al. Alzheimer's disease: an update and insights into pathophysiology. Front Aging Neurosci. 2022;14:742408. Available from: https://frontiersin.org
- Adnan ZA, Farhan ZM, Mohsein OA. Understanding the link between diabetes mellitus and fatty liver disease: A narrative review. Int J Chem Stud. 2024;12(4):40-48.
- Agoston DV, Helmy A. Fluid-Based Protein Biomarkers in Traumatic Brain Injury: The View from the Bedside. Int J Mol Sci. 2023. Available from: https://mdpi.com
- Al-Mekhlafi A, Sühs KW, Schuchardt S, Kuhn M, Müller-Vahl K, Trebst C, et al. Elevated free phosphatidylcholine levels in cerebrospinal fluid distinguish bacterial from viral CNS infections. Cells. 2021;10(5):1115. Available from: https://mdpi.com
- Anapindi KD, Romanova EV, Checco JW, Sweedler JV. Mass spectrometry approaches empowering neuropeptide discovery and therapeutics. Pharmacol Rev. 2022;74(3):662-79. Available from: https://nih.gov
- Ashrafian H, Zadeh EH, Khan RH. Review on Alzheimer's disease: inhibition of amyloid beta and tau tangle formation. Int J Biol Macromol. 2021;167:382394.
- Ausó E, Gómez-Vicente V, Esquiva G. Biomarkers for Alzheimer's disease early diagnosis. J Pers Med. 2020. Available from: https://mdpi.com
- Barthelson K, Pederson SM, Newman M, Lardelli M. Analysis reveals subtle effects on mitochondrial function and iron homeostasis of mutations in the SORL1 gene implicated in early onset familial Alzheimer's disease. Mol Brain. 2020. Available from: https://springer.com
- Blomqvist M, Zetterberg H, Blennow K, Månsson JE. Sulfatide in health and disease. The evaluation of sulfatide in cerebrospinal fluid as a possible biomarker for neurodegeneration. Mol Cell Neurosci. 2021;116:103670. Available from: https://sciencedirect.com
- Budelier MM, Bateman RJ. Biomarkers of Alzheimer disease. J Appl Lab Med. 2020;5(1):194-208. Available from: https://nih.gov
- Cáceres C, Heusser B, Garnham A, Moczko E. The major hypotheses of Alzheimer's disease: related nanotechnology-based approaches for its diagnosis and treatment. Cells. 2023. Available from: https://mdpi.com
- Cai Y, Liu J, Wang B, Sun M, Yang H. Microglia in the neuroinflammatory pathogenesis of Alzheimer's disease and related therapeutic targets. Front Immunol., 2022. Available from: https://frontiersin.org
- Cammisuli DM, Cipriani G, Castelnuovo G. Technological solutions for diagnosis, management and treatment of Alzheimer's disease-related symptoms: A structured review of the recent scientific literature. Int J Environ Res Public Health. 2022;19(5):3122. Available from: https://mdpi.com
- Cano A, Turowski P, Ettcheto M, Duskey JT, Tosi G, Sánchez-López E, et al. Nanomedicine-based technologies and novel biomarkers for the diagnosis and treatment of Alzheimer's disease: from current to future challenges. J Nanobiotechnology. 2021;19(1):122. Available from: https://springer.com
- Chen CY, Lin YS, Lee WJ, Liao YC, Kuo YS, Yang A. Endophenotypic effects of the SORL1 variant rs2298813 on regional brain volume in patients with late-onset Alzheimer's disease. Front Aging Neurosci. 2022;14:885090. Available from: https://frontiersin.org
- Chen ZR, Huang JB, Yang SL, Hong FF. Role of cholinergic signaling in Alzheimer's disease. Molecules. 2022. Available from: https://mdpi.com
- Crestini A, Santilli F, Martellucci S, Carbone E, Sorice M, Piscopo P, et al. Prions and neurodegenerative diseases: a focus on Alzheimer's disease. J Alzheimer's Dis. 2022;85(2):503-518. Available from: https://escholarship.org
- Curtin SC, Tejada-Vera B, Bastian BA. Deaths: leading causes for 2020. CDC, 2023. Available from: https://cdc.gov
- Du Z, Li M, Ren J, Qu X. Current strategies for modulating Aβ aggregation with multifunctional agents. Acc Chem Res. 2021.
- Feng L, Li J, Zhang R. Current research status of blood biomarkers in Alzheimer's disease: Diagnosis and prognosis. Ageing Res Rev. 2021.
- Fernández-Calle R, Konings SC, Frontiñán-Rubio J, García-Revilla J, Camprubí-Ferrer L, Svensson M, et al. APOE in the bullseye of neurodegenerative diseases: impact of the APOE genotype in Alzheimer's disease pathology and brain diseases. Mol Neurodegener. 2022;17(1):62. Available from: https://springer.com
- Frisoni GB, Altomare D, Thal DR, Ribaldi F, van der Kant R, Ossenkoppele R, et al. The probabilistic model of Alzheimer disease: the amyloid hypothesis revised. Nat Rev Neurosci. 2022;23(1):53-66. Available from: https://nih.gov
- Ganguly U, Kaur U, Chakrabarti SS, Sharma P, Agrawal BK, Saso L, et al. Oxidative stress, neuroinflammation, and NADPH oxidase: implications in the pathogenesis and treatment of Alzheimer's disease. Oxid Med Cell Longev. 2021;2021:7086512. Available from: https://wiley.com
- Ghosh S, Ali R, Verma S. Aβ-oligomers: A potential therapeutic target for Alzheimer's disease. Int J Biol Macromol. 2023;239:124231.
- Goldman J, Xie S, Green D, Naini A, Mansukhani MM, Marder K. Predictive testing for neurodegenerative diseases in the age of next-generation sequencing. J Genet Couns. 2021;30(2):553-562. Available from: https://wiley.com
- Guan YH, Zhang LJ, Wang SY, Deng YD, Zhou HS, Chen DQ. The role of microglia in Alzheimer's disease and progress of treatment. Ibrain. 2022;8(1):37-47. Available from: https://wiley.com
- Gupta J, Gupta R, Sharma P. Alzheimer's Disease: Role of Amyloid-β Peptide in the Pathogenesis of Neurodisorder. Eur J Mol Clin Med. 2022;9(7):72827290. Available from: https://researchgate.net
- Hampel H, Hardy J, Blennow K, Chen C, Perry G, Kim SH, et al. The amyloid-β pathway in Alzheimer's disease. Mol Psychiatry. 2021;26(10):5481-503. Available from: https://nature.com
- Hansson O, Edelmayer RM, Boxer AL, Carrillo MC, Mielke MM, Rabinovici GD, et al. The Alzheimer's Association appropriate use recommendations for blood biomarkers in Alzheimer's disease. Alzheimer's Dement. 2022;18(12):2669-2686.
- Hart de Ruyter FJ, Evers MJ, Morrema TH, Dijkstra AA, den Haan J, Twisk JW, et al. Neuropathological hallmarks in the post-mortem retina of neurodegenerative diseases. Acta Neuropathol. 2024;148(1):24.
- Henriques AD, Machado-Silva W, Leite RE, Suemoto CK, Leite KR, Srougi M, et al. Genome-wide profiling and predicted significance of post-mortem brain microRNA in Alzheimer's disease. Mech Ageing Dev. 2020;191:111352.
- Herman DS, Rhoads DD, Schulz WL, Durant TJ. Artificial intelligence and mapping a new direction in laboratory medicine: a review. Clin Chem. 2021;67(11):1466-1482.
- Heron M. Deaths: leading causes for 2019; 2021. Available from: https://cdc.gov
- Inyushin M, Zayas-Santiago A, Rojas L, Kucheryavykh L. On the role of platelet-generated amyloid beta peptides in certain amyloidosis health complications. Front Immunol. 2020;11:571083.
- Iqbal MJ, Javed Z, Sadia H, Qureshi IA, Irshad A, Ahmed R, et al. Clinical applications of artificial intelligence and machine learning in cancer diagnosis: looking into the future. Cancer Cell Int. 2021;21(1):270.
- Ito E, Iha K, Yoshimura T, Nakaishi K, Watabe S. Early diagnosis with ultrasensitive ELISA. Adv Clin Chem. 2021;101:121-133.
- Jeremic D, Jiménez-Díaz L, Navarro-López JD. Past, present and future of therapeutic against amyloid-β peptides in Alzheimer's disease: A systematic review. Ageing Res Rev. 2021;69:101362.
- Ju Y, Tam KY. Pathological mechanisms and therapeutic strategies for Alzheimer's disease. Neural Regen Res. 2022;17(5):925-934.
- King A, Bodi I, Troakes C. The neuropathological diagnosis of Alzheimer's disease the challenges of pathological mimics and concomitant pathology. Brain Sci. 2020;10(11):870.
- Klyucherev TO, Olszewski P, Shalimova AA, Chubarev VN, Tarasov VV, Attwood MM, et al. Advances in the development of new biomarkers for Alzheimer's disease. Transl Neurodegener. 2022;11(1):25.
- Kwon DH, Hwang JS, Kim SG, Jang YE, Shin TH, Lee G. Cerebrospinal fluid metabolome in Parkinson's disease and multiple system atrophy. Int J Mol Sci. 2022;23(3):1879.
- Nasser NA, Sadek AH, Mahmeed BA, Mohsein OA. The levels of prostate specific antigen and leptin hormone in patients with prostate cancer. S Asian J Life Sci. 2025;13:1-7.
- Li J, Zhan X. Mass spectrometry-based proteomics analyses of post-translational modifications and proteoforms in human pituitary adenomas. Biochim Biophys Acta Proteins Proteom. 2021;1869(3):140584.
- Li N, Desiderio DM, Zhan X. The use of mass spectrometry in a proteome-centered multiomics study of human pituitary adenomas. Mass Spectrom Rev. 2022;41(2):178-196.
- Liang CS, Li DJ, Yang FC, Tseng PT, Carvalho AF, Stubbs B, et al. Mortality rates in Alzheimer's disease and non-Alzheimer's dementias: a systematic review and meta-analysis. Lancet Healthy Longev. 2021;2(8):e479-e488.
- Lista S, Mapstone M, Caraci F, Emanuele E, LópezOrtiz S, Martín-Hernández J, et al. A critical appraisal of blood-based biomarkers for Alzheimer's disease. Ageing Res Rev. 2024;102290.
- Litvinenko IV, Lobzin VY. On a new paradigm of the development of neurodegenerative diseases by the example of Alzheimer's disease and Parkinson's disease. Adv Gerontol. 2022;12(3):116-129.
- Mahaman YAR, Embaye KS, Huang F, Li L, Zhu F, Wang JZ, et al. Biomarkers used in Alzheimer's disease diagnosis, treatment, and prevention. Ageing Res Rev. 2022;74:101544.
- Mohsein OA, Thuwaini MM, Salman HK. The relationship between leptin, thyroid hormone and insulin resistance in obese diabetic patients. Cent Asian J Med Nat Sci. 2023;4(3):518-523.
- Mankhong S, Kim S, Lee S, Kwak HB, Park DH, Joa KL, et al. Development of Alzheimer's disease biomarkers: From CSF-to blood-based biomarkers. Biomedicines. 2022;10(4):850.
- Minic R, Zivkovic I. Optimization, validation and standardization of ELISA. Norovirus. In: IntechOpen; 2020. Available from: https://intechopen.com
- Moore KBE, Hung TJ, Fortin JS. Hyperphosphorylated tau (p-tau) and drug discovery in the context of Alzheimer's disease and related tauopathies. Drug Discov Today. 2023;28(4):838-846.
- Mulroy E, Jaunmuktane Z, Balint B, Erro R, Latorre A, Bhatia KP. Some new and unexpected tauopathies in movement disorders. Mov Disord Clin Pract. 2020;7(6):616-621.
- Muralidar S, Ambi SV, Sekaran S, Thirumalai D, Palaniappan B. Role of tau protein in Alzheimer's disease: The prime pathological player. Int J Biol Macromol. 2020;163:1599-1617.
- Öhman F, Hassenstab J, Berron D, Schöll M, Papp KV. Current advances in digital cognitive assessment for preclinical Alzheimer's disease. Alzheimer's Dement Diagn Assess Dis Monit. 2021;13(1):e12217.
- Padala SP, Newhouse PA. Blood-based biomarkers in Alzheimer's disease: A mini-review. Metab Brain Dis. 2023;38:27-34.
- Pardo-Moreno T, González-Acedo A, RivasDomínguez A, García-Morales V, García-Cozar FJ, Ramos-Rodríguez JJ, et al. Therapeutic approach to Alzheimer's disease: current treatments and new perspectives. Pharmaceutics. 2022;14(6):1117.
- Parhizkar S, Holtzman DM. APOE mediated neuroinflammation and neurodegeneration in Alzheimer's disease. Semin Immunol. 2022;58:101582.
- Passeri E, Elkhoury K, Morsink M, Broersen K, Linder M, Tamayol A, et al. Alzheimer's disease: treatment strategies and their limitations. Int J Mol Sci. 2022;23(22):13954.
- Pathak N, Vimal SK, Tandon I, Agrawal L, Hongyi C, Bhattacharyya S. Neurodegenerative disorders of Alzheimer, Parkinsonism, amyotrophic lateral sclerosis and multiple sclerosis: an early diagnostic approach for precision treatment. Metab Brain Dis. 2021;1-38.
- Peng P, Liu C, Li Z, Xue Z, Mao P, Hu J, et al. Emerging ELISA derived technologies for in vitro diagnostics. TrAC Trends Anal Chem. 2022;152:116605.
- Porsteinsson AP, Isaacson RS, Knox S, Sabbagh MN, Rubino I. Diagnosis of early Alzheimer's disease: clinical practice in 2021. J Prev Alzheimers Dis. 2021;8(5):371-386.
- Puranik N, Yadav D, Song M. Advancements in the Application of Nanomedicine in Alzheimer's Disease: A Therapeutic Perspective. Int J Mol Sci. 2023;24(1):16.
- Rahman A, Banu Z, Rani R, Mehdiya R. Unravelling Alzheimer's disease: Insights into pathophysiology, etiology, diagnostic approaches, and the promise of aducanumab, lecanemab, and donanemab. J Phytonanotech Pharm Sci. 2024;4(3):1-10.
- Rahman MM, Lendel C. Extracellular protein components of amyloid plaques and their roles in Alzheimer's disease pathology. Mol Neurodegener. 2021;16(1):54.
- Rasmussen MK, Mestre H, Nedergaard M. Fluid transport in the brain. Physiol Rev. 2022;102(1):1-45.
- Rocha S, Peixoto P, Marques P. Evaluation of cerebrospinal fluid biomarkers in Alzheimer's disease. J Neurosci. 2023;42(5):1179-1192.
- Santos RR, Pereira L. Analysis of cerebrospinal fluid biomarkers in Alzheimer's disease. Methods Mol Biol. 2024;2534:123-141.
- Shankar GM, Walsh DM. Alzheimer's disease: synaptic dysfunction and the amyloid beta oligomer hypothesis. Neurochem Int. 2020;85:60-68.
- Shi Y, Zhu Q, Wu T, Wang Y, Yu J. The Role of tau in Alzheimer's disease and other neurodegenerative disorders. Mol Neurodegener. 2021;16(1):69.
- Shekhar S, Martin T, Chowdhury R. Progress in diagnostic biomarkers for Alzheimer's disease: Current trends and perspectives. Curr Alzheimer Res. 2022;19(9):747-763.
- Stojanovic A, Ken I, Hong J. Role of genetic factors in neurodegenerative diseases. Transl Neurosci. 2023;14(2):43-58.
- Thomas W, Cools H, Ghosh A, Ong B. Amyloid-beta peptide signaling in Alzheimer's disease. Curr Opin Neurol. 2021;34(3):389-397.
- Tocheva L, Varadarajulu S, King M, Kumar A. Novel diagnostic biomarkers for Alzheimer's disease: The role of imaging. J Neurol. 2023;270(4):1552-1560.
- Tohyama S, Fujiwara H, Iwatsubo T. Neurodegenerative diseases and amyloid-beta peptide misfolding. FEBS Lett. 2020;594(7):1075-1088.
- Tornatore T, Onofri F, Scheinfeld M. The role of amyloid-beta in cognitive decline: Strategies for therapeutic intervention. Ageing Res Rev. 2024; 48:101-114.
- Wang Z, Zhang Y, Xie Y. The application of PET in Alzheimer's disease diagnosis. Aging Cell. 2022;21(4):e13543.
- Xu Y, Zhan W, Chang K. Early biomarker detection for Alzheimer's disease through modern diagnostic techniques. J Alzheimers Dis. 2024;87(2):581-594.