
Research article · 2025 · Full text
International Journal of Agriculture and Food ScienceComplementary feeding practices and associated factors among mothers of children age 6-24 months of Banaskantha district
Volume 7(8) · Pages 1423–1432 · DOI: 10.33545/2664844x.2025.v7.i8n.719 ↗
Research areasChild Nutrition and Water AccessFood Security and Health in Diverse Populations
Abstract
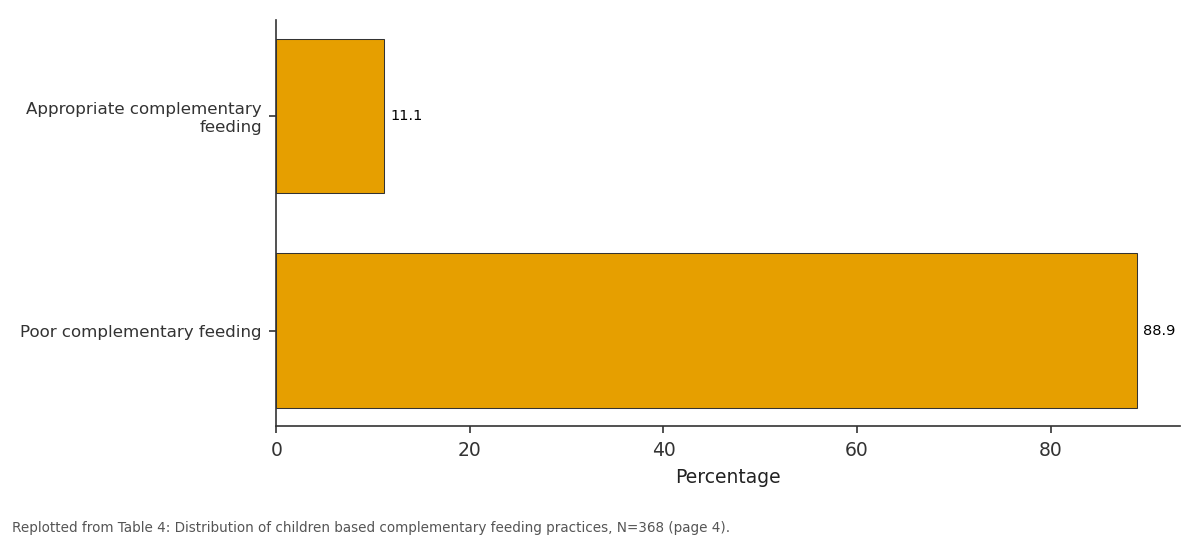
Author-writtenMalnutrition during early childhood remains a pressing public health issue in many developing regions, including India. One of the primary contributors to under nutrition among children aged 6-24 months is inappropriate complementary feeding practices. Although the World Health Organization (WHO) recommends the timely introduction of safe and nutritionally adequate complementary foods in conjunction with continued breastfeeding, adherence to these guidelines remains poor in several parts of India. This study was conducted to assess the prevalence and determinants of complementary feeding practices among children aged 6-24 months in Banaskantha district, Gujarat, and to examine their associations with maternal socio-economic characteristics. A descriptive cross-sectional design was employed, involving 368 mother-child pairs selected through proportionate simple random sampling. Data collection included structured interviews with mothers to gather socio-demographic information and feeding practices, along with anthropometric measurements of children. Findings revealed a significant gap in adherence to WHO-recommended complementary feeding practices. Only 11.1% of children received appropriate complementary feeding, while 88.9% exhibited poor practices. Timely initiation of complementary feeding was observed in just 43.5% of children, and only 36.1% met the minimum dietary diversity (MDD). While dairy products (100%) and grains/tubers (95%) were widely consumed, intake of protein-rich foods such as flesh foods (0.54%) and eggs (0.81%), as well as vitamin A-rich fruits and vegetables (17%), was notably low. Furthermore, 39.9% of children consumed processed or packaged foods, and 25% consumed sweetened beverages. Only 28.8% of children achieved the minimum acceptable diet (MAD), and 58.2% met the minimum meal frequency (MMF). These findings underscore the urgent need for targeted nutritional interventions and behavior change communication strategies to improve complementary feeding practices in the region.
Summary
Source-checkedPlain-language reading of the full paper, prepared with AI and checked against the text. Each point links to the authors' own words.
Why it matters
- Inappropriate complementary feeding practices are a primary cause of childhood malnutrition in developing regions like India. View evidence ↗
- The period between 6 and 24 months is critical for a child's growth, immunity, and cognitive development; poor feeding here increases the risk of stunting and micronutrient deficiencies. View evidence ↗
- Nutritional status in Gujarat is particularly concerning, with high rates of stunting (39.0%), wasting (25.3%), underweight (39.7%), and anemia (79.7%) in children. View evidence ↗
The question
- The study aimed to determine the prevalence of complementary feeding practices in the Banaskantha district of Gujarat and how these practices relate to the mothers' socio-economic characteristics. View evidence ↗
What they did
- The researchers used a descriptive cross-sectional design with 368 mother-child pairs selected via proportionate simple random sampling. View evidence ↗
- Data was collected using structured interviews covering personal characteristics, a modified socio-economic status scale, and complementary feeding practices. View evidence ↗
- The study analyzed data using frequency distributions, Chi-square tests, and Z-tests. View evidence ↗
What they found
- The vast majority of children (88.9%) had poor complementary feeding practices, with only 11.1% receiving appropriate feeding. View evidence ↗
- Only 43.5% of children had complementary feeding started on time, and only 36.1% met the minimum dietary diversity requirements. View evidence ↗
- While dairy (100%) and grains/tubers (95%) were common, there was very low intake of eggs (0.81%), flesh foods (0.54%), and vitamin A-rich produce (17%). View evidence ↗
- A significant portion of children consumed processed or packaged foods (39.9%) and sweetened beverages (25%). View evidence ↗
- Only 28.8% of children met the minimum acceptable diet standard, though 58.2% met the minimum meal frequency. View evidence ↗
- Hygiene was poor, with 88.9% of mothers failing to sterilize feeding utensils. View evidence ↗
- There is a statistically significant link between a mother's socio-economic status and the quality of complementary feeding (p < 0.001). View evidence ↗
- Maternal education level is highly significantly associated with child feeding behavior (p < 0.001). View evidence ↗
- Maternal occupation is also a critical determinant of feeding practices, showing high statistical significance (p < 0.001). View evidence ↗
What it means
- The authors conclude that targeted nutrition education and support are urgently needed for mothers who are low-income, less educated, or in informal work to improve child health. View evidence ↗
Visual summary
2 visualsIllustrations explain the paper; charts are replotted from the paper's own table values.
Percentage: Appropriate... vs Poor complementary...
Replotted from Table 4 (page 4) of the original paper. Every bar is the paper's own table value.
View source evidence ↗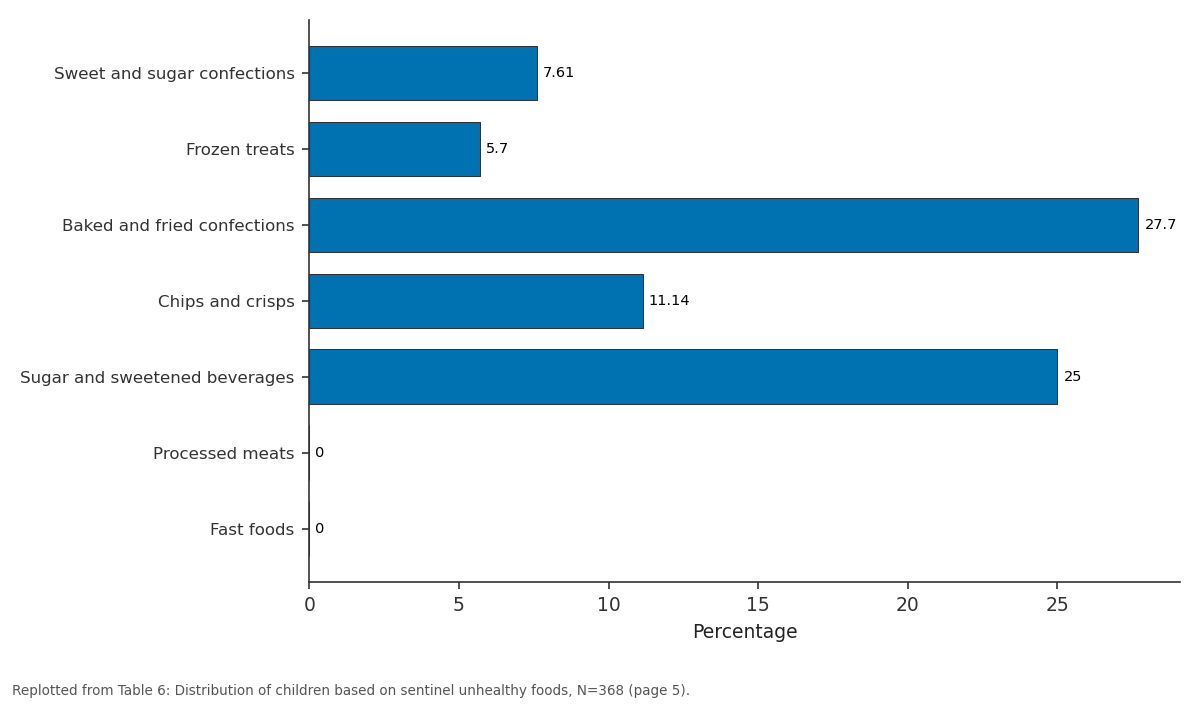
Percentage: Sweet and sugar... vs Frozen treats vs Baked and fried... vs Chips and crisps vs Sugar and sweetened...
Replotted from Table 6 (page 5) of the original paper. Every bar is the paper's own table value.
View source evidence ↗Figures & tables
From the original paper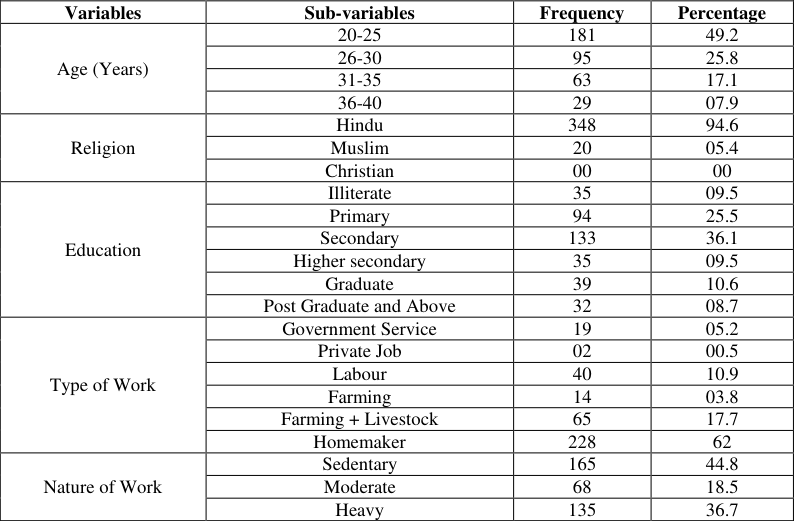 Table 1
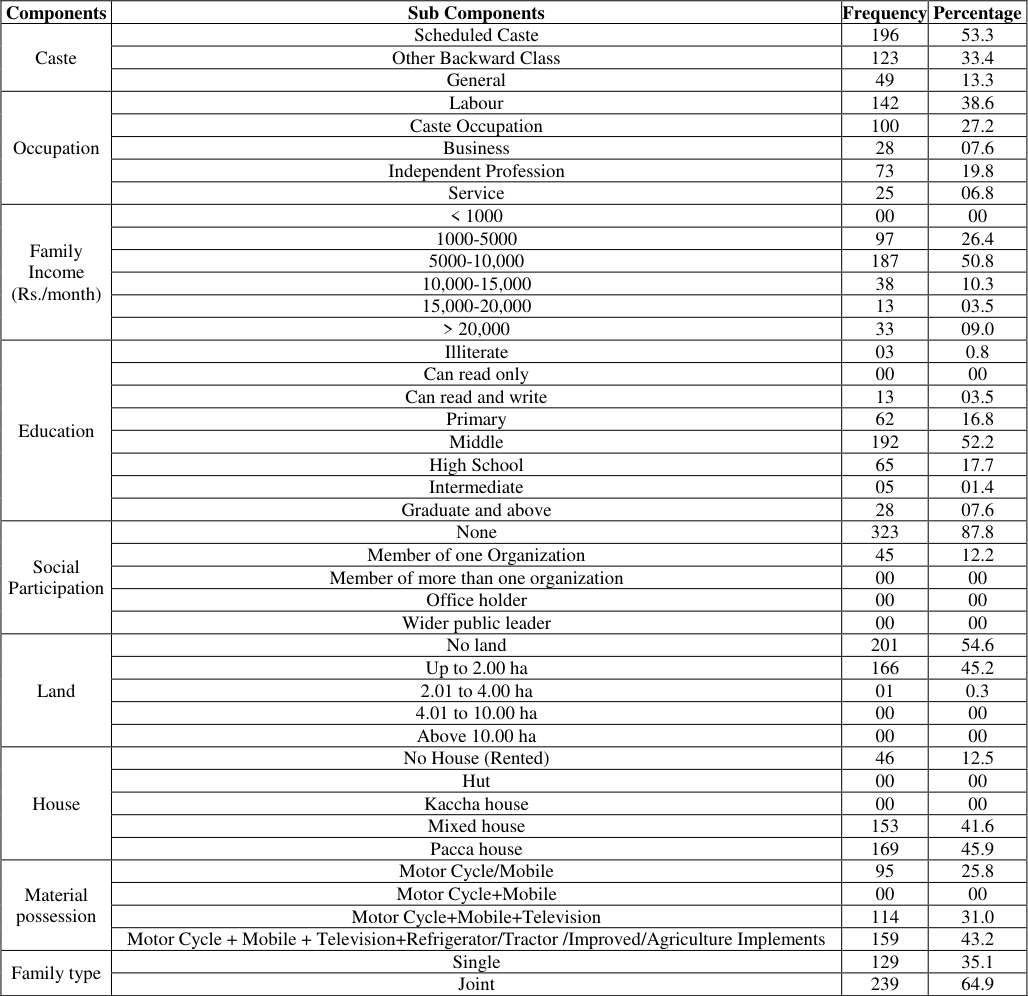 Table 2
 Table 3
 Table 4
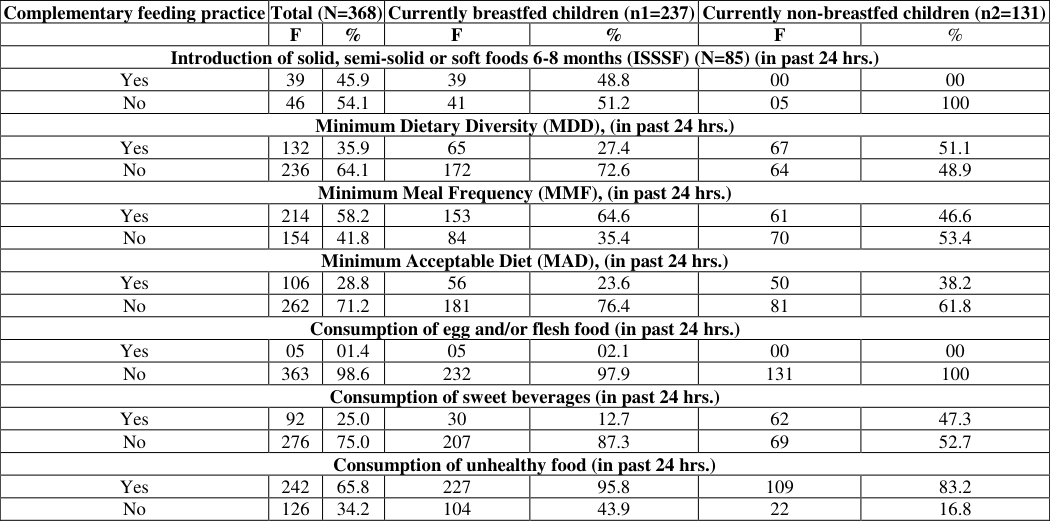 Table 5
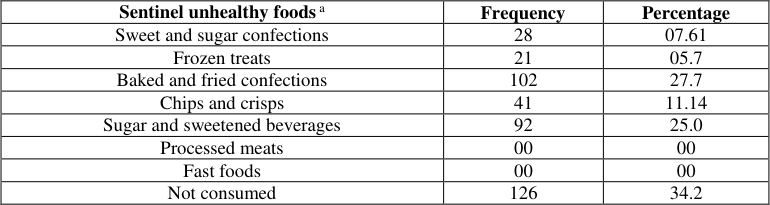 Table 6
 Table 7
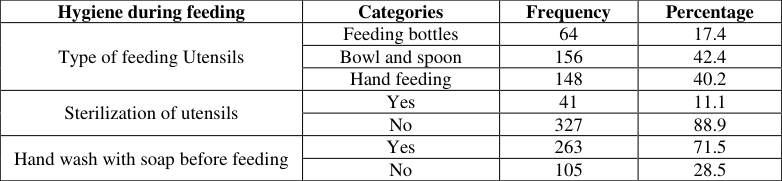 Table 8
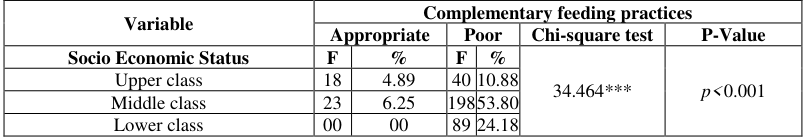 Table 9
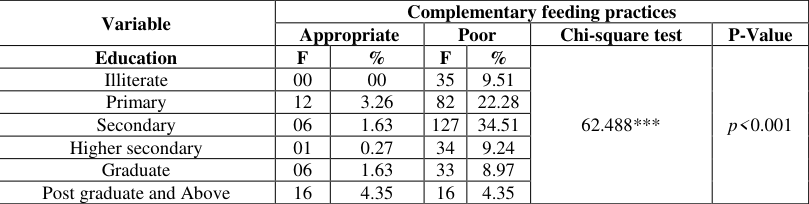 Table 10
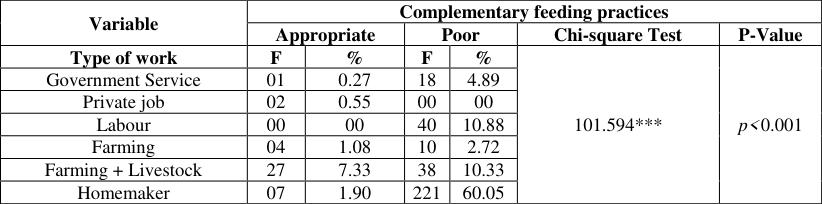 Table 11
Introduction
Malnutrition in early childhood remains a major public health concern in India, particularly among children under five, with high rates of stunting (35.5%), wasting (19.3%), and underweight (32.1%) nationally, as per NFHS-5 (2019-21). One of the most direct and preventable contributors to under nutrition is inappropriate complementary feeding introducing solid or semi-solid foods after six months of exclusive breastfeeding. The critical 6-24-month window is essential for growth, cognitive development, and immune function. Inadequate feeding during this period raises the risk of stunting, micronutrient deficiencies, and long-term health issues. The WHO recommends timely introduction of complementary foods at six months, continued breastfeeding up to two years or beyond, and adherence to key indicators Minimum Dietary Diversity (MDD), Minimum Meal Frequency (MMF), and Minimum Acceptable Diet (MAD). However, in India, particularly in rural and socioeconomically challenged areas, these practices remain suboptimal. Cultural beliefs, low maternal education, poverty, food insecurity, and limited awareness all contribute to poor feeding habits.
In Gujarat, the nutritional situation is more alarming: 39.0% of children under five are stunted, 25.3% wasted, and 39.7% underweight, with 79.7% of children aged 6-59 months anemic exceeding national averages. Within Gujarat, Banaskantha district exemplifies these challenges due to its rural landscape, dependence on agriculture, limited health services, and socio-cultural barriers. Issues such as early marriage, low maternal literacy, food taboos, and the growing presence of processed foods worsen the scenario. District-level data on complementary feeding are limited, necessitating localized research. Understanding the prevalence of WHO-recommended indicators and the maternal socio-economic and demographic factors influencing them is vital. This knowledge can inform tailored, community-driven nutrition interventions that are more effective than broad, top-down strategies. This study aims to assess the prevalence and determinants of complementary feeding practices among children aged 6-24 months in Banaskantha. By generating district-specific evidence, the study will help guide nutrition education, integrate findings into existing schemes like ICDS and Poshan Abhiyaan, and contribute to achieving Sustainable Development Goals related to hunger, health, and wellbeing.
Materials and Methods
A Descriptive Research Design was adopted to conduct the present study. The present study was conducted at ASPEE College of Nutrition and Community Science, Sardarkrushinagar Dantiwada Agricultural University, Sardarkrushinagar, Banaskantha, Gujarat. Proportionate Simple Random Sampling was used for respondent selection.The total sample size was 368, which is determined by the use of sample size estimation formula given by Abramson and Abramson, 1999 and the estimation is based on complementary feeding rate that is children age 6-8 months receiving semi-solid or solid food and breast milk in Gujarat. The data is taken from 5 th National Family Health Survey, 2019-20. The study included a total of 15,848 respondents across four talukas: Deesa, Lakhani, Kankarej, and Deodar. The highest number of respondents came from Deesa (6,536), followed by Kankarej (4,468), Lakhani (3,432), and Deodar (1,412). A proportional sampling method was applied, with each taluka contributing 2.32% of its total respondents to the final sample. Consequently, 151 respondents were selected from Deesa, 104 from Kankarej, 80 from Lakhani, and 33 from Deodar, resulting in a total of 368 selected respondents for the study. The interview schedule was developed by the researcher to collect the following data Background information performa to assess personal characteristics of the respondents, socio economic status scale of Udai Pareek and Trivedi with slight modification and performa on complementary feeding practices. An interview technique was used for data collection. The information was collected by direct observation and personal interview method on their permission. Collected data were analyzed with frequency distribution, Chi-square test and Z-test by Gupta and Kapoor (2002) [5] .
Results and Discussion
The personal characteristics of the mothers of children in the study reveal that nearly half (49.2%) were between 20 to 25 years of age, with the majority falling within the 20-30 year age range. The population was predominantly Hindu (94.6%), with very few Muslims (5.4%) and no Christians. In terms of education, most mothers had attained secondary education (36.1%), followed by primary education (25.5%), while a small proportion were illiterate (9.5%) or had pursued higher studies (graduate and above, 19.3% combined). Regarding occupation, a significant majority were homemakers (62%), while others were involved in labour (10.9%), farming combined with livestock (17.7%), or government and private sector jobs (5.7% combined). When assessing the nature of work, 44.8% of the mothers engaged in sedentary activities, while 36.7% were involved in heavy physical work and 18.5% in moderate activity levels (Table 1). indicator is computed from the WHO/UNICEF 2021 indicators such as child is currently breastfeeding, commenced complementary feeding at age 6 months and meets minimum meal frequency and minimum dietary diversity. Inappropriate complementary feeding on the other hand was defined as when a child did not meet these criteria. When assessed for overall complementary feeding, only 11.1 per cent of children received appropriate complementary feeding, whereas the remaining 88.9 per cent were categorized under poor complementary feeding practices (Table 4). The present study slightly exceeds this national figure. Tiwari et al., (2022) [24] in Madhya Pradesh, India, reported that only 9.7 per cent practicing appropriate complementary feeding. Their study emphasized that maternal education and ANC visits were significantly associated with better feeding practices. Kundu et al., (2020) [12] in West Bengal found that only 13.5 per cent of children had adequate complementary feeding. They also noted a strong correlation between low socio-economic status and poor feeding behaviors. The findings indicate a significant gap in adherence to optimal complementary feeding practices, particularly concerning dietary diversity and acceptable diet standards. Despite WHO recommendations for timely introduction of solid and semi-solid foods and achieving minimum dietary standards by 6-8 months (WHO, 2021) [29] , more than half the children in present study did not meet the recommended initiation period. The low percentage (35.9%) of children meeting MDD is comparable to findings from the National Family Health Survey (NFHS-5, 2021), which reported that only 25.5 per cent of Indian children aged 6-23 months consumed the minimum number of food groups. Interestingly, non-breastfed children in this study had higher rates of MDD and MAD than breastfed children. This trend aligns with research by Khan et al., (2019) [9] , which suggested that non-breastfed children often receive more varied complementary foods to compensate for the absence of breast milk. However, these same children were more likely to consume sweetened beverages, as observed in similar studies conducted in rural Bangladesh and Nepal (Senarath et al., 2012; Joshi et al., 2020) [22,6] , highlighting the risk of introducing less nutritious, high-sugar items as breast milk substitutes. The high prevalence of unhealthy food consumption, especially among breastfed children, is concerning. This could be due to a misconception among caregivers that breast milk alone compensates for poor quality complementary foods, as noted in a study by Nguyen et al., (2013) [18] across multiple South Asian countries. The minimal consumption of animal source foods (1.4%) also reflects limited access or cultural dietary restrictions; a common barrier identified in low income settings (Black et al., 2013) [3] . 6 highlights the frequency and percentage of children aged 6-24 months who consumed different types of sentinel unhealthy foods. These foods are commonly associated with poor dietary quality, early exposure to high fat, high sugar, and high sodium foods, and risk of non-communicable diseases (NCDs). The most consumed items were baked and fried confections (27.7%) and sugar-sweetened beverages (25%). Notably, processed meats and fast foods were not consumed at all, while 126 children (34.2%) had no exposure to any of the listed unhealthy foods. The results reveal significant early exposure to unhealthy foods, particularly baked/fried items and sweetened beverages, which can influence long-term dietary preferences and health outcomes. Poti et al., (2017) [20] emphasized that early introduction to unhealthy processed foods increases risk of childhood obesity and poor diet quality later in life. In India, a study by Agarwal et al., (2020) [2] found that 42 per cent of urban children under 2 years regularly consumed packaged snacks, including fried foods and sweets. Pries et al., (2019) [21] conducted a multicountry analysis and found that sugar sweetened beverages and snack foods are increasingly consumed by children aged 6-23 months in low and middle income countries, particularly due to marketing and availability. Monteiro et al., (2023) [14] warned about the rise in ultra-processed food consumption among toddlers in urban areas and its association with nutrient displacement and risk of metabolic diseases. A study in Mumbai highlighted that many mothers introduced packaged infant cereals, fruit juices, and biscuits before 12 months of age, due to aggressive marketing and lack of awareness about appropriate feeding. The data shows that 66.8 per cent of mothers stayed with the child during feeding, while 33.2 per cent do not (Table 7). This indicates that a significant proportion of mothers actively supervise or assist feeding, a practice considered beneficial for both nutritional intake and mother child bonding. During episodes of illness, 75 per cent of mothers reported feeding the child slowly and patiently, while 25 per cent offered the child's favorite foods. Notably, no mothers reported force feeding the child, which reflects a positive and responsive feeding approach (Table 8). These findings align well with the World Health Organization (WHO, 2021) [30] recommendations, which emphasize responsive feeding practices such as being patient, encouraging but not forcing, and modifying food preferences during sickness. A study by Nguyen et al., (2013) [18] in South Asia found that caregivers who stayed with the child during meals and practiced patient feeding were more likely to have children with better growth indicators. Similarly, Abeshu et al., (2016) [1] in Ethiopia reported that responsive feeding during illness improved nutrient intake and reduced the risk of malnutrition. The absence of force-feeding in this sample may be attributed to increased awareness or changing cultural attitudes towards child autonomy during feeding. This is encouraging, as force-feeding has been linked to negative outcomes such as food aversions, poor appetite regulation, and long-term eating disorders (Ventura and Birch, 2008) [26] . The data in table 8 provides insights into feeding hygiene practices among mothers of children. Three key areas were assessed: type of feeding utensils used, sterilization practices, and hand hygiene before feeding. Bowl and spoon feeding were the most common method (42.4%), followed closely by hand feeding (40.2%). Feeding bottles were used by only 17.4 per cent of mothers. A study by Taneja et al., (2015) [23] in India similarly observed that bottle feeding was used by 20-25 per cent of mothers, while spoon and hand feeding remained more common in rural and semi-urban areas. Bottle-feeding, while convenient, is often linked with increased risks of diarrheal diseases due to difficulties in maintaining sterility. Only 11.1 per cent of mothers sterilized feeding utensils, while a striking 88.9 per cent did not. This finding raises concern, especially considering that poor utensil hygiene is a major contributor to infant gastrointestinal infections. Black et al., (2013) [3] found that inadequate sterilization of feeding tools was significantly associated with higher incidence of diarrhea and stunting in children under two years in low-income settings. This emphasizes the urgent need for community education on basic food hygiene, especially when animal milk or semi-solid complementary foods are used. Majority of mothers (71.5%) washed their hands with soap before feeding, whereas 28.5 per cent did not. This represents a moderately good practice, though the gap suggests continued room for improvement. According to Curtis et al., (2000), hand washing with soap can reduce the risk of diarrheal disease by up to 47 per cent, making it one of the simplest yet most effective public health interventions for children under five. The findings suggest generally appropriate feeding utensil choices, but highlight critical gaps in sterilization and hand hygiene practices.
| Hygiene during feeding | Categories | Frequency | Percentage |
|---|---|---|---|
| Type of feeding Utensils | Feeding bottles | 64 | 17.4 |
| Bowl and spoon | 156 | 42.4 | |
| Hand feeding | 148 | 40.2 | |
| Sterilization of utensils | Yes | 41 | 11.1 |
| No | 327 | 88.9 | |
| Hand wash with soap before feeding | Yes | 263 | 71.5 |
| No | 105 | 28.5 |
Table text extracted from the original PDF; superscript letters are shown inline. The original table image is below.
View original table image
| Ways of complementary feeding | Categories | Frequency | Percentage |
|---|---|---|---|
| Stay with child | Yes | 246 | 66.8 |
| No | 122 | 33.2 | |
| Feeding child during sickness | Feed slowly and patiently | 276 | 75.0 |
| Give favorite foods | 92 | 25.0 | |
| Feed the child forcefully | 00 | 00 |
Table text extracted from the original PDF; superscript letters are shown inline. The original table image is below.
View original table image
| Indicators | Categories | Frequency | Percentage |
|---|---|---|---|
| Complementary feeding practices | Appropriate complementary feeding | 41 | 11.1 |
| Poor complementary feeding | 327 | 88.9 |
Table text extracted from the original PDF; superscript letters are shown inline. The original table image is below.
View original table image
| Variables | Sub-variables | Frequency | Percentage |
|---|---|---|---|
| Age (Years) | 20-25 | 181 | 49.2 |
| 26-30 | 95 | 25.8 | |
| 31-35 | 63 | 17.1 | |
| 36-40 | 29 | 07.9 | |
| Religion | Hindu | 348 | 94.6 |
| Muslim | 20 | 05.4 | |
| Christian | 00 | 00 | |
| Education | Illiterate | 35 | 09.5 |
| Primary | 94 | 25.5 | |
| Secondary | 133 | 36.1 | |
| Higher secondary | 35 | 09.5 | |
| Graduate | 39 | 10.6 | |
| Post Graduate and Above | 32 | 08.7 | |
| Type of Work | Government Service | 19 | 05.2 |
| Private Job | 02 | 00.5 | |
| Labour | 40 | 10.9 | |
| Farming | 14 | 03.8 | |
| Farming + Livestock | 65 | 17.7 | |
| Homemaker | 228 | 62 | |
| Nature of Work | Sedentary | 165 | 44.8 |
| Moderate | 68 | 18.5 | |
| Heavy | 135 | 36.7 |
Table text extracted from the original PDF; superscript letters are shown inline. The original table image is below.
View original table image
Given the vulnerability of infants to foodborne pathogens, especially during the weaning period, improved mother education on hygiene protocols is essential. The socio economic status (SES) of mothers is a significant determinant of complementary feeding practices among children aged 6-24 months. In the current analysis, a positive association was observed between higher SES and improved complementary feeding behaviors (Table 9). The analysis revealed a statistically significant association between the socio economic status of mothers and complementary feeding practices among children, as indicated by a chi-square value of 34.464 (p<0.001). This suggests that complementary feeding practices significantly vary with maternal socio-economic status (Table 9). Among mothers from the upper socio economic class, 40 per cent practiced appropriate complementary feeding, which includes timely initiation (at 6 months), adequate meal frequency, and dietary diversity. In contrast, no mothers from the lower socio economic class were found to follow appropriate feeding practices 100 per cent had poor feeding practices. A large proportion of mothers from the middle class (198 out of 221) also demonstrated poor practices, with only 23 following appropriate guidelines. These findings highlight that higher socio economic status is positively associated with better complementary feeding behaviors. Mothers in upper income households are more likely to be educated, have better access to health information and services, and can afford a diverse range of nutritious foods. On the other hand, mothers from lower socio-economic groups may face constraints related to poverty, food insecurity, and lack of awareness, which severely impact their ability to adhere to WHO recommended feeding practices.
| Variable | Complementary feeding practices | — | — | — | — | — |
|---|---|---|---|---|---|---|
| Appropriate | Poor | Chi-square test | P-Value | |||
| Socio Economic Status | F | % | F | % | 34.464*** | p<0.001 |
| Upper class | 18 | 4.89 | 40 | 10.88 | ||
| Middle class | 23 | 6.25 | 198 | 53.80 | ||
| Lower class | 00 | 00 | 89 | 24.18 |
Table text extracted from the original PDF; superscript letters are shown inline. The original table image is below.
View original table image
This association supports existing literature, where maternal education, income, and living conditions are found to influence infant and young child feeding behaviors (Senarath et al., 2012; Kanjilal et al., 2020) [22,7] . The findings underscore the need for targeted nutrition education and food support interventions for economically disadvantaged families to bridge the gap in feeding practices and improve child nutritional outcomes. The analysis of complementary feeding practices in relation to maternal education revealed a highly significant association (Chi-square=62.488, p<0.001), indicating that the level of maternal education greatly influences children feeding behavior. Among illiterate mothers, none practiced appropriate complementary feeding, and 9.51 per cent followed poor practices. A similar trend was noted among those with only primary or secondary education, where poor practices were predominant (22.28% and 34.51%, respectively), while appropriate practices were minimal. However, as the education level increased, the proportion of appropriate feeding practices also improved. Notably, mothers with postgraduate education and above showed the highest percentage of appropriate feeding practices (4.35%) and an equal proportion with poor practices, reflecting a more balanced and informed approach. This trend underscores the role of maternal education in enhancing knowledge and adoption of recommended infant and young child feeding (IYCF) guidelines (Table 10).
| Variable | Complementary feeding practices | — | — | — | — | — |
|---|---|---|---|---|---|---|
| Appropriate | Poor | Chi-square test | P-Value | |||
| Education | F | % | F | % | 62.488*** | p<0.001 |
| Illiterate | 00 | 00 | 35 | 9.51 | ||
| Primary | 12 | 3.26 | 82 | 22.28 | ||
| Secondary | 06 | 1.63 | 127 | 34.51 | ||
| Higher secondary | 01 | 0.27 | 34 | 9.24 | ||
| Graduate | 06 | 1.63 | 33 | 8.97 | ||
| Post graduate and Above | 16 | 4.35 | 16 | 4.35 |
Table text extracted from the original PDF; superscript letters are shown inline. The original table image is below.
View original table image
The findings are consistent with several other studies that highlight maternal education as a key determinant of child nutrition. For instance, Nguyen et al., (2017) [17] reported a strong positive correlation between maternal education and dietary diversity among children in Bangladesh, Vietnam, and Ethiopia. Educated mothers were more likely to introduce a variety of food groups, improving overall dietary quality. Similarly, Kumar et al., (2019) [11] emphasized that mothers with higher education levels are better positioned to translate nutritional knowledge into practical feeding behaviors, particularly in resource constrained settings. In the Indian context, Patel et al., (2021) [19] found that maternal education significantly influenced the adoption of appropriate complementary feeding practices, especially in rural areas. These studies collectively support the current findings, reinforcing that improving women's education may serve as a long-term strategy to combat under nutrition and poor feeding practices in low-and middle-income countries. 11 presents the relationship between the type of maternal occupation and the quality of complementary feeding practices among children. Overall, complementary feeding practices were found to be significantly associated with maternal occupation, as evidenced by a chi-square test value of 101.594 and a p<0.001, indicating highly statistical significance. Among homemakers only 1.90 per cent children received appropriate complementary feeding, while a staggering 60.05 per cent received poor feeding. Mothers engaged in farming combined with livestock rearing showed better outcomes, with 7.33 per cent children receiving appropriate feeding and 10.33 per cent receiving poor feeding. Those solely involved in farming reported 1.08 per cent cases of appropriate and 2.72 per cent of poor feeding.
In stark contrast, none of the children of laborer mothers received appropriate feeding; all 10.88 per cent had poor complementary feeding practices. Mothers in government service had only 0.27 per cent child receiving appropriate feeding and 4.89 per cent receiving poor feeding, whereas private job holders had 0.55 per cent children with appropriate practices and none with poor feeding. The findings strongly indicate that maternal occupation is a critical determinant of complementary feeding practices, with homemakers and laborers showing significantly poorer outcomes. Although homemakers theoretically have more time to care for children, the data suggests that this group may lack nutritional knowledge, empowerment, or decisionmaking power related to child feeding. The complete absence of appropriate feeding among laborers' children is particularly concerning and highlights how economic hardship and long working hours negatively impact feeding practices.
Mothers engaged in farming with livestock performed better, possibly due to access to homegrown and animalbased food sources, which facilitate better feeding diversity and frequency. Conversely, mothers in formal employment (government/private) showed a mixed picture. Private Job holders had a small sample but fared relatively well, potentially reflecting better education and nutritional awareness. These results align with findings from Senarath et al., (2012) [22] , who reported that mothers involved in agriculture or unskilled labor had significantly lower odds of practicing appropriate complementary feeding. Similarly, Vijayaraghavan et al., (2020) [27] found that maternal knowledge and employment status were key determinants of child feeding behaviors in rural India. Another study by Khan et al., (2017) to nutrition education and health services often linked with formal jobs-were more likely to meet complementary feeding standards. This study underscores the importance of targeted nutrition education programs, particularly for homemakers and informal workers, and highlights the need to improve livelihood opportunities and health awareness for better child nutrition outcomes.
Conclusion
This study reveals critical gaps in complementary feeding practices among children aged 6-24 months, with most failing to meet WHO standards. Poor dietary diversity, delayed feeding, and high intake of unhealthy foods were common, despite continued breastfeeding. Socio-economic status, maternal education, and occupation significantly influenced feeding behaviors mothers from higher-income or educated backgrounds practiced better feeding. Hygiene practices, especially utensil sterilization, were also inadequate. These findings highlight the need for targeted nutrition education and support programs for low-income, less educated, and informal working mothers to improve child nutrition and health outcomes.
Figures and tables from the paper
| Components | Sub Components | Frequency | Percentage |
|---|---|---|---|
| Caste | Scheduled Caste | 196 | 53.3 |
| Other Backward Class | 123 | 33.4 | |
| General | 49 | 13.3 | |
| Occupation | Labour | 142 | 38.6 |
| Caste Occupation | 100 | 27.2 | |
| Business | 28 | 07.6 | |
| Independent Profession | 73 | 19.8 | |
| Service | 25 | 06.8 | |
| Family Income (Rs./month) | < 1000 | 00 | 00 |
| 1000-5000 | 97 | 26.4 | |
| 5000-10,000 | 187 | 50.8 | |
| 10,000-15,000 | 38 | 10.3 | |
| 15,000-20,000 | 13 | 03.5 | |
| > 20,000 | 33 | 09.0 | |
| Education | Illiterate | 03 | 0.8 |
| Can read only | 00 | 00 | |
| Can read and write | 13 | 03.5 | |
| Primary | 62 | 16.8 | |
| Middle | 192 | 52.2 | |
| High School | 65 | 17.7 | |
| Intermediate | 05 | 01.4 | |
| Graduate and above | 28 | 07.6 | |
| Social Participation | None | 323 | 87.8 |
| Member of one Organization | 45 | 12.2 | |
| Member of more than one organization | 00 | 00 | |
| Office holder | 00 | 00 | |
| Wider public leader | 00 | 00 | |
| Land | No land | 201 | 54.6 |
| Up to 2.00 ha | 166 | 45.2 | |
| 2.01 to 4.00 ha | 01 | 0.3 | |
| 4.01 to 10.00 ha | 00 | 00 | |
| Above 10.00 ha | 00 | 00 | |
| House | No House (Rented) | 46 | 12.5 |
| Hut | 00 | 00 | |
| Kaccha house | 00 | 00 | |
| Mixed house | 153 | 41.6 | |
| Pacca house | 169 | 45.9 | |
| Material possession | Motor Cycle/Mobile | 95 | 25.8 |
| Motor Cycle+Mobile | 00 | 00 | |
| Motor Cycle+Mobile+Television | 114 | 31.0 | |
| Motor Cycle + Mobile + Television+Refrigerator/Tractor /Improved/Agriculture Implements | 159 | 43.2 | |
| Family type | Single | 129 | 35.1 |
| Joint | 239 | 64.9 |
Table text extracted from the original PDF; superscript letters are shown inline. The original table image is below.
View original table image
| Category | Frequency | Percentage | Mean | SD |
|---|---|---|---|---|
| Upper class (≥24.08) | 58 | 15.8 | 18.71 | 5.366 |
| Middle class (13.35-24.07) | 221 | 60.1 | ||
| Lower class (≤13.34) | 89 | 24.2 |
Table text extracted from the original PDF; superscript letters are shown inline. The original table image is below.
View original table image
| Complementary feeding practice | Total (N=368) | — | Currently breastfed children (n1=237) | — | Currently non-breastfed children (n2=131) | — |
|---|---|---|---|---|---|---|
| F | % | F | % | F | % | |
| Introduction of solid, semi-solid or soft foods 6-8 months (ISSSF) (N=85) (in past 24 hrs.) | ||||||
| Yes | 39 | 45.9 | 39 | 48.8 | 00 | 00 |
| No | 46 | 54.1 | 41 | 51.2 | 05 | 100 |
| Minimum Dietary Diversity (MDD), (in past 24 hrs.) | ||||||
| Yes | 132 | 35.9 | 65 | 27.4 | 67 | 51.1 |
| No | 236 | 64.1 | 172 | 72.6 | 64 | 48.9 |
| Minimum Meal Frequency (MMF), (in past 24 hrs.) | ||||||
| Yes | 214 | 58.2 | 153 | 64.6 | 61 | 46.6 |
| No | 154 | 41.8 | 84 | 35.4 | 70 | 53.4 |
| Minimum Acceptable Diet (MAD), (in past 24 hrs.) | ||||||
| Yes | 106 | 28.8 | 56 | 23.6 | 50 | 38.2 |
| No | 262 | 71.2 | 181 | 76.4 | 81 | 61.8 |
| Consumption of egg and/or flesh food (in past 24 hrs.) | ||||||
| Yes | 05 | 01.4 | 05 | 02.1 | 00 | 00 |
| No | 363 | 98.6 | 232 | 97.9 | 131 | 100 |
| Consumption of sweet beverages (in past 24 hrs.) | ||||||
| Yes | 92 | 25.0 | 30 | 12.7 | 62 | 47.3 |
| No | 276 | 75.0 | 207 | 87.3 | 69 | 52.7 |
| Consumption of unhealthy food (in past 24 hrs.) | ||||||
| Yes | 242 | 65.8 | 227 | 95.8 | 109 | 83.2 |
| No | 126 | 34.2 | 104 | 43.9 | 22 | 16.8 |
Table text extracted from the original PDF; superscript letters are shown inline. The original table image is below.
View original table image
| Sentinel unhealthy foods a | Frequency | Percentage |
|---|---|---|
| Sweet and sugar confections | 28 | 07.61 |
| Frozen treats | 21 | 05.7 |
| Baked and fried confections | 102 | 27.7 |
| Chips and crisps | 41 | 11.14 |
| Sugar and sweetened beverages | 92 | 25.0 |
| Processed meats | 00 | 00 |
| Fast foods | 00 | 00 |
| Not consumed | 126 | 34.2 |
Table text extracted from the original PDF; superscript letters are shown inline. The original table image is below.
View original table image
| Variable | Complementary feeding practices | — | — | — | — | — |
|---|---|---|---|---|---|---|
| Appropriate | Poor | Chi-square Test | P-Value | |||
| Type of work | F | % | F | % | 101.594*** | p<0.001 |
| Government Service | 01 | 0.27 | 18 | 4.89 | ||
| Private job | 02 | 0.55 | 00 | 00 | ||
| Labour | 00 | 00 | 40 | 10.88 | ||
| Farming | 04 | 1.08 | 10 | 2.72 | ||
| Farming + Livestock | 27 | 7.33 | 38 | 10.33 | ||
| Homemaker | 07 | 1.90 | 221 | 60.05 |
Table text extracted from the original PDF; superscript letters are shown inline. The original table image is below.
View original table image
References
30 in the original paper- Abeshu MA, Lelisa A, Geleta B. Complementary feeding: Review of recommendations, feeding practices, and adequacy of homemade complementary food preparations in developing countries-lessons from Ethiopia. Front Nutr. 2016;3:41-41.
- Agarwal S, Kim R, Sharma S, Sharma S, Subramanian SV. Consumption of processed foods by urban children under 2 years of age in India: Patterns and determinants. Matern Child Nutr. 2020;16(3):e12951e12951.
- Black RE, Victora CG, Walker SP, Bhutta ZA, Christian P, Onis DM, et al. Maternal and child under nutrition and overweight in low-income and middle-income countries. Lancet. 2013;382(9890):427451.
- Curtis V, Cairncross S. Effect of washing hands with soap on diarrhoea risk in the community: A systematic review. Lancet Infect Dis. 2003;3(5):275-281.
- Gupta SP, Kapoor VK. Fundamentals of Applied Statistics. 4 th Ed. Sultan Chand & Sons; 2002.
- Joshi N, Agho KE, Dibley MJ, Senarath U, Tiwari K. Determinants of inappropriate complementary feeding practices in young children in Nepal: Secondary data analysis of Demographic and Health Survey 2016. Matern Child Nutr. 2020;16(2):e12973-e12973.
- Kanjilal B, Mazumdar PG, Mukherjee M, Rahman MH. Nutritional status of children in India: Household socio economic condition as the contextual determinant. Int J Equity Health. 2020;19(1):216-216.
- Khan AM, Kayina P, Agrawal P, Gupta A, Kaur S. A study on infant and young child feeding practices among mothers attending an urban health center in East Delhi. Indian J Public Health. 2012;56(4):301-304.
- Khan GN, Ariff S, Khan U, Habib A, Umer M, Suhag Z, et al. Determinants of complementary feeding practices among infants and young children in Pakistan: Secondary data analysis of Demographic and Health Survey 2012-13. Food Nutr Bull. 2019;40(2):119-129.
- Kulkarni B, Chauhan AS, Gadgil M, Chiplunkar S, Kapadia-Kundu N. Marketing and early introduction of packaged foods among infants in Mumbai: A qualitative study. Indian J Public Health. 2022;66(1):1015.
- Kumar D, Goel NK, Mittal PC, Misra P. Influence of infant-feeding practices on nutritional status of under five children. Indian J Pediatr. 2019;86(3):262-265.
- Kundu S, Bhowmick D, Roy S. Complementary feeding practices among mothers of children aged 623 months in rural West Bengal, India. J Fam Med Prim Care. 2020;9(9):4638-4644.
- Ministry of Health and Family Welfare (MoHFW). National Family Health Survey (NFHS-5), India, 201921. Mumbai: International Institute for Population Sciences (IIPS); 2021.
- Monteiro CA, Cannon G, Moubarac JC, Levy RB, Louzada ML, Jaime PC. The UN Decade of Nutrition, the NOVA food classification and the trouble with ultra-processing. Public Health Nutr. 2023;26(3):456465.
- National Family Health Survey (NFHS-5), Gujarat State Report 2019-21. Ministry of Health and Family Welfare, Government of India; 2021.
- National Family Health Survey (NFHS-5), India 2019-21. Ministry of Health and Family Welfare, Government of India; 2021.
- Nguyen PH, Avula R, Headey D, Tran LM, Ruel MT, Menon P. Maternal and child dietary diversity are associated in Bangladesh, Vietnam, and Ethiopia. J Nutr. 2017;147(5):938-947.
- Nguyen PH, Avula R, Ruel MT, Saha KK, Ali D, Tran LM, et al. Maternal and child dietary diversity are associated in Bangladesh, Vietnam, and Ethiopia. J Nutr. 2013;143(7):1176-1183.
- Patel A, Pusdekar YV, Badhoniya N, Borkar J, Agho KE, Dibley MJ. Determinants of inappropriate complementary feeding practices in young children in India: Secondary analysis of national family health survey 2005-2006. Matern Child Nutr. 2021;17(1):e13022-e13022.
- Poti JM, Mendez MA, Ng SW, Popkin BM. Is the degree of food processing and convenience linked with the nutritional quality of foods purchased by US households?, Am J Clin Nutr. 2017;101(6):1251-1262.
- Pries AM, Filteau S, Ferguson EL. Snack food and beverage consumption and young child nutrition in lowand middle-income countries: A systematic review. Matern Child Nutr. 2019;15(S4):e12729-e12729.
- Senarath U, Agho KE, Akram DS, Godakandage SS, Hazir T, Jayawickrama H. Comparisons of complementary feeding indicators and associated factors in children aged 6-23 months across five South Asian countries. Matern Child Nutr. 2012;8(Suppl 1):89-106.
- Taneja DK, Misra A, Mathur NB, Mishra P, Jain S. Infant and young child feeding practices among children under two years of age: Findings from a cross-sectional study in a rural area of Delhi. Indian J Public Health. 2015;59(1):18-22.
- Tiwari R, Sharma S, Mishra P, Yadav A. Complementary feeding practices and associated factors among mothers of children aged 6-23 months in Madhya Pradesh, India. Int. J Community Med Public Health. 2022;9(3):1205-1210.
- Pareek U, Trivedi OP. Manual of socio-economic status scale (rural). 1 st Ed. Manasayan; 1964.
- Ventura AK, Birch LL. Does parenting affect children's eating and weight status? Int J Behav Nutr Phys Act. 2008;5:15-15.
- Vijayaraghavan K, Thomas T, Kurpad AV. Influence of maternal knowledge and employment on infant and young child feeding practices in rural South India. Int J Child Health Nutr. 2020;9(1):1-9.
- World Health Organization, UNICEF. Indicators for assessing infant and young child feeding practices: Part 1 Definitions. Geneva: WHO; 2021.
- World Health Organization. Guiding principles for feeding non-breastfed children 6-24 months of age. Geneva: WHO; 2021.
- World Health Organization. Infant and young child feeding: Model Chapter for textbooks for medical students and allied health professionals. Geneva: WHO; 2021.