
Research article · 2025 · Full text
International Journal of Veterinary Sciences and Animal HusbandrySuccessful management of dermatological disorder due to Microsporum canis in a persian cat
Volume 10(1) · Pages 97–99 · DOI: 10.22271/veterinary.2025.v10.i1b.2000 ↗
Research areasNail Diseases and TreatmentsToxin Mechanisms and ImmunotoxinsHerpesvirus Infections and Treatments
Abstract
Author-writtenFeline dermatophytosis is caused by superficial fungal infection of keratinized cutaneous structures in cats. Microsporum canis is the most common and important cause of dermatophytosis in cats, due to its pathogenicity and significant zoonotic potential. A persian cat was presented with history of almost complete alopecia, pruritis and crusting. The cat initially had localised patchy alopecia and was treated previously for the past 6 months with antibiotics and anti-inflammatory ointments. There was no improvement and gradual worsening of the condition was evident. Dermatological examination, revealed alopecia with sparse hair on extremities, crusting, scaling and intense pruritis. Other vitals were normal. Routine diagnostic examinations such as skin scrapings, coat brushings and trichogram revealed no abnormalities while Wood’s lamp examination revealed apple green fluorescence. Hematological and Serum Biochemical examination revealed mild leucocytosis with mild neutrophilia. Fungal culture with hair pluck revealed Microsporum canis. The cat was diagnosed to have dermatophytosis due to M. canis. Treatment was started on itraconazole orally (@ 5 mg/kg once daily) on a “week on – week off” basis along with oral and topical supportive medications. The cat showed improvement from 3rd week and hair coat showed remarkable improvement in 12 weeks.
Summary
Source-checkedPlain-language reading of the full paper, prepared with AI and checked against the text. Each point links to the authors' own words.
Why it matters
- Feline dermatophytosis is a superficial fungal infection that affects the keratinized cutaneous structures of a cat's skin. View evidence ↗
- Microsporum canis is the most frequent and significant cause of this condition because it is pathogenic and can be transmitted to humans (zoonotic potential). View evidence ↗
- The disease often presents with various skin signs, most commonly multifocal patches of hair loss (alopecia) and scaling, which can lead to misdiagnosis without proper testing. View evidence ↗
The question
- The study aimed to manage a dermatological disorder in a Persian cat presenting with almost complete hair loss, itching (pruritis), and crusting. View evidence ↗
What they did
- The subject was a three-year-old female Persian cat. View evidence ↗
- Diagnostic methods included skin scraping, coat brushing, tape impression, trichogram, direct impression, and Wood's lamp examination. View evidence ↗
- Hair samples were cultured on Sabouraud Dextrose Agar to identify the fungal agent. View evidence ↗
- The treatment regimen consisted of oral Itraconazole at 10mg/kg daily for 28 days, followed by 5mg/kg for 5 weeks on a 'week on-week off' basis, repeated for 3 cycles. View evidence ↗
- Supportive care included daily oral Silymarin (10mg/kg) to protect the liver from Itraconazole toxicity and Omega-3 fatty acid supplements (2.5ml every 12 hours). View evidence ↗
- Topical treatments included 1% Terbinafine cream daily for 4 weeks and a weekly shampoo containing 2% Miconazole and 2% Chlorhexidine. View evidence ↗
What they found
- Initial Wood's lamp examination showed apple green fluorescence in the hairs, indicating dermatophytosis. View evidence ↗
- Fungal culture of hair plucks confirmed the infection was caused by Microsporum canis. View evidence ↗
- After four weeks of treatment, the cat showed visible hair regrowth and a reduction in apple green fluorescence. View evidence ↗
- By week 12, the hair coat had returned to normal and apple green fluorescence was no longer evident. View evidence ↗
What it means
- The authors conclude that accurate and timely diagnosis is essential to start targeted therapy and prevent complications. View evidence ↗
- Misdiagnosing this condition can lead to irreversible skin damage, prolonged animal suffering, and increased zoonotic transmission risk. View evidence ↗
Figures & tables
From the original paper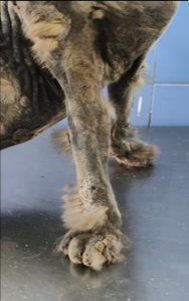 Figure 1
 Figure 1
 Figure 1
 Figure 2
 Figure 2
 Figure 3
 Figure 4A
 Figure 4B
 Figure 4C
Introduction
A three years old female persian cat was presented with history of severe hair loss, itching and crusts on skin (Figure 1). The cat was already treated elsewhere with systemic antibiotics and anti-inflammatory ointments for a prolonged period of time. On physical examination, the rectal temperature was normal (102.2°F) and heart rate was 150bpm. Dermatological examination, namely skin scraping, coat brushing, tape impression, trichogram, direct impression, wood’s lamp examination was performed (Gross et al., 2005) [1], out of which the wood’s lamp examination revealed apple green fluorescence in the hairs (Figure 2), indicating the presence of dermatophytosis.
Haematological and Serum biochemical parameters were normal. The hair samples were subjected to fungal culture on Sabouraud Dextrose Agar, and a white fluffy colony was present in the centre (Figure 3), confirming dermatophytosis due to Microsporum canis infection (Mariello, 2019) [4]. The cat was treated with Itraconazole @ 10mg/kg b.wt once a day orally, for a period of 28 days, followed by 5mh/kg b.wt for 5 weeks on a “Week on-week off” basis. The treatment was repeated for 3 cycles (Puls et al., 2017) [2].
Silymarin, a hepatic cytoprotectant, was administered @ 10mg/kg once every day orally, to counteract the hepatotoxic effects of long-term administration of itraconazole. An Ω – 3 fatty acid supplement was administered @ 2.5ml orally every 12 hours. Topical therapy was advised by administering Terbinafine cream – 1% w/w, once a day for 4 weeks, and a shampoo consisting of Miconazole (2% w/v) and Chlorhexidine (2% w/v), once a week. Environmental hygiene was advised by washing the dwelling areas of the cat with bleach (1:100 dilution with water) and isolation of affected cat.
VET 2025; 10(1): 97-99 David Karunyakaran H MVSc, Scholar, Department of Veterinary Clinical Medicine, Madras Veterinary College, Tamil Nadu Veterinary and Animal Sciences University, Chennai, Tamil Nadu, India Sandhya Bhavani M Assistant Professor, Department of Clinics, Madras Veterinary College, Tamil Nadu Veterinary and Animal Sciences University, Chennai, Tamil Nadu, India Kavitha S Professor and Head, Department of Veterinary Clinical Medicine, Madras Veterinary College, Tamil Nadu Veterinary and Animal Sciences University, Chennai, Tamil Nadu, India Vijayakumar G Professor and Head, Department of Clinics, Madras Veterinary College, Tamil Nadu Veterinary and Animal Sciences University, Chennai, Tamil Nadu, India Aravindh G Undergraduate Scholar, Madras Veterinary College, Chennai, Tamil Nadu, India David Karunyakaran H MVSc, Scholar, Department of Veterinary Clinical Medicine, Madras Veterinary College, Tamil Nadu Veterinary and Animal Sciences University, Chennai, Tamil Nadu, India https://www.veterinarypaper.com apple green fluorescence in Wood’s lamp examination (Figure 4b). On week 12, the hair coat is back to normal and there was no apple green fluorescence evident on Wood’s lamp examination (Figure 4c). The animal was presented for follow-up, after four weeks of treatment. There was visible hair growth (Figure 4a), and there was visible reduction in apple green fluorescence in Wood’s lamp examination.
On week 8, there was a remarkable improvement in hair growth and great reduction in Fig 1: Severe alopecia and crusting on the entire body (1a), Legs (1b), ears (1c) and face (1d) Fig 3: SDA agar-cloudy white colony Fig 2: Apple green fluorescence visualized in the hairs during Wood’s lamp examination on the body (Fig2a) and face (Fig 2b) Fig 4a Fig 4b Fig 4c Fig 4: Recovery of the cat at 4th week (Fig 4a), 8th week (Fig 4b), and 12th week (Figure 4c). Over the period of 12 weeks, there is regrowth of hair and reduction in the crusty lesions https://www.veterinarypaper.com Creative Commons (CC) License This is an open-access journal, and articles are distributed under the terms of the Creative Commons Attribution-Non Commercial-Share Alike 4.0 International (CC BY-NC-SA 4.0) License, which allows others to remix, tweak, and build upon the work non-commercially, as long as appropriate credit is given and the new creations are licensed under the identical terms.
Discussion
Feline dermatophytosis is a superficial fungal infection affecting the keratinized cutaneous structures of the skin of cats. It is due to Microsporum canis, which also has zoonotic potential. It may be presented with a large range of potential dermatological signs (most commonly multifocal patches of alopecia with variable scaling), thus lending to misdiagnosis of the condition without appropriate diagnostic testing. Diagnosis of this condition is of utmost importance in order to provide specific therapy.
The disease is treatable and curable once a diagnosis has been established.
Conclusion
The misdiagnosis of feline dermatophytosis for other disorders, can have devastating consequences, leading to irreversible damage to the skin and hair coat, prolonged suffering, and increased risk of transmission to other animals and humans. Therefore, it is imperative to prioritize accurate and timely diagnosis to ensure the initiation of targeted therapy, preventing further complications and promoting successful recovery. Conflicts of interest There are no conflicts of interest. Funding There is no funding for conducting this study Financial Support Not available Reference 1.
Gross TL, Ihrke PJ, Walder EJ, Affolter VK. Skin diseases of the dog and cat – Clinical and histopathological diagnosis. Blackwell Science, 2005. 2. Puls C, Johnson K, Young J, Hare K, Rosenkrans K, Young L, et al.
Efficacy of itraconazole oral solution using an alternate-week pulse therapy regimen for treatment of cats with experimental Microsporum canis infection. J Feline Med Surg. 2017;28(17):869-874. 3. Moriello KA, Coyner K, Paterson S, Mignon B. Diagnosis and treatment of dermatophytosis in dogs and cats.
Vet Dermatol. 2017;28:266-e68. 4. Mariello K. Dermatophytosis in cats and dogs: A practical guide to diagnosis and treatment. In Practice. 2019;41:138-147. 5.
Kauffman M, Kauffman J, Kauffman A. Fungal infections in cats: Diagnosis and treatment. Vet Clin North Am Small Anim Pract. 2018;48(4):751-764. 6. Kauffman M, Kauffman J, Kauffman A.
Dermatophytosis in cats: A review of the literature. J Feline Med Surg. 2019;21(1):3-12. 7. Kauffman M, Kauffman J, Kauffman A. The role of environmental management in the control of dermatophytosis in cats.
Vet Dermatol. 2020;31(1):1-8. 8. Kauffman M, Kauffman J, Kauffman A. Advances in the treatment of dermatophytosis in cats. J Feline Med Surg. 2021;23(1):1-10.
How to Cite This Article Karunyakaran DH, Bhavani SM, Kavitha S, Vijayakumar G. Successful management of dermatological disorder due to Microsporum canis in a persian cat. International Journal of Veterinary Sciences and Animal Husbandry. 2025;10(1):97-99.
References
0 in the original paperCited by 1
From OpenAlex, OpenCitations and reference lists read by Scinovex
- Successful treatment and rehabilitation of burn injury in an Indian Flying Squirrel (Petaurista philippensis) Presented to Veterinary Hospital, Narharpur, Kanker, Chhattisgarh, India
Chitralekha Deo, Tarun Sahu, Upasna Chandrakar · International Journal of Veterinary Sciences and Animal Husbandry · 2026
A wild adult Indian flying squirrel (Petaurista philippensis) was presented to the Veterinary Hospital, Narharpur, Kanker, exhibiting severe thermal burn injuries following accidental exposure to a local fire incident. Clinical examination revealed partial-thickness burns involving twelve to fifteen percent of the total body surface area, specifically affecting the dorsal trunk, tail, and hind limbs. The condition was accompanied by severe dehydration, acute pain, depression, and reduced mobility. The animal was managed systematically through initial fluid stabilization, wound debridement, sys