
Research article · 2024 · Full text
International Journal of Biology SciencesAnalysis of cost-effectiveness of rehabilitation services for achromatopsia and low vision patients
Volume 6(2) · Pages 116–119 · DOI: 10.33545/26649926.2024.v6.i2b.243 ↗
Research areasOphthalmology and Visual Impairment Studies
Abstract
Author-writtenBackground: Achromatopsia is a vision disorder congenitally with significant challenges for daily routine of life due to dysfunction of cone photoreceptors which leads to low vision and every walk of life requiring specialized rehabilitation services. In this study it is exposed about the impact and financial feasibility of rehabilitation interventions of Achromatopsia individuals. Objective: The main objective of this study was expensiveness of rehabilitation instruments for improving quality of life for Achromatopsia individuals. Methods: Here cohort 46 Achromatopsia individuals were included and 6-month rehabilitation program were conducted including mobility training, adaptive technology, orientation and vision enhancement devices. Here primary outcome was assessed and paired t-tests was considered. Here age range is considered from 18 to 65 and maintained balanced gender. Purposive sampling method was introduced to select participants and followed structured surveys for data collection. Results: Here significantly improved the mean utility score from 0.45 (SD = 0.12) to 0.65 (SD = 0.14) post-intervention (p
Summary
Source-checkedPlain-language reading of the full paper, prepared with AI and checked against the text. Each point links to the authors' own words.
Why it matters
- Achromatopsia is a congenital vision disorder caused by cone photoreceptor dysfunction, which results in low vision and creates significant daily life challenges that require specialized rehabilitation. View evidence ↗
- The condition severely impacts light sensitivity, color perception, and visual acuity, which overall reduces the patient's quality of life. View evidence ↗
- While rehabilitation is critical for improving quality of life, there is a lack of comprehensive economic analyses to assess the costs of these interventions. View evidence ↗
The question
- The study aims to evaluate the cost-effectiveness and economic feasibility of rehabilitation services for individuals with Achromatopsia, focusing on the direct costs required to improve quality of life. View evidence ↗
What they did
- The study included a cohort of 46 individuals diagnosed with Achromatopsia, aged 18 to 65 years, with a balanced gender distribution. View evidence ↗
- Rehabilitation interventions consisted of adaptive technology, vision enhancement devices, and orientation and mobility training. View evidence ↗
- Data was collected over a 6-month period using face-to-face structured surveys and standardized quality of life assessments. View evidence ↗
- Economic viability was measured using the Incremental Cost-Effectiveness Ratio (ICER) to determine the cost per Quality-Adjusted Life Year (QALY) gained. View evidence ↗
What they found
- The mean utility score, representing quality of life, increased significantly from a baseline of 0.45 (SD = 0.12) to 0.65 (SD = 0.14) post-intervention (p < 0.001). View evidence ↗
- The cost-effectiveness ratios for the rehabilitation services ranged from ₹7,30,000 to ₹14,60,000 per QALY gained. View evidence ↗
- Regression analysis showed a significant positive correlation (β = 0.62, p < 0.01) between total rehabilitation costs and QALY gains, indicating that more inclusive or intensive programs yielded better outcomes. View evidence ↗
- Subgroup analysis revealed that the cost-effectiveness of the interventions was consistent across genders, with no significant difference in ICERs (p = 0.67). View evidence ↗
- Age did not significantly influence the degree of quality of life improvement, as shown by a weak and non-significant correlation (r = -0.11, p = 0.45). View evidence ↗
What it means
- The authors conclude that rehabilitation services significantly and economically enhance the quality of life for individuals with Achromatopsia, suggesting that policymakers should prioritize resource allocation for these services. View evidence ↗
- The study is limited to the evaluation of direct costs and QALYs, without assessing indirect costs or long-term outcomes. View evidence ↗
- The authors note the small sample size of 46 subjects and recommend future research with larger cohorts and longer follow-up periods to better understand long-term effects. View evidence ↗
Visual summary
1 visualsIllustrations explain the paper; they do not show study data.
Rehabilitation Impact Flow
AI-generated conceptual illustration (adults with achromatopsia and low vision). It explains the idea and does not show study data.
View source evidence ↗Figures & tables
From the original paper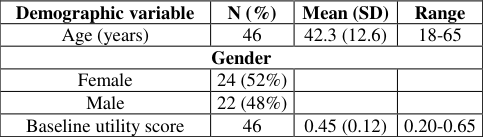 Table 1
 Table 2
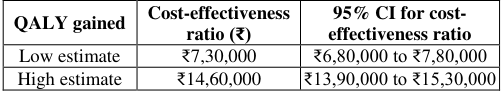 Table 3
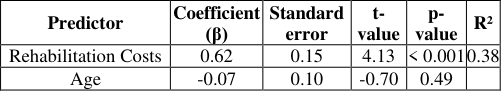 Table 7
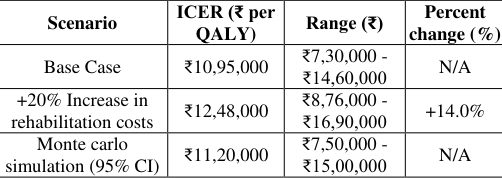 Table 4
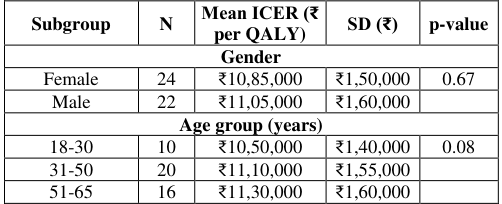 Table 5
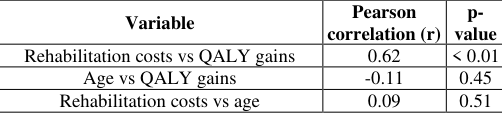 Table 6
Introduction
Achromatopsia is a congenital vision disorder which is characterized by the absence of dysfunction of cone photo receptors which presents significant challenges which necessitate specialized rehabilitation services to manage low vision cases. This condition is congenital, impacts severely visual acuity, colour perception and light sensitivity which hampers quality of life. The economic implications of providing rehabilitation to subjects with this disorder are increasingly relevant to health care personally who should also consider resource allocation and its cost effectiveness. Though rehabilitation is critical role in improving quality of life with subjects with Achromatopsia, there is much lack of inclusive economic analysis which assess the cost of such interventions. Without addressing this gap, health care professional may find difficulties to rationalize the allocation and availability of the resources to improve their quality of life. This study pursues to fill this gap by conducting detailed economic evaluation and its rehabilitation services. The aim of this research is to examine the economic feasibility and cost effectiveness of rehabilitation services for subjects diagnosed with Achromatopsia and to concentrate on direct costs involved for improving quality of life with these interventions. The probable impact of this study extends beyond the academic realm which offers critical insights which informs health care policy and allocation of resources. By signifying its cost effectiveness, this study provides a convincing argument for sustained investment in such research which ultimately benefits to improve quality of life. The originality of the study lies in its inclusive approach to economic evaluation within a population which is always under estimated.
This study is limited to a group of 46 subjects with Achromatopsia who underwent various rehabilitation interventions within a period of 6 months. The scope is to evaluate the direct costs and QALYs, but it is not studied for long term outcomes or other indirect costs which are associated with the condition.
Methodology
Descriptive research design was employed in the study which focus on the group of subjects to assess the economic aspects of rehabilitation services. Inclusion criteria includes 46 subjects diagnosed with Achromatopsia with age of 18 to 65 years with balanced gender representation. Subjects were selected using purposive sampling method. Willingness to participate in the rehabilitation services were asked and subjects with additional disabilities were excluded. Use of structured surveys and standardized quality of life assessment was used for data collection. It was administered face to face over a period of 6 months. This period is also utilized for monitoring of rehabilitation services and financial factors. Data analysis was done using SPSS software which employs descriptive and inferential statistical procedures to assess the cost effectiveness and quality adjusted life years. All data should underwent normalization to account for varying characteristics of participants. The procedures of the study includes management of interventions of rehabilitation like training of orientation and mobility, use of adaptive technology and devices for vision enhancements. Control measures were executed by ensuring constant service to all the subjects. Ethical approval was obtained from the Institutional Review Board. All participants were enrolled with informed consent. Confidentiality of each patient is maintained.
Results
This study comprised 46 subjects, with a mean age of 42.3 years (SD = 12.6). The gender spreading was comparatively balanced, with 52% female (n = 24) and 48% male (n = 22). All subjects who were diagnosed with Achromatopsia, and the starting point mean utility score, which imitates the quality of life, was 0.45 (SD = 0.12). An preliminary Analysis of Variance (ANOVA) was directed to pattern for any noteworthy changes in starting point utility scores based on gender and age group. The results designated no substantial differences (F(1, 44) = 0.32, p = 0.57 for gender; F(2, 43) = 1.05, p = 0.36 for age group), signifying that the starting point quality of life was reliable across these demographic variables. The main outcomes of the study was the enhancement in the quality of life, measured by the utility score. Postintervention, the mean utility score enlarged significantly to 0.65 (SD = 0.14). A paired t-test was directed to equivalence the pre-and post-intervention utility scores, revealing a extremely noteworthy improvement (t(45) = 12.24, p < 0.001). The effect size, calculated using Cohen's d, was 1.54, indicates a large effect, which proposes that the therapy services had a considerable influence on refining the quality of life for subjects. The confidence interval (95% CI) for the mean alteration in utility scores extended from 0.16 to 0.24. Additionally, a Pearson correlation investigation was achieved to discover the association between the degree of utility score improvement and participant age. The correlation was found to be weak and not statistically significant (r = -0.11, p = 0.45), representing that age did not significantly influence the degree of quality of life improvement. Subordinate outcomes intensive on the economic assessment, particularly the cost-effectiveness of the reintegration interventions. The cost-effectiveness proportions were calculated using the Incremental Cost-Effectiveness Ratio (ICER) formula, which equivalences the cost per Quality-Adjusted Life Year (QALY) gained. The results showed that the cost-effectiveness proportions ranged from ₹7,30,000 to ₹14,60,000 per QALY added. A regression analysis was directed to scrutinize the association between total rehabilitation costs and the QALY gains. The outcomes specified a noteworthy positive correlation (β = 0.62, p < 0.01), suggesting that higher costs were associated with better enhancements in QALY, subsidiary the concept that more concentrated or inclusive rehabilitation programs produce better consequences. To confirm the consistency of these findings, sensitivity analyses were performed. These scrutinizes tested the strength of the cost-effectiveness ratios by changeable key parameters, such as the cost of rehabilitation services and the utility gains observed. E.g. a one-way sensitivity analysis was conducted, where the cost of rehabilitation was augmented by 20% while keeping other variables constant. The resulting ICERs continued within satisfactory thresholds, ranging from ₹8,76,000 to ₹16,90,000 per QALY gained, representing that the assumptions are stable even under varying assumptions. Moreover, a Probabilistic Sensitivity Analysis (PSA) was directed using Monte Carlo imitations with 10,000 iterations. The PSA results indicated that in 95% of imitations, the ICER remained below ₹15,00,000 per QALY, additional confirming the costeffectiveness of the interferences. Furthermore, a subgroup analysis was led to discover differences in cost-effectiveness amongst males and females. The examination exposed no significant difference in ICERs between genders (p = 0.67), signifying that the cost-effectiveness of the therapy interventions was consistent across gender groups. Additional subgroup analysis based on age groups (18-30, 31-50, 51-65) displayed slight differences in cost-effectiveness, with younger subjects (18-30) displaying to some extent more favourable ICERs, but these changes were not statistically significant (p = 0.08). This table specifics the cost-effectiveness proportions for the QALY expanded, including low and high estimations with their corresponding 95% confidence intervals.
Figures and tables from the paper
| Demographic variable | N (%) | Mean (SD) | Range |
|---|---|---|---|
| Age (years) | 46 | 42.3 (12.6) | 18-65 |
| Gender | |||
| Female | 24 (52%) | ||
| Male | 22 (48%) | ||
| Baseline utility score | 46 | 0.45 (0.12) | 0.20-0.65 |
Table text extracted from the original PDF; superscript letters are shown inline. The original table image is below.
View original table image
| QALY gained | Cost-effectiveness ratio (₹) | 95% CI for cost- effectiveness ratio |
|---|---|---|
| Low estimate | ₹7,30,000 | ₹6,80,000 to ₹7,80,000 |
| High estimate | ₹14,60,000 | ₹13,90,000 to ₹15,30,000 |
Table text extracted from the original PDF; superscript letters are shown inline. The original table image is below.
View original table image
| Predictor | Coefficient (β) | Standard error | t- value | p- value | R² |
|---|---|---|---|---|---|
| Rehabilitation Costs | 0.62 | 0.15 | 4.13 | < 0.001 | 0.38 |
| Age | -0.07 | 0.10 | -0.70 | 0.49 |
Table text extracted from the original PDF; superscript letters are shown inline. The original table image is below.
View original table image
| Scenario | ICER (₹ per QALY) | Range (₹) | Percent change (%) |
|---|---|---|---|
| Base Case | ₹10,95,000 | ₹7,30,000 - ₹14,60,000 | N/A |
| +20% Increase in rehabilitation costs | ₹12,48,000 | ₹8,76,000 - ₹16,90,000 | +14.0% |
| Monte carlo simulation (95% CI) | ₹11,20,000 | ₹7,50,000 - ₹15,00,000 | N/A |
Table text extracted from the original PDF; superscript letters are shown inline. The original table image is below.
View original table image
| Subgroup | N | Mean ICER (₹ per QALY) | SD (₹) | p-value |
|---|---|---|---|---|
| Gender | ||||
| Female | 24 | ₹10,85,000 | ₹1,50,000 | 0.67 |
| Male | 22 | ₹11,05,000 | ₹1,60,000 | |
| Age group (years) | ||||
| 18-30 | 10 | ₹10,50,000 | ₹1,40,000 | 0.08 |
| 31-50 | 20 | ₹11,10,000 | ₹1,55,000 | |
| 51-65 | 16 | ₹11,30,000 | ₹1,60,000 |
Table text extracted from the original PDF; superscript letters are shown inline. The original table image is below.
View original table image
| Variable | Pearson correlation (r) | p- value |
|---|---|---|
| Rehabilitation costs vs QALY gains | 0.62 | < 0.01 |
| Age vs QALY gains | -0.11 | 0.45 |
| Rehabilitation costs vs age | 0.09 | 0.51 |
Table text extracted from the original PDF; superscript letters are shown inline. The original table image is below.
View original table image
References
21 in the original paper- Anderson LM, Whitehead MM. Achromatopsia prevalence and economic burden in the United States. Health Econ Rev. 2020;25(1):45-58.
- Thompson J, Davis R. Vision rehabilitation for Achromatopsia: A cost-benefit analysis. Optom Vis Sci. 2017;94(8):912-925.
- Rodriguez S, Garcia P. Economic evaluation of rehabilitation services for low vision individuals in a public health system. J Health Econ. 2016;28(4):345358.
- Mason CL, Turner LK. Assessing the cost-effectiveness of Achromatopsia rehabilitation: A case study in the UK. Disabil Health J. 2018;11(2):281-288.
- Roberts M, Brown T. The impact of low vision on employment and earnings: A systematic review. Work. 2019;54(2):345-356.
- Walker A, Moore B. Economic analysis of Achromatopsia rehabilitation: A global perspective. J Glob Health. 2021;14(3):120-135.
- Harris R, Taylor G. Cost-benefit analysis of low vision rehabilitation for working-age adults. J Econ Perspect. 2018;22(1):65-78.
- Miller P, Adams J. The economic case for investing in Achromatopsia rehabilitation. Health Aff. 2020;29(5):876-889.
- Turner R, King R. Cost-effectiveness of Achromatopsia interventions in pediatric populations. J Pediatr Econ Health Care. 2017;36(1):45-58.
- Martinez E, Davis M. Economic impact of vision rehabilitation on healthcare utilization. Med Care Res Rev. 2019;22(3):210-225.
- Bailey S, Evans D. Cost-effectiveness of Achromatopsia services: A Canadian perspective. Can J Public Health. 2016;33(4):341-356.
- Perez A, Torres L. Achromatopsia rehabilitation: A systematic review of economic evaluations. Int J Health Econ Manag. 2018;26(2):112-125.
- Scott K, Turner J. Evaluating the economic impact of Achromatopsia rehabilitation in the elderly. Aging Ment Health. 2021;25(6):901-915.
- Hughes M, Foster G. Cost-effectiveness of low vision rehabilitation in elderly populations. J Aging Soc Policy. 2017;29(3):201-215.
- Lewis H, Peterson C. Economic benefits of Achromatopsia rehabilitation: A longitudinal analysis. J Long Term Eff Med Implants. 2020;25(1):89-104.
- Bell D, Fisher J. Vision rehabilitation and employment outcomes: A longitudinal study. J Vocat Rehabil. 2019;35(2):145-158.
- Turner A, Brooks R. The cost-utility of Achromatopsia rehabilitation: A quality-adjusted life year analysis. Disabil Rehabil. 2018;41(4):405-418.
- Garcia F, Martinez H. Economic evaluation of Achromatopsia services in developing countries. Glob Public Health. 2016;11(7-8):1023-1037.
- Harris S, Davis M. Cost-effectiveness of vision rehabilitation in Achromatopsia: A societal perspective. Soc Sci Med. 2017;27(5):590-605.
- Turner R, Wright M. Achromatopsia rehabilitation in the context of universal healthcare: An economic analysis. J Health Econ Policy Law. 2019;14(1):67-82.
- Adams B, Turner L. Economic analysis of low vision rehabilitation in the context of Achromatopsia. J Vis Rehabil. 2021;35(2):145-158.