
Research article · 2024 · Full text
International Journal of Biology SciencesMacular degenerative changes and observation in the aging population
Volume 6(2) · Pages 91–94 · DOI: 10.33545/26649926.2024.v6.i2b.237 ↗
Research areasRetinal Imaging and Analysis
Abstract
Author-writtenThe objective of our study was to evaluate the current level of knowledge about the pathogenesis, ocular symptoms, diagnosis, and ancillary testing of age-related macular degeneration. Methodology: relevant research on age-related macular degeneration published up to 2014 is used for systematic reviews. Age-related Macular Degeneration (AMD) is a prevalent macular disorder mostly affecting the elderly in the Western world. Geographic atrophy, choroidal neovascularization, and the formation of drusen in the macula are characteristics that set it apart (CNV). The macula is commonly affected by age-related macular degeneration, a prevalent chronic degenerative illness that mostly affects the elderly. Loss of central vision is caused by anomalies in the photoreceptor, retinal pigment epithelium, choroidal complex, Bruch's membrane, and photoreceptor. Geographic atrophy and/or neovascularization are frequently the result of these anomalies. Advanced AMD can be divided into two primary categories: wet and dry. While dry AMD accounts for most diagnosed instances, wet AMD causes the bulk of severe visual loss and often develops over weeks to months. While neovascularization has been demonstrated to be the most common cause of severe vision loss, geographic atrophy, the most advanced form of dry AMD, can also cause a significant loss of vision.
Summary
Source-checkedPlain-language reading of the full paper, prepared with AI and checked against the text. Each point links to the authors' own words.
Why it matters
- Age-related Macular Degeneration (AMD) is a common disorder of the macula that primarily impacts elderly populations in Western countries. View evidence ↗
- AMD is the third leading cause of blindness globally, following cataracts and glaucoma. View evidence ↗
- The loss of central vision in AMD is driven by abnormalities in the choroidal complex, Bruch's membrane, retinal pigment epithelium, and photoreceptors. View evidence ↗
The question
- The study aims to evaluate existing knowledge regarding the diagnosis, symptoms, pathogenesis, and ancillary testing for age-related macular degeneration. View evidence ↗
What they did
- The authors conducted a systematic review using relevant research on AMD published up to the year 2014. View evidence ↗
What they found
- Advanced AMD is uncommon in individuals under 55 but becomes more prevalent in those aged 75 and older. View evidence ↗
- Dry AMD is the most common form diagnosed, but wet AMD is responsible for most severe vision loss and typically progresses over a period of weeks to months. View evidence ↗
- Drusen, an early sign of AMD, typically range in size from 20 to 100 µm and are categorized as either hard or soft. View evidence ↗
- Soft drusen, which have non-discrete borders and a maximum size of 63 µm, are linked to an increased risk of progressing to neovascular AMD. View evidence ↗
- Neovascular AMD is clinically indicated by the presence of intraretinal or subretinal fluid, hemorrhage (retinal, subretinal, or sub-RPE), lipid exudates, RPE rupture or separation, and specific discolorations. View evidence ↗
- Optical coherence tomography (OCT) is identified as a useful diagnostic tool across all stages of AMD. View evidence ↗
- The primary treatment for neovascular AMD consists of intravitreal injections of anti-VEGF medications, including bevacizumab, aflibercept, or ranibizumab. View evidence ↗
What it means
- The authors conclude that early administration of anti-VEGF medication can stabilize or improve vision in many cases. View evidence ↗
Visual summary
1 visualsIllustrations explain the paper; they do not show study data.
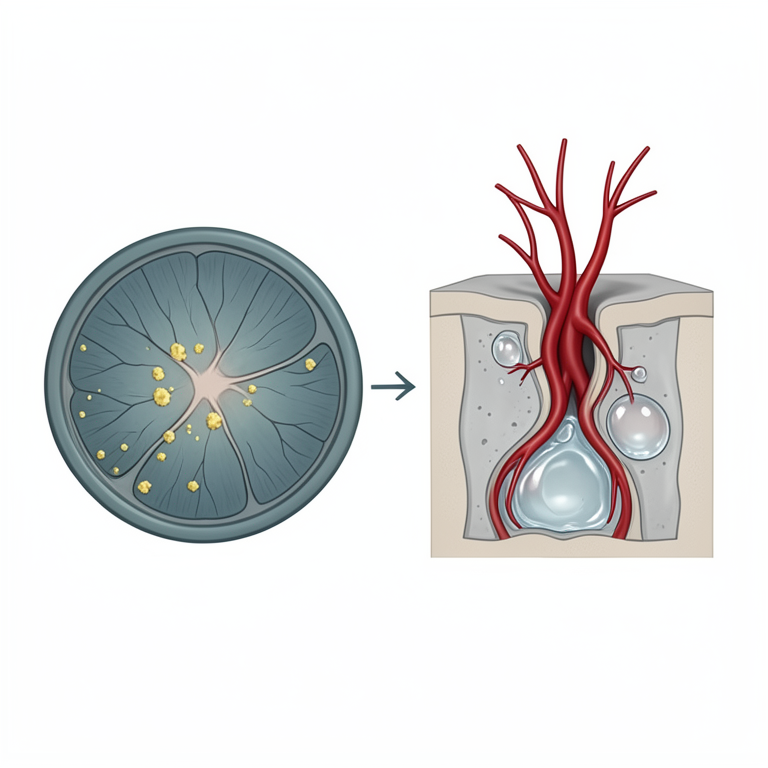
Comparison of Dry vs Wet AMD
AI-generated conceptual illustration (human retina and macula). It explains the idea and does not show study data.
View source evidence ↗Figures & tables
From the original paper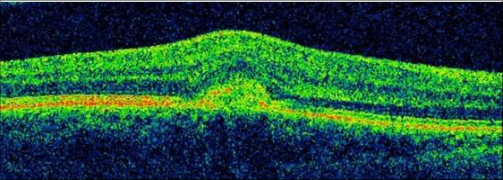 Figure 1
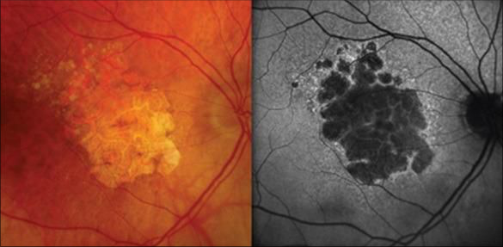 Figure 2
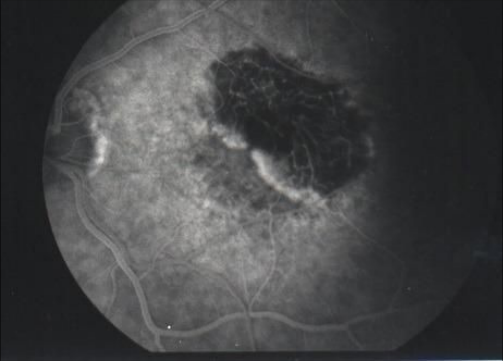 Figure 3
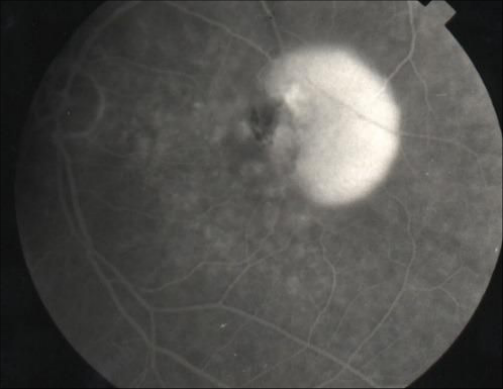 Figure 4
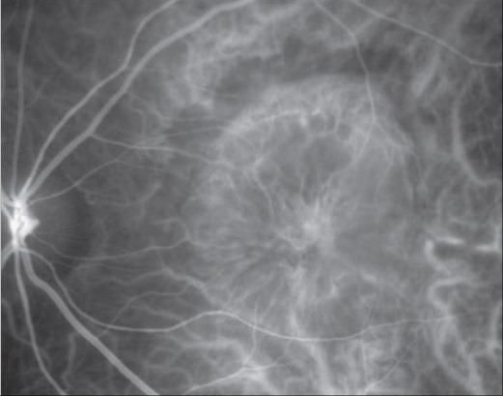 Figure 5
Introduction
The macula is commonly affected by age-related macular degeneration, a prevalent chronic degenerative illness that mostly affects the elderly. Loss of central vision is caused by anomalies in the photoreceptor, retinal pigment epithelium, choroidal complex, Bruch's membrane, and photoreceptor. Geographic atrophy and/or neovascularization are typically the result of these anomalies. Advanced AMD may be divided into two primary categories: wet and dry. While dry AMD accounts for most identified instances, wet AMD causes the bulk of severe visual loss and often develops over weeks to months. While neovascularization has been demonstrated to be the most common cause of severe vision loss, geographic atrophy, the most advanced type of dry AMD, can also cause a significant loss of vision.
Epidemiology
AMD ranks third among the world's main causes of blindness, after glaucoma and cataracts. Most of the people affected live in developed countries. In general, advanced AMD is rare in those under 55 and more prevalent in those 75 years of age and above. The frequency of neovascular AMD and geographic atrophy appears to vary globally across different ethnic and cultural groups. The incidence of advanced AMD increases every ten years beyond the age of fifty and peaks at eighty.
Risk factors
AMD In general, risk factors may be divided into two categories: environmental and personal (Such as smoking, sun exposure, and dietary intake of fish, micronutrients, and alcohol).
Personal factors can be further subdivided into the following categories: sociodemographic (Such as age, sex, race/ethnicity, heredity, and socioeconomic status); ocular (Such as iris color, macular pigment optical density, cataract and its surgery, refractive error, and cup/disc ratio); and systemic (Such as cardiovascular disease and its risk factors, reproductive and related factors, dermal elastotic degeneration, and antioxidant enzymes). Factors that put choroidal neovascularization development at risk. The presence of five or more drusen, smoking, hyperpigmentation, systemic hypertension, and one or more large drusen (Larger than 63 µm in linear dimension) are all present.
Pathogenesis
Currently being employed to provide information on the origin of AMD include molecular dissection of histopathologic specimens and genetic linkage analysis using different populations. Early in the disease phase, lipids are accumulated in Bruch's membrane, most likely due to the RPE's incapacity to manage cellular debris associated with outer segment turnover. Only later in the course of the illness do drusen become apparent. The onset of drusen is the first evident clinical sign of AMD. Lipids, complement factors, amyloid, and other biological components are detected by Drusen analysis [1,2] . The development of drusen is preceded or coincident with the thickening of the collagenous layers of the Bruch's membrane, the calcification of the membrane, the degradation of collagen and elastin within the membrane, the accumulation of lipids and exogenous proteins, and the elevation of advanced glycation end products [3] . These changes may function as a hydrophobic barrier, preventing fluid and nutrients from moving between the outer retina and choroid, leading to relative ischemia. Bruch's membrane breaks may then cause the choriocapillaris to develop and become neovascularized [4] .
Diagnosis and ancillary testing
A clinical examination is usually adequate to confirm a diagnosis of AMD, while additional techniques like as fundus autofluorescence, optical coherence tomography, fluorescein angiography, and indocyanine green angiography are best used to determine mild macular abnormalities. Optical coherence tomography may be a useful additional diagnostic at any stage of AMD. In patients with dry AMD, high-quality B-scans can be performed to assess the ultrastructure of drusen and examine surrounding retinal layers that may be impacted by the disease process. OCT can track the development of early AMD into more severe types, such geographic atrophy. Some characteristics of wet AMD, such as the presence of intraretinal or subretinal fluid and retinal PEDs (which may be categorized as serous, fibrovascular, and hemorrhagic PEDs), can be detected using high quality B-scans. Occult CNV is differentiated by fibrovascular PED or late leaking from an unknown cause using angiography. An region of irregularly elevated RPE, which is neither as bright nor as well-defined as normal CNV, is the hallmark of fibrovascular PED. Midphase angiography may show stippled hyperfluorescence, while late-phase angiography may show leakage or staining [13] .
Classic CNV
The term "classical Choroidal Neovascularization" (CNV) describes the aberrant development of new blood vessels that extend into the subretinal region and originate from the choroid, the vascular layer of the eye. The most typical association between this disorder and Age-related Macular Degeneration (AMD) is with the "wet" type of the disease.
Underneath the retina, fluid, blood, and lipid exudates build up as a result of the fragility and leakiness of the nascent capillaries. If treatment is not received, this may lead to a severe and rapid loss of eyesight.
Important Features of
Important Features of
Outlook Variable:
The degree of neovascularization and the promptness of therapy determine the prognosis for individuals with typical CNV. In many situations, anti-VEGF medication used early on can stabilize or even enhance eyesight.
In summary
When it comes to conditions like wet AMD, classic CNV is a crucial stage when vision preservation requires quick action. The therapy of this problem has greatly improved with the introduction of anti-VEGF medicines and advances in imaging tools, providing afflicted individuals with hope for improved visual results. In the following situations, indocyanine green angiography is highly beneficial Poorly defined or ambiguous CNV; • CNV linked to fluid above the exudate or hemorrhage Differentiating between the vascularized and serous sections of fibrovascular PED Indocyanine green angiography is very useful in following circumstances: Distinguishing between vascularized and serous of a fibrovascular PED; CNV associated with exudate or hemorrhage fluid above [14] .
Figures and tables from the paper
References
12 in the original paper- Mullins RF, Russell SR, Anderson DH, et al. Drusen associated with aging and age-related macular degeneration contain proteins common to extracellular deposits associated with atherosclerosis, elastosis, amyloidosis, and dense-deposit disease. FASEB Journal. 2000;14:835-846.
- Johnson LV, Leitner WP, Staples MK, et al. Complement activation and inflammatory processes in drusen formation and age-related macular degeneration. Experimental Eye Research. 2001;73:887-896.
- Green WR, McDonnell PJ, Yeo JH. Pathologic features of senile macular degeneration. Ophthalmology. 1985;92:612-627.
- Pauleikhoff D, Harper CA, Marshall J, et al. Aging changes in Bruch's membrane: A histochemical and morphologic study. Ophthalmology. 1990;97:171-178.
- Martin D, Maguire M, Fine S, et al. Ranibizumab and bevacizumab for neovascular age-related macular degeneration (AMD). New England Journal of Medicine. 2011;364:1897-1908.
- Klein R, Klein BE, Knudtson MD, et al. Fifteen-year cumulative incidence of age-related macular degeneration: The Beaver Dam Eye Study. Ophthalmology. 2007;114:253-262.
- Cohen SY, Dubois L, Tadayoni R, et al. Prevalence of reticular pseudodrusen in age-related macular degeneration with newly diagnosed choroidal neovascularization. British Journal of Ophthalmology. 2007;91:354-359.
- Schmitz-Valckenberg S, Steinberg JS, Fleckenstein M, et al. Combined confocal scanning laser ophthalmoscopy and spectral-domain optical coherence tomography imaging of reticular drusen associated with age-related macular degeneration. Ophthalmology. 2010;117:1169-1176.
- Zayit-Soudry S, Moroz I, Loewenstein A. Retinal pigment epithelial detachment. Survey of Ophthalmology. 2007;52:227-243.
- Gregori G, Wang F, Rosenfeld PJ, et al. Spectraldomain optical coherence tomography imaging of drusen in nonexudative age-related macular degeneration. Ophthalmology. 2011;118:1373-1379.
- Garcia Filho CA, Rosenfeld PJ, Yehoshua Z, et al. Spectral-domain optical coherence tomography imaging of age-related macular degeneration. US Ophthalmic Review. 2011;5:98-103.
- Holz FG, Bellman C, Staudt S, et al. Fundus autofluorescence and development of geographic atrophy in age-related macular degeneration. Investigative Ophthalmology & Visual Science. 2001;42:1051-1056.