
Research article · 2024 · Full text
International Journal of Veterinary Sciences and Animal HusbandryIsoflurane sparing effect of a multimodal analgesic protocol for ovariohysterectomy in dogs
Volume 9(2) · Pages 40–44 · DOI: 10.22271/veterinary.2024.v9.i2a.1178 ↗
Research areasVeterinary Pharmacology and AnesthesiaAnesthesia and Pain ManagementPediatric Pain Management Techniques
Abstract
Author-writtenThe study was conducted to evaluate the isoflurane sparing effect of a multimodal analgesic protocol in dogs. Twelve animals presented for ovariohysterectomy were selected and divided into group I and II. Group I received gabapentin (2 mg/kg orally), meloxicam (0.1 mg/kg subcutaneously), butorphanol (0.2 mg/kg) and dexmedetomidine (3.5 µg/kg intramuscular), diazepam (0.2 mg/kg), propofol to effect, ketamine (0.7 mg/kg), and lignocaine (2 mg/kg) intravenously, followed by a constant rate infusion of ketamine (10 µg/kg) and lignocaine (30 µg/kg) along with isoflurane maintenance. In Group II, tramadol 2 mg/ kg and dexmedetomidine 3.5 µg/kg intramuscular, followed by diazepam 0.2 mg/kg and propofol to effect intravenously were given. Anaesthesia was maintained with isoflurane in both the groups. The multimodal analgesic protocol provided better quality of sedation and induction, reduced the requirement of propofol for induction and isoflurane for maintenance of anaesthesia and also reduced postoperative pain when compared to a balanced anaesthesia protocol without abnormal deviations from normal.
Summary
Source-checkedPlain-language reading of the full paper, prepared with AI and checked against the text. Each point links to the authors' own words.
Why it matters
- Multimodal analgesia uses two or more drugs with different mechanisms of action to create additive or synergistic pain relief. View evidence ↗
- Failure to control nociception (the transmission of noxious stimuli) can lead to unstable hemodynamics during surgery and pain syndromes after the procedure. View evidence ↗
- Using a multimodal approach can improve cardiopulmonary function by reducing the need for inhalant anesthetics and dampening the body's autonomic response to surgery. View evidence ↗
The question
- The study aimed to compare a multimodal analgesic protocol against a balanced anesthesia protocol to see if it reduced the amount of inhalational anesthetic needed and better controlled postoperative pain in dogs undergoing ovariohysterectomy. View evidence ↗
What they did
- Group I received a multimodal protocol featuring five classes of analgesic drugs, while Group II received a routine balanced protocol with only two analgesic drugs. View evidence ↗
- Group I's premedication included gabapentin (2 mg/kg), meloxicam (0.1 mg/kg), butorphanol (0.2 mg/kg), and dexmedetomidine (3.5 µg/kg); Group II received tramadol (2 mg/kg) and dexmedetomidine (3.5 µg/kg). View evidence ↗
- Group I received a constant rate infusion (CRI) of ketamine (10 µg/kg/min) and lignocaine (30 µg/kg/min) during the procedure. View evidence ↗
- The researchers used an unpaired t-test to analyze the collected data. View evidence ↗
What they found
- The multimodal protocol (Group I) significantly reduced the propofol dose required for induction to 1.0 mg/kg, compared to 2.5±0.22 mg/kg in Group II. View evidence ↗
- The amount of isoflurane liquid needed for maintenance was significantly lower in Group I (2.55±0.33 mL) than in Group II (5.06±0.78 mL), demonstrating an isoflurane-sparing effect. View evidence ↗
- One hour after surgery, dogs in Group I had significantly lower postoperative pain scores than those in Group II. View evidence ↗
- Three dogs in the balanced anesthesia group (Group II) exhibited postoperative hyperesthesia and allodynia, indicating peripheral and central pain sensitization. View evidence ↗
- One dog in each group experienced a second-degree heart block during anesthesia monitoring. View evidence ↗
What it means
- The authors conclude that a multimodal protocol reduces isoflurane requirements, which may lower costs and minimize side effects from high-dose inhalant anesthetics. View evidence ↗
- The authors state that the multimodal protocol effectively controls pain sensitization and reduces postoperative pain without causing adverse systemic effects. View evidence ↗
Visual summary
1 visualsIllustrations explain the paper; they do not show study data.

Multimodal vs Balanced Analgesia Concept
AI-generated conceptual illustration (domestic dogs). It explains the idea and does not show study data.
View source evidence ↗Figures & tables
From the original paper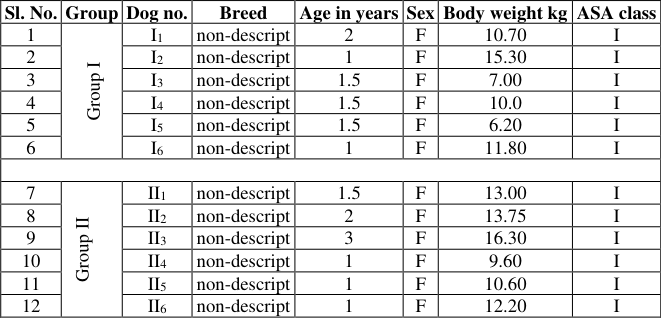 Table 1
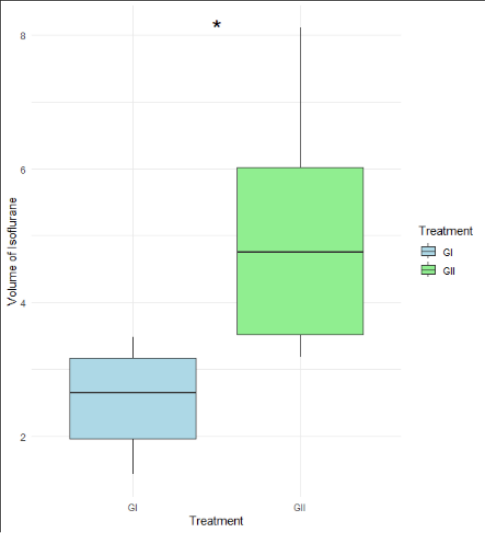 Figure 1
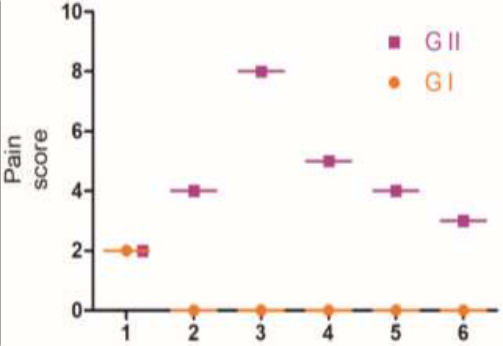 Figure 2
Introduction
Multimodal analgesia is achieved through the additive or synergistic effect of two or more analgesics which have different mechanisms of action. When given preemptively it reduces peripheral and central sensitisation and tachyphylaxis (Gaynor and Muir 2015) [9] . It disrupts more than one part of the nociceptive pathway (Brown et al., 2018) [3] which is the process through which the noxious stimuli are transmitted through the nervous system and the perception of noxious stimuli by the somatosensory cortex leads to experience of pain by the individual. Nociception happens even if the patient is under anaesthesia and the nociceptive processes induced by surgery during handling of viscera or dissection of tissues is the main reason that demands general anaesthesia. If nociception is not controlled, it results in haemodynamic disturbances intraoperatively and pain syndromes postoperatively (Brown et al., 2018) [3] . Multimodal analgesia reduces the requirement of inhalant anaesthetics and autonomic response to surgical stimuli, thereby improves the cardiopulmonary function. It also brings about early and smooth recovery from anaesthesia. It aims at limiting the post operative pain to a tolerable level by preventing peripheral as well as central sensitisation (Lemke and Creighton, 2010) [11] . Hence a study was under taken to evaluate the effects of a multimodal analgesic protocol on requirement of inhalational anaesthetic used for maintenance of anaesthesia and control of post operative pain, in comparison with a balanced anaesthesia protocol for ovariohysterectomy in dogs.
Materials and Methods
The study was conducted in 12 dogs presented for ovariohysterectomy to University Veterinary Hospitals of Kerala Veterinary and Animal Sciences University. All the dogs under study were subjected to thorough pre-anaesthetic evaluation before surgery. A complete clinical examination, followed by evaluation of haematological and serum biochemical parameters, were carried out for all the dogs under study.
Based on the pre-anaesthetic evaluation, the anaesthetic risk was assessed and animals were assigned suitable status of physical health as per American Society of Anesthesiologists' (ASA) standards. Those dogs falling under class I or II were included in the study. The selected dogs were divided randomly into two groups, Group I and II. The dogs in Group I received a multimodal analgesic protocol with five different classes of analgesic drugs as adjunct to balanced anaesthesia. Group II received a routine balanced anaesthesia protocol with only two drugs with analgesic properties in the protocol. Food was withheld for 12 hours and access to water was provided until four hours prior to pre-anaesthetic medication. All the dogs included in group I were given gabapentin at the dose rate of 2.0 mg/kg body weight orally and injection meloxicam 0.1 mg per kg body weight subcutaneously two hours and one hour prior to induction of anaesthesia respectively. Injection butorphanol 0.2 mg per kg body weight and injection dexmedetomidine 3.5 µg per kg body weight were given intramuscularly 20 minutes prior to induction of anaesthesia. Anaesthesia was induced with injection diazepam at the dose rate of 0.2 mg per kg body weight and injection propofol administered 'to effect' intravenously. This was followed by injection ketamine at the dose rate of 0.7 mg per kg and injection lignocaine at the dose rate of 2.0 mg per kg body weight administered intravenously for analgesia. All the dogs under Group II were given injection tramadol at the dose rate of 2.0 mg per kg body weight and injection dexmedetomidine at the dose rate of 3.5 µg per kg body weight, administered intramuscularly. After twenty minutes, anaesthesia was induced with injection diazepam at the dose rate of 0.2 mg per kg and propofol administered 'to effect' intravenously. Soon after induction, all the animals were intubated with appropriately sized endotracheal tubes to maintain airway patency and preoxygenated for two minutes. Inhalation anaesthesia with isoflurane was initiated after ensuring normal vital parameters in all the dogs. For those dogs belonging to Group I, it was followed by ketamine-lignocaine constant rate infusion (CRI) with injection ketamine at the dose rate of 10 μg per kg per minute and lignocaine at the dose rate of 30 μg per kg per minute. These were added to a volume of 5 ml per kg normal saline administered at a fluid rate of 5 ml per kg per hour using the CRI pump which was continued until the completion of surgical procedure. In Group II, normal saline was provided intravenously at the rate of 5 ml per kg per hour until the completion of surgical procedure. In both the groups, the time and quality of sedation and induction and dose of propofol needed for induction were recorded. The vital parameters, reflexes, peripheral saturation of oxygen (SpO 2 ), end tidal carbon dioxide (EtCO 2 ) and perfusion index were monitored during maintenance of anaesthesia. Flow rate of oxygen and the duration of anaesthesia for each vapouriser setting were also recorded to facilitate calculation of the volume of isoflurane vapour and subsequently volume of isoflurane liquid utilised. Blood pressure, ECG and rectal temperature were also monitored for all the dogs until the end of the procedure. The data were analysed using unpaired t test.
Consumption of isoflurane
The volume of isoflurane liquid required to maintain anaesthesia in each case were calculated according to the formula used by Kumar et al. (2013) [10] . As the body weight of the dogs under study ranged from 6 to 20 kg and the duration of anaesthesia from 25 to 80 minutes, it was standardized to 15 kg for 40 minutes. The duration of anaesthesia for each vapouriser setting and fresh gas flow rate were recorded and the total isoflurane vapour utilized was calculated using the formula (1) Vapouriser setting x fresh gas flow in litres per minute (LPM) x time (duration for each vapouriser setting) x 10 Summing up of the isoflurane vapour utilised during each vapouriser setting provided the total isoflurane vapour utilised for that particular procedure. It was then equated to 15 kg body weight and 40 minutes duration of anaesthesia for a uniform assessment using the formula
Results
All the dogs under study were of non-descript breed aged between one and four years and body weight ranging from 6 to 20 kg (Table . 1). After the initial clinical and laboratory examinations, all the dogs were given the ASA status I. Following premedication, there was no significant difference in the time taken for sedation to set in and it was 6.17±0.83 in Group I and 6.67±0.84 in Group II. The dogs in Group I showed better quality of sedation than group II with a median score of 1.5 in Group I and score one in Group II. Time taken for induction was lower and the quality of induction was better in group I dogs as more number of dogs showed good to excellent quality of induction even though significant differences were not there between groups. Induction time was 2.17±0.17 and 3.00±0.45 for Group I and II respectively with no significant difference. However, the dose of propofol required for induction in Group I dogs, was significantly lower than that needed for Group II, 1.0 mg per kg and 2.5±0.22 mg per kg respectively. Degree of muscle relaxation was excellent, jaw tone relaxed and permitted endotracheal intubation in all the dogs after induction. No undesirable effects were observed in any of the dogs of both the groups during induction. The rate of respiration was within the normal limits during general anaesthesia and did not differ significantly between groups although the rates were higher in group II dogs. It was 23±5.25 and 29.17±9.51 in Group I and Group II respectively. The heart rate also followed similar pattern, within the normal physiological limits and there were no statistically significant differences. It was 81±10.41 and 110.5±9.13 in Group I and II respectively. There was no significant difference between groups though the values shown by dogs in Group II were higher. The colour of visible mucous membrane was pale roseate and capillary refill time remained less than two seconds for all the dogs throughout the period of study.
Temperature showed no significant difference between the groups and it was 37.83±0.16 and 37.42±0.33 respectively for Group I and II during the anaesthetic procedure. The peripheral saturation of oxygen remained stable and within the normal limits throughout the anaesthetic procedure and it was 98±0.93 and 98±0.77 for Group I and II without any significant difference between groups. Perfusion index values were within the normal range and though Group I dogs showed higher values at all periods of observation, there was no significant difference between the two groups. It was 1.00±0.40 and 0.53±0.09 for Group I and II respectively. EtCO2 values were lower than normal during anaesthesia in Group II. It was 35.17±2.21 and 33.67±2.33 in Group I and II respectively. There was no significant difference between the two groups. Nociception as indicated by sudden increase in heart rate and respiratory rate associated with pulling of suspensory ligament was observed in four dogs of group II and one dog in Group I. Three dogs of Group II showed signs of peripheral and central sensitization of pain in the form of hyperesthesia and allodynia, during the postoperative period.
Haematological and serum biochemical parameters remained within the normal physiological limits in both the groups throughout the period of study. Total duration of anaesthesia was 49.17±7.63 and 37.5±3.88 in group I and II respectively. The volume of isoflurane liquid used to maintain anaesthesia was 2.55±0.33 and 5.06±0.78 respectively in Group I and II (figure 1). It was significantly lower in group I when compared to group II p < 0.05 The mean value of mean arterial blood pressure (MAP) exhibited by the dogs under study during anaesthesia was 84.17±5.29 and 95.50±13.04 in Group I and II respectively. There was no significant difference and the values were within the normal range.
The post operative pain score assessed after one hour, using a modified Glasgow Composite measure Pain Scale-short form was significantly lower for Group I dogs when compared to Group II (figure 2)
Discussion
The study was aimed at evaluating the effectiveness of a multimodal analgesic protocol in controlling the nociception and postoperative pain, at the same time reducing the requirement of drugs used for induction and maintenance of anaesthesia. Multimodal analgesia includes different classes of drugs which act at various levels of the pain pathway, blocking the transmission of nociceptive signals. The preanaesthetic evaluation consisting of clinical examination, laboratory evaluation including haemato-biochemical evaluation, revealed the health status, and ASA class of the patient. The dogs included in the present study were under class I were selected for study as those included in class ≥III were associated with increased risk of anaesthesia related death (Bille et al., 2012) [2] . The preanaesthetic preparation included withdrawal of food for twelve hours and water for four hours prior to anaesthesia. Most of the researchers performing anaesthesia related research in dogs prefer withdrawal of food but not water (Lozano et al., 2009) [12] or withdrawal of water for a limited period of two hours (Farokhzad et al., 2021) [7] . Gatson et al.
(2016) [8] in their study had given access to water until premedication. They also opined that subclinical dehydration due to water deprival when combined with the hypotensive effect of anaesthetics may result in clinically evident hypotension.
The multimodal analgesia protocol with multiple classes of analgesics including an opioid, a non-steroidal antiinflammatory drug, alpha 2 agonist, NMDA antagonist, intravenous preparation of lignocaine and a gabapentinoid (α2δ ligand) along with induction and maintenance drugs was proved to be better in multiple ways than the balanced anaesthesia protocol which included only a single analgesic drug along with premedication, induction and maintenance agents. It provided better quality of sedation, induction, reduced the dose of propofol required for induction of anaesthesia and isoflurane liquid utilised for maintenance of anaesthesia. Multimodal analgesia reduced autonomic response to the surgical stimuli, thereby improved the cardiopulmonary function. It also brought about early and smooth recovery from anaesthesia (Lemke and Creighton, 2010) [11] . Studies have proved that postoperative pain is a combination of nociceptive, inflammatory, neurogenic and visceral components so must be managed through multimodal analgesic techniques (Crociolli et al., 2015) [6] . Hence a combination of drugs that manage neuropathic, somatic and visceral pain, have anti-inflammatory action which act at different levels of the pain pathway were used in this study.
Induction of anaesthesia was assessed by muscle relaxation indicated by absence of jaw tone, absence of palpebral reflex and ease of endotracheal intubation (Ahmad et al., 2013) [1] . Muscle relaxation and ease of endotracheal intubation was excellent in all the animals once they were induced except two dogs in group II. Preoxygenation for 2-3 minutes was recommended prior to induction which provided more time before haemoglobin desaturated in the face of an emergency (Niggemann et al., 2019) [13] . In the present study preoxygenation was provided after induction, before starting maintenance of anaesthesia with isoflurane which was found to be adequate in maintaining the peripheral saturation of oxygen within normal limits. The MAP values were within the normal range in both the groups and hypotension was not evident. Bustamante et al. (2018) [4] in their study found that isoflurane maintenance resulted in reduced MAP values when compared to propofol maintenance and managed hypotension (MAP< 60 mm Hg) by decreasing the concentration of isoflurane or rate of propofol infusion and administered atropine if concurrent bradycardia was also evident. Cattai et al. (2018) [5] had observed a fall in BP during induction of anaesthesia with propofol and it was attributed to decrease in sympathetic response and systemic vascular resistance caused by propofol. In the present study, even though multiple drugs were used, hypotension was not evident. All the parameters for anaesthetic monitoring including the rate of respiration, heart rate, CRT, colour of visible mucous membrane, SpO2, ETCO2, perfusion index and rectal temperature, all were within the normal range and did not show any significant difference between groups. The undesirable changes observed during monitoring of anaesthesia were 2° heart block in one dog each of Group I and II. Uilenreef et al. (2008) [15] also monitored a lead II ECG and reported sinus arrhythmia in all the dogs, and second-degree heart block with higher doses of dexmedetomidine CRI. Slingsby et al. (2011) [14] also reported second degree AV block which got corrected without any intervention.
Conclusion
Multimodal anesthesia protocol can indeed reduce the requirement of isoflurane, which could potentially lead to cost savings and minimize the side effects associated with higher doses of inhalation anesthetics. A lower dose of propofol for induction is generally desirable as it would decrease the risk of adverse events associated with propofol administration, such as hypotension or respiratory depression. Multimodal anesthesia protocol can effectively control both peripheral and central sensitization of pain, it could indeed lead to reduced postoperative pain without causing any adverse systemic effects. This is beneficial for patient recovery and satisfaction and has the potential to improve various aspects of anesthesia and postoperative care.
Acknowledgement
The authors are thankful to the Kerala Veterinary and Animal Sciences University Veterinary Hospitals at Mannuthy and Kokkala and College of Veterinary and Animal Sciences Mannuthy for the facilities provided.
Figures and tables from the paper
| Sl. No. | Group | Dog no. | Breed | Age in years | Sex | Body weight kg | ASA class |
|---|---|---|---|---|---|---|---|
| 1 | Group I | I1 | non-descript | 2 | F | 10.70 | I |
| 2 | I2 | non-descript | 1 | F | 15.30 | I | |
| 3 | I3 | non-descript | 1.5 | F | 7.00 | I | |
| 4 | I4 | non-descript | 1.5 | F | 10.0 | I | |
| 5 | I5 | non-descript | 1.5 | F | 6.20 | I | |
| 6 | I6 | non-descript | 1 | F | 11.80 | I | |
| 7 | Group II | II1 | non-descript | 1.5 | F | 13.00 | I |
| 8 | II2 | non-descript | 2 | F | 13.75 | I | |
| 9 | II3 | non-descript | 3 | F | 16.30 | I | |
| 10 | II4 | non-descript | 1 | F | 9.60 | I | |
| 11 | II5 | non-descript | 1 | F | 10.60 | I | |
| 12 | II6 | non-descript | 1 | F | 12.20 | I |
Table text extracted from the original PDF; superscript letters are shown inline. The original table image is below.
View original table image
References
15 in the original paper- Ahmad RA, Kinjavdekar P, Aithal HP, Pawde AM, Kumar D. Potential use of dexmedetomidine for different levels of sedation, analgesia and anaesthesia in dogs. Veterinarni Medicina. 2013;58(2):87-95.
- Bille C, Auvigne V, Libermann S, Bomassi E, Durieux P, Rattez E. Risk of anaesthetic mortality in dogs and cats: an observational cohort study of 3546 cases. Veterinary anaesthesia and analgesia. 2012;39(1):59-68.
- Brown EN, Pavone KJ, Naranjo M. Multimodal general anesthesia: theory and practice. Anesthesia and analgesia. 2018;127(5):1246-1258.
- Bustamante R, Aguado D, Cediel R, de Segura IG, Canfrán S. Clinical comparison of the effects of isoflurane or propofol anaesthesia on mean arterial blood pressure and ventilation in dogs undergoing orthopaedic surgery receiving epidural anaesthesia. The Veterinary Journal. 2018;233:49-54.
- Cattai A, Rabozzi R, Ferasin H, Isola M, Franci P. Haemodynamic changes during propofol induction in dogs: new findings and approach of monitoring. BMC veterinary research. 2018;14(1):1-8.
- Crociolli GC, Cassu RN, Barbero RC, Rocha TL, Gomes DR, Nicacio GM. Gabapentin as an adjuvant for postoperative pain management in dogs undergoing mastectomy. Journal of Veterinary Medical Science. 2015;77(8):1011-1015.
- Farokhzad B, Sabiza S, Razi Jalali M, Baniadam A. Intraperitoneal administration of lidocaine or tramadol alone or in combination on postoperative pain after ovariohysterectomy in dogs. Veterinary Medicine and Science. 2021;7(3):634-641.
- Gatson BJ, Garcia-Pereira FL, James M, Carrera-Justiz S, Lewis DD. Use of a perfusion index to confirm the presence of sciatic nerve blockade in dogs. Veterinary Anaesthesia and analgesia. 2016;43(6):662-669.
- Gaynor JS, Muir III WW. Alternative drugs and novel therapies used to treat pain. In Handbook of Veterinary Pain Management. Edn3, Mosby, Missouri, 2015, 280301.
- Kumar SS, Rajendran N, Dharmaceelan S, Kathirvel S, Subramanian M, Selvaraj P. Effect of Butorphanol and Buprenorphine on inhalant sparing and gas concentrations during low flow Isoflurane anaesthesia in cattle. Advances in Animal and Veterinary Sciences 2013;1(2):29-32.
- Lemke KA, Creighton CM. Analgesia for anesthetized patients. Topics in Companion Animal Medicine. 2010;25(2):70-82.
- Lozano AJ, Brodbelt DC, Borer KE, Armitage-Chan E, Clarke KW, Alibhai HI. A comparison of the duration and quality of recovery from isoflurane, sevoflurane and desflurane anaesthesia in dogs undergoing magnetic resonance imaging. Veterinary anaesthesia and analgesia. 2009;36(3):220-229.
- Niggemann JR, Tichy A, Eberspächer-Schweda MC, Eberspächer-Schweda E. Preoperative calming effect of melatonin and its influence on propofol dose for anesthesia induction in healthy dogs. Veterinary anaesthesia and analgesia. 2019;46(5):560-567.
- Slingsby LS, Taylor PM, Murrell JC. A study to evaluate buprenorphine at 40 μg kg-1 compared to 20 μg kg-1 as a post-operative analgesic in the dog. Veterinary anaesthesia and analgesia. 2011;38(6):584-593.
- Uilenreef JJ, Murrell JC, McKusick BC, Hellebrekers LJ. Dexmedetomidine continuous rate infusion during isoflurane anaesthesia in canine surgical patients. Veterinary anaesthesia and analgesia. 2008;35(1):1-12.