
Research article · 2024 · Full text
International Journal of Advanced Biochemistry ResearchD-Dimer a biomarker for disease severity in COVID-19 patients
Volume 8(3) · Pages 17–21 · DOI: 10.33545/26174693.2024.v8.i3a.669 ↗
Research areasCardiovascular Disease and AdiposityAdipokines, Inflammation, and Metabolic DiseasesDermatological and COVID-19 studies
Abstract
Author-writtenIntroduction: The Covid-19 disease has devastating effect in the world since its emergence in Wuhan of the Hubei province in China in December 2019. The world struggled for an early and effective biomarker to predict severity and to improve the management of the disease. Aim: To estimate the level of D-dimer which could predict disease severity in Covid-19 related disease. Materials and Methods: This is a Cross sectional study done with D-dimer to predict disease severity in Covid-19 in the department of Biochemistry, Jawaharlal Nehru Institute of Medical Sciences, Imphal, Manipur. The study period is from June 2021 to August 2021. It involved analysis of 144 hospitalised patients of different grades of Covid-19 pneumonia with different ranges of severity. The study population included symptomatic patients of both sexes which are above 18 years with a laboratory confirmed Covid-19 by RTPCR from either throat or nasal swab. All the samples for D-dimer were collected 2-3 days from the period of confirmation. The study population are further divided into three cohorts viz. mild, moderate and severe Covid-19 groups based on the clinical parameters as per ICMR (Indian Council of Medical Research) guide line published at the time. Results: The study produces results which showed significant differences in the ranges of D-dimer values across the different clinical severities of Covid-19 pneumonia (p
Summary
Source-checkedPlain-language reading of the full paper, prepared with AI and checked against the text. Each point links to the authors' own words.
Why it matters
- There has been a global need for effective biomarkers that can predict the severity of COVID-19 to improve patient management. View evidence ↗
- Critically ill COVID-19 patients often experience coagulopathy, as the virus may predispose them to thrombotic diseases in both arterial and venous circulation. View evidence ↗
- D-dimer, a product of fibrin lysis, is used as a marker where elevated levels correlate with poor prognosis in patients with acute respiratory distress syndrome (ARDS). View evidence ↗
The question
- The study aimed to measure D-dimer levels in hospitalized COVID-19 patients to determine if there is a correlation between these levels and the severity of the disease. View evidence ↗
What they did
- This cross-sectional study was conducted from June to August 2021 at the Jawaharlal Nehru Institute of Medical Sciences, involving 144 RT-PCR confirmed COVID-19 patients over 18 years old. View evidence ↗
- D-dimer samples were collected 2-3 days after RT-PCR confirmation, and patients were categorized as mild, moderate, or severe based on ICMR guidelines. View evidence ↗
- The study used a D-dimer cut-off value of < 0.5 mg/L to define the normal range. View evidence ↗
- Statistical analysis was performed using SPSS v21, employing T-tests, Mann-Whitney U tests, Chi-square tests, and Kendall’s coefficient analysis for correlations. View evidence ↗
What they found
- The study found no significant difference in D-dimer results based on comorbidities such as diabetes mellitus, hypertension, or renal insufficiency. View evidence ↗
- D-dimer values at admission showed a significant increase as the severity of COVID-19 increased (Kendall’s tau-b = 0.46, p<0.001). View evidence ↗
What it means
- The authors conclude that D-dimer is a useful prognostic biomarker that can help improve the clinical management of COVID-19. View evidence ↗
- A limitation of the study is the lack of confirmatory assessments for deep vein thrombosis, pulmonary embolism, or other thromboembolic events. View evidence ↗
- The study did not evaluate the influence of multiorgan dysfunction on D-dimer levels, nor did it monitor D-dimer trends in patients recovering from severe pneumonia. View evidence ↗
Visual summary
2 visualsIllustrations explain the paper; charts are replotted from the paper's own table values.
Correlation of D-dimer and Disease Severity
AI-generated conceptual illustration (human lungs and blood vessels). It explains the idea and does not show study data.
View source evidence ↗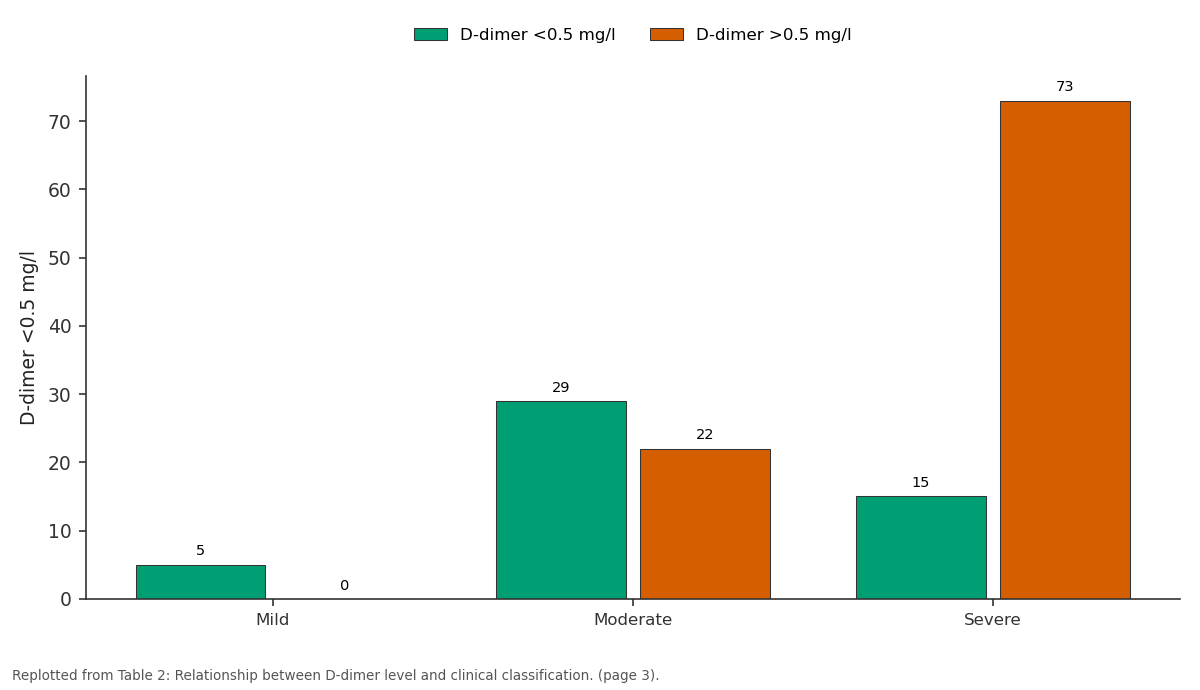
D-dimer <0.5 mg/l and D-dimer >0.5 mg/l: Mild vs Moderate vs Severe
Replotted from Table 2 (page 3) of the original paper. Every bar is the paper's own table value.
View source evidence ↗Figures & tables
From the original paper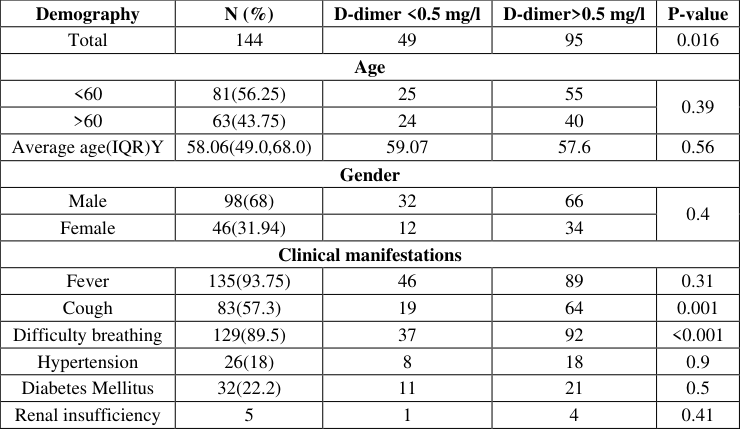 Table 1
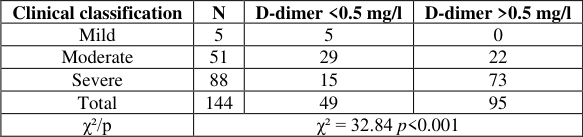 Table 2
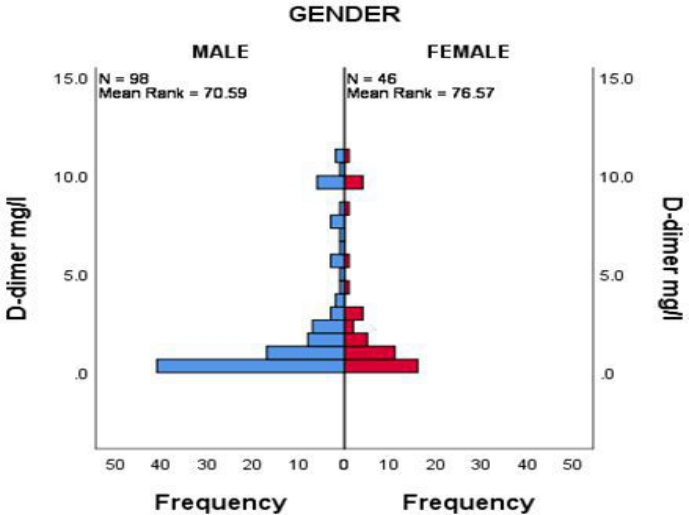 Figure 1
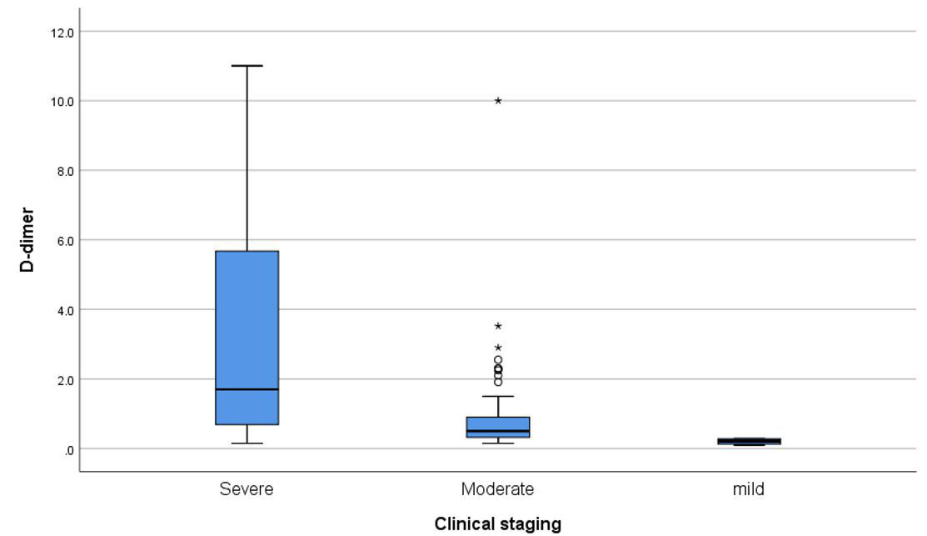 Figure 2
Introduction
The severe acute respiratory syndrome coronavirus 2 (SARS-CoV-2) has spread rapidly worldwide affecting all ranges of population since the emergence of COVID-19 in December, 2019, in Wuhan, China. This infection can present as asymptomatic carriers or produce common symptoms in the infected individuals such as fever, dry cough, dyspnoea, and fatigue of varying severity. In its most severe manifestation, individuals with COVID-19 can cause Acute Respiratory Distress Syndrome (ARDS) ultimately leading to death if the disease progresses [1] . With wide spectrum of symptoms and among those requiring hospitalization for respiratory support about 20-26% of patients become severe or critically ill with mortality rates varying from 26 to 61.5% [2] . Coagulopathy is more prevalent in critically ill patients of COVID-19. Several studies have shown that SARS-CoV-2 may predispose the infected patients to thrombotic disease of the venous and arterial circulation. This may be due to the pathology of excessive inflammation, platelet activation, endothelial dysfunction, and stasis of the circulation [3] . D-dimer is a product of lysis of cross-linked fibrin after the process of coagulation and fibrinolysis [4] . Elevated D-dimer values correlate with a poor prognosis in patients of acute respiratory distress syndrome (ARDS). Hence there is increased rate of admission to intensive care unit with simultaneous increase in mortality [5,6] .
COVID-19 and Thromboembolism
During the course of management of patients of COVID-19 of varying ranges of clinical severity, several clinicians observe that the prothrombotic state and venous thromboembolic disease events may play a role in COVID-19 symptomology [7][8][9][10][11] . This impression is on the foundation of plenty of reports of large vessel stroke among young patients, recurrent clotting of haemodialysis catheter, reports of occult pulmonary embolism and pulmonary microangiopathy in autopsy of such patients. Also, the pulmonary physiology of these mechanically ventilated COVID-19 patients were also found to be similar to pulmonary vascular disease of such patients mentioned above [12][13][14][15] .
AIMS
The present study was conducted to estimate the level of Ddimer in COVID 19 positive patients admitted in the hospital and find out the correlation, if any, between the level of D-dimer and the disease severity.
Materials and Method
This is a Cross sectional study done in the department of Biochemistry, Jawaharlal Nehru Institute of Medical Sciences, Imphal, Manipur June 2021 to August. 144 hospitalised patients of varying severity of isolated COVID-19 pulmonary disease who are above 18years (of both sexes) with a RT-PCR confirmed COVID-19 were included in the study. Patients who do not give consent was the exclusion criteria. Ethical clearance was obtained from the Institutional Ethics committee JNIMS, prior to the study. Informed consent was taken from the patients. All the samples for D-Dimer was collected 2-3 days after RTPCR confirmation of symptomatic patients and clinically categorized into mild, moderate and severe COVID-19 pneumonia as per ICMR guideline. Patient characteristics, comorbidities, on admission and disease severity, were obtained from patients' medical records and reaffirmed with patients clinical assessment.
Statistical analysis
Data were analysed using SPSS software v21. Both continuous and categorical data were expressed as mean and percentage. Test of significance for quantitative data was performed using T tests or Man-Whitney U test. Categorical variables were compared by Chi-square tests or fisher's exact test. Correlation of D-dimer with clinical staging was evaluated by Kendall's coefficient analysis. The Probability value (P-value) of less than 0.05 was taken as significant.
Result
Of the 144 patients in the study, the median age was 58 years (IQR, 49-68), ranging from 24 years to 87years. A total of 43.75% (63/144) patients were more than 60 years and the remaining 56.25% (81/144) patients were less than 60 years of age. The cut-off value for D-dimer was set at the usual normal range of < 0.5 mg/L. The basic demographic characteristics of the patients such as age, gender and comorbidities are listed in table 1. Generally, the distribution of D-dimer across all ages and gender is the same. As per the cut-off value, 66% (95/144) patients' D-dimer levels were more than 0.5 mg/l, and 34% (49/144) had D-dimer level < 0.5 mg/l (p-0.016). Like any other pneumonia, fever, cough and difficulty in breathing are the usual clinical manifestations of COVID-19 pneumonia. Patients with abnormal D-dimer levels were more likely to have a severe cough and breathing difficulty (p-0.001). No significant difference in the results are noted among the patients with respect to underlying co-morbid condition such as hypertension, diabetes mellitus and renal insufficiency are noted in our present study. There were significant differences in D-dimer test values for the different clinical classification (p<0.001) as shown in Table . 2. D-dimer level were more likely to be abnormal in patients with severe cases than those with mild or moderate symptoms (Fig. 2).
| Demography | N (%) | D-dimer <0.5 mg/l | D-dimer>0.5 mg/l | P-value |
|---|---|---|---|---|
| Total | 144 | 49 | 95 | 0.016 |
| Age | ||||
| <60 | 81(56.25) | 25 | 55 | 0.39 |
| >60 | 63(43.75) | 24 | 40 | |
| Average age(IQR)Y | 58.06(49.0,68.0) | 59.07 | 57.6 | 0.56 |
| Gender | ||||
| Male | 98(68) | 32 | 66 | 0.4 |
| Female | 46(31.94) | 12 | 34 | |
| Clinical manifestations | ||||
| Fever | 135(93.75) | 46 | 89 | 0.31 |
| Cough | 83(57.3) | 19 | 64 | 0.001 |
| Difficulty breathing | 129(89.5) | 37 | 92 | <0.001 |
| Hypertension | 26(18) | 8 | 18 | 0.9 |
| Diabetes Mellitus | 32(22.2) | 11 | 21 | 0.5 |
| Renal insufficiency | 5 | 1 | 4 | 0.41 |
Table text extracted from the original PDF; superscript letters are shown inline. The original table image is below.
View original table image
Discussion
In our study, it is found that elevation of D-dimer level is common among patients of COVID-19 and its elevated values has positive correlation with increased disease severity. D-dimers which is one of the fragments produced when plasmin cleaves fibrin to break down clots is routinely used to exclude thrombosis. Any pathologic or nonpathologic process that increases fibrin production or breakdown thereby increases plasma D-dimer levels [16] . Deep vein thrombosis, pulmonary embolism, arterial thrombosis, disseminated intravascular coagulation and conditions that promotes thrombosis such as pregnancy, inflammation, cancer, chronic liver diseases, post trauma and vasculitis are some the conditions that can cause elevation of D-dimer.
The study lacks the confirmatory assessment for pulmonary embolism or deep vein thrombosis or any other thromboembolism of any part of the body. Nevertheless, elevated D-dimer serves as a diagnostic tool for thromboembolism in the ongoing pathophysiologic milieu of any COVID-19 affected patient. There is also a significant correlation between the elevated D-dimer levels and disease severity stratified by clinical staging according to the interim guideline. High percentage of D-dimer elevation is seen in the present study which may be due to higher percentage of severe cases with the hospital serving as a referral centre.
The study lacks to define the influence of concomitant multisystem and multiorgan dysfunction or injury in the level of D-dimer values. It also lacks the monitoring of increasing or static or perhaps a declining levels of D-dimer in those who recover from severe COVID pneumonia. The effect of several medications and management protocols in D-dimer also merits further evaluation. Hence, further studies are still advocated as to associate the causal mechanisms and the specific effects of SARS-CoV 2 with consequent systemic inflammatory response. It is also worthwhile to note that in SARS-COV-2 infection there is dysregulation of coagulation/anti-coagulation cascades resulting in worsening lung pathology. 17 Ongoing infection promotes the release of pro-inflammatory cytokines such as IL-2, IL-7, G-CSF, IP-10, MCP-1, MIP-1A and TNF-α, thus causing an inflammatory storm [18] . Levels of these were higher especially in the plasma of severe COVID-19 patients and likely so in other illnesses causing SIRS.
Conclusion
D-dimer levels are commonly raised in SARS-CoV-2 infection. Significantly higher levels are seen in patients with severe illness. Therefore D-dimer can be a good prognostic and helpful biomarker to improve the management of COVID-19.
Figures and tables from the paper
| Clinical classification | N | D-dimer <0.5 mg/l | D-dimer >0.5 mg/l |
|---|---|---|---|
| Mild | 5 | 5 | 0 |
| Moderate | 51 | 29 | 22 |
| Severe | 88 | 15 | 73 |
| Total | 144 | 49 | 95 |
| χ²/p | χ² = 32.84 p<0.001 |
Table text extracted from the original PDF; superscript letters are shown inline. The original table image is below.
View original table image
References
22 in the original paper- Huang C, et al. Clinical features of patients infected with 2019 novel coronavirus in Wuhan, China. Lancet 2020;395:497-506.
- Mehrdad Rostami, Hassan Mansouritorghabeh D-dimer level in COVID-19 infection: A systematic review, Expert Review of Hematology. 2020;13(11):12651275. DOI: 10.1080/17474086.2020.1831383
- Piazza G, Campia U, Hurwitz S, et al. Registry of arterial and venous thromboembolic complications in patients with COVID-19. J Am Coll Cardiol. 2020;76(18):2060-20.
- Zhang L, Yan X, Fan Q, Liu H, Liu X, Liu Z, et al. Ddimer levels on admission to predict in-hospital mortality in patients with COVID-19. J Thromb Haemost. 2020;18(6):1324-1329. doi: 10.1111/jth.14859. PMID: 32306492; PMCID: PMC7264730.
- Zhou F, Yu T, Du R, et al. Clinical course and risk factors for mortality of adult inpatients with COVID-19 in Wuhan, China: a retrospective cohort study. Lancet. 2020;395(10229):1054-1062.
- Wu Z, McGoogan JM. Characteristics of and important lessons from the Coronavirus Disease 2019 (COVID19) outbreak in China: summary of a report of 72 314 cases from the Chinese Center for Disease Control and Prevention. JAMA. 2020;323(13):1239-1242.
- Wu Z, McGoogan JM. Characteristics of and important lessons from the coronavirus disease 2019 (COVID-19) outbreak in China: summary of a report of 72314 cases from the Chinese Center for Disease Control and Prevention. JAMA. 2020 (ahead of print) [PubMed] [Google Scholar]
- Tang N. Abnormal coagulation parameters are associated with poor prognosis in patients with novel coronavirus pneumonia. J. Thromb. Haemost. 2020;18(4):844-847. [PMC free article] [PubMed] [Google Scholar].
- Barrett CD. ISTH interim guidance on recognition and management of coagulopathy in COVID-19: a comment. J Thromb. Haemost. 2020 (ahead of print) [PubMed] [Google Scholar]
- Zhang Y. Coagulopathy and antiphospholipid antibodies in patients with COVID-19. N. Engl. J. Med. 2020;382(17):e38. [PMC free article] [PubMed] [Google Scholar]
- Dolhnikoff M. Pathological evidence of pulmonary thrombotic phenomena in severe COVID-19. J. Thromb. Haemost, 2020 (ahead of print) [PMC free article] [PubMed] [Google Scholar
- Cui S. Prevalence of venous thromboembolism in patients with severe novel coronavirus pneumonia. J Thromb. Haemost. 2020. (ahead of print) [PMC free article] [PubMed] [Google Scholar]
- Oxley TJ. Large-vessel stroke as a presenting feature of COVID-19 in the young. N. Engl. J Med. 2020. (ahead of print) [PMC free article] [PubMed] [Google Scholar]
- LM. COVID-19 Autopsies, Oklahoma, USA. Am. J Clin. Pathol. 2020. (ahead of print) [PMC free article] [PubMed] [Google Scholar]
- Liu X. Ventilatory ratio in hypercapnic mechanically ventilated patients with COVID-19 associated ARDS. Am. J Respir. Crit. Care Med. 2020. (ahead of print) [PMC free article] [PubMed] [Google Scholar]
- Linkins LA, Takach Lapner S. Review of D-dimer testing: good, bad, and ugly. Int J Lab Hematol. 2017;39(S1):98-103. doi: 10.1111/ijlh.12665.
- Gralinski LE, Baric RS. Molecular pathology of emerging coronavirus infections. J Pathol. 2015;235(2):185-195. doi: 10.1002/path.4454. [PMC free article] [PubMed] [CrossRef] [Google Scholar]
- Chousterman BG, Swirski FK, Weber GF. Cytokine storm and sepsis disease pathogenesis. Semin. Immunopathol. 2017;39:517-528. https://doi.org/10.1007/s00281-017-0639-8.
- Chen G, et al. Clinical and immunological features of severe and moderate coronavirus disease 2019. J. Clin. Investig. 2020;130:2620-2629. https://doi.org/10.1172/jci137244.
- Mehta P, et al. COVID-19: consider cytokine storm syndromes and immunosuppression. Lancet (London, England), 2020;395:1033-1034. https://doi.org/10.1016/s0140-6736(20)30628-0.
- Wong JP, et al. Current and future developments in the treatment of virus-induced hypercytokinemia. Future Med. Chem. 2017;9:169-178. https://doi.org/10.4155/fmc-2016-0181.
- Li H, et al. Serum Amyloid A is a biomarker of severe coronavirus disease and poor prognosis. J Infect. 2020;80:646-655. https://doi.org/10.1016/j.jinf.2020.03.035.