
Research article · 2023 · Full text
International Journal of Biology SciencesEpidemiology of Enterobacteriaceae uropathogenic strains and resistant to antibiotics in the clinical laboratory of the regional hospital of Beni Mellal, Morocco
Volume 5(2) · Pages 08–13 · DOI: 10.33545/26649926.2023.v5.i2a.164 ↗
Research areasUrinary Tract Infections ManagementAntibiotic Resistance in BacteriaEnterobacteriaceae and Cronobacter Research
Abstract
Author-writtenUrinary tract infections were a reel public health problem. Enterobacteriaceae are the most common bacteria involved in the etiology of this type of infection. This study aimed to describe the Epidemiology of Enterobacteriaceae uropathogenic strains isolated from both hospitalized and outpatient’s cases, and to determine their resistance antibiograms. This retrospective descriptive study was carried out in the Clinical Laboratory of the Regional Hospital of Beni Mellal city, over a period of three years from January 2020 to December 2022. Data collection was done using the laboratory register, and statistical analysis was performed using the SphinxPlus2.V5. The prevalence of urinary tract infections was 15.6%. A total of 325 bacterial strains were isolated from 206 women and 119 men. Among the germs identified, 89.84% were Enterobacteriaceae, 84.93% were community strains and 17.07% were nosocomial strains. Escherichia coli was the most frequent organism, accounting for 71.63% of cases. The result showed that all isolated strains of Enterobacteriaceae had high levels of resistance to commonly used β-lactam antibiotics, including amoxicillin (60.31%), Ticarcillin (56%), ampicillin (51.38%), amoxicillin-clavulanic acid (48%), cefalotin (42.77%), mecillinam (35.69%) and Cefoxitin (32.66%). Additionally, the strains demonstrated resistance to quinolones such as Ofloxacin (40.31%), ciprofloxacin (36.31%), and nalidixic acid (29.35%), as well as sulfamides such as cotrimoxazole (31.69%). However, there was a low rate of resistance to third-generation cephalosporins (ceftazidime (12.61%) and ceftriaxone (9.85%), phenicoles (chloramphenicol (13.85%), carbapenems (imipenem (2.46%), Aminoglycosidees (gentamicin (7.69%) and Polymyxins (Colistin (09.54%). This study showed a high prevalence of urinary tract infections, mainly caused by Enterobacteriaceae with a high frequency of antibiotic resistance. The results of our study could be useful for taking action to reduce the incidence of urinary tract infections and to mitigate the spread of resistant bacteria.
Summary
Source-checkedPlain-language reading of the full paper, prepared with AI and checked against the text. Each point links to the authors' own words.
Why it matters
- Urinary tract infections (UTIs) represent a significant public health challenge. View evidence ↗
- Bacteria from the Enterobacteriaceae family are the most frequent cause of UTIs. View evidence ↗
- The rise of antibiotic resistance is a global concern, with WHO projections suggesting it could become the leading cause of death by 2050. View evidence ↗
The question
- The study aimed to describe the epidemiology of uropathogenic Enterobacteriaceae strains from both inpatients and outpatients and determine their antibiotic resistance profiles. View evidence ↗
What they did
- The research was a retrospective descriptive study conducted at the Regional Hospital of Beni Mellal, Morocco, from January 2020 to December 2022. View evidence ↗
- The study included all positive Cyto Bacteriological Examination of Urine (CBEU) results and corresponding antibiograms recorded in the laboratory register. View evidence ↗
- Data analysis was performed using Sphinx Plus2 software, employing the chi-squared (χ2) test to assess relationships between variables. View evidence ↗
What they found
- The overall prevalence of urinary tract infections among the tested population was 15.6% (325 out of 2083 cases). View evidence ↗
- Out of 325 isolated bacterial strains, 206 were from women and 119 were from men. View evidence ↗
- Enterobacteriaceae accounted for 89.84% of identified germs, with 84.93% being community-acquired and 17.07% being nosocomial. View evidence ↗
- Escherichia coli was the most common organism isolated, representing 71.63% of the cases. View evidence ↗
- Enterobacteriaceae strains showed high resistance to several β-lactam antibiotics, most notably amoxicillin (60.31%), Ticarcillin (56%), and ampicillin (51.38%). View evidence ↗
- Resistance was also observed for quinolones, including Ofloxacin (40.31%) and ciprofloxacin (36.31%), and the sulfamide cotrimoxazole (31.69%). View evidence ↗
- Low resistance rates were found for imipenem (2.46%), gentamicin (7.69%), and colistin (9.54%). View evidence ↗
What it means
- The authors recommend implementing antibiotic susceptibility testing before treatment, ensuring prescription compliance, and increasing public awareness to reduce self-medication. View evidence ↗
- The study was limited by its retrospective design, reliance on laboratory registers, and its focus on a single hospital center, meaning results may not be generalizable to the entire population. View evidence ↗
Figures & tables
From the original paper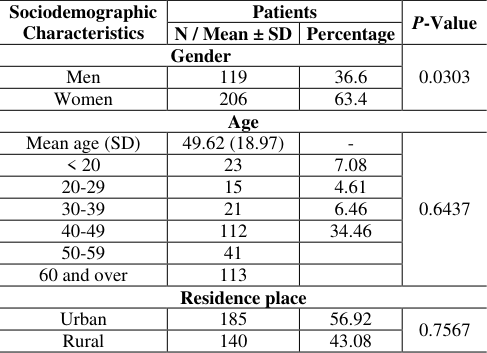 Table 1
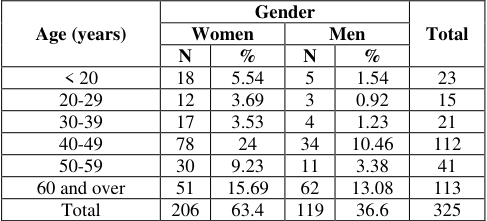 Table 2
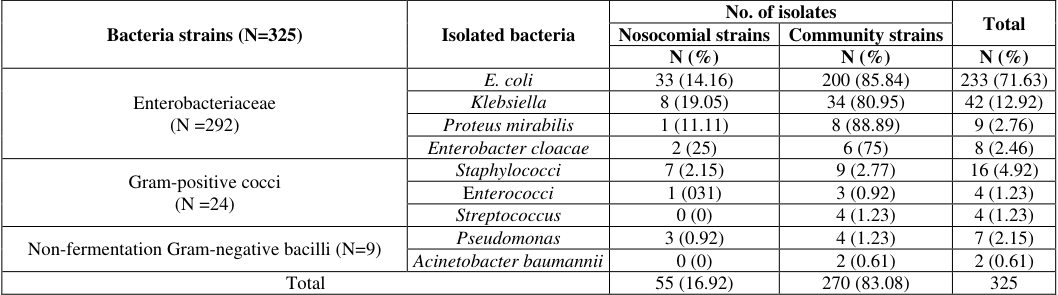 Table 3
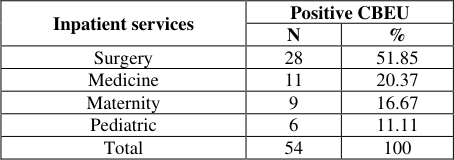 Table 4
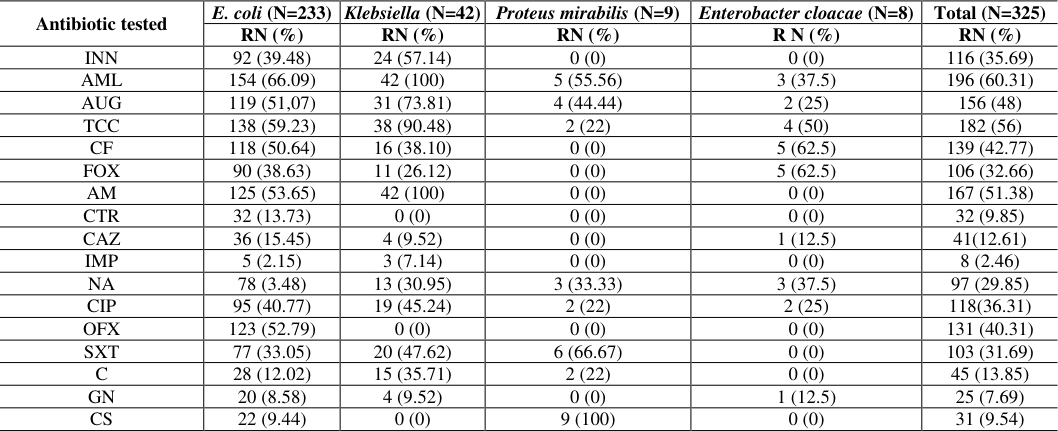 Table 5
Introduction
Urinary tract infections (UTIs) come in second place after infections respiratory problems as reasons for consultation and antibiotic prescription (Chervet et al., 2018) [1] . Around 150 million cases of UTIs worldwide were recorded annually (Bertholom, 2016) [2] . They are a major public health problem. Enterobacteriaceae were generally the most bacteria involved in the etiology of UTIs (Randrianirina et al., 2007; Muvunyi Arsalane et al., 2014; Amady et al., 2021) [3][4][5] . This epidemiological profile were largely dominated by Escherichia coli (E. coli) and Klebsiella (Amady et [5][6][7][8][9][10][11] . Since the end of the years 1990, the epidemiology of UTIs evolved with the emergence within Enterobacteriaceae of a resistance to antibiotics (Cattoir and Bicêtre, 2008; Elhani, 2008) [12,13] . The rate of uropathogen resistance to routinely administered antibiotics (Amoxicillin, trimethoprim, sulfamethoxazole) has also been steadily rising, according to various studies conducted in Europe and the United States (Gupta et al., 1999; Kahlmeter and Menday, 2003) [14,15] . In Africa, strains of Enterobacteriaceae are highly resistant to commonly used -lactams, quinolones and sulfamides were noticed in Burkina Faso (Ouedraogo et al., 2022) [16] . Studies carried out in Morocco showed that uropathogens Enterobacteriaceae were resistant to β-lactams, quinolones and Aminoglycosidees (Rafik et al., 2021; Nadmi et al., 2010; Nejjari et al., 2022) [9,17,18] . This antibiotic resistance has caused growing concern worldwide. Indeed, the World Health Organization (WHO) estimates that in 2050, this resistance will be the first cause of mortality in the world with 10 million cases against 8.2 million for cancer (Berthuin et al., 2018) [19] . To deal with this alarming figure, the WHO created the Global Antimicrobial Resistance Surveillance System (GLASS) in 2015 as a critical component of the global action plan against antimicrobial resistance (WHO, 2017) [20] . By the end of 2018, Morocco joined the GLASS system as a member, and the Ministry of Moroccan Health established the national coordination unit and the technical committee for the surveillance of antimicrobial resistance (Nejjari et al., 2022) [18] . Hitherto, however, the data on resistance to antibiotics of uropathogenic Enterobacteriaceae are very limited and needs further investigations to provide a perspective at a national level (Rafik et al., 2021) [9] . In this context, our study's aim were to describe the epidemiology of Enterobacteriaceae uropathogenic strains isolated from hospitalized and outpatients at the Clinical Laboratory of the Regional Hospital (CLRH) of Beni Mellal and to determine their resistance profile to common antibiotics.
Materials and Methods
Materials and Methods
Study area and design
This was a retrospective descriptive study, carried out in the CLRH of Beni Mellal in Morocco. It was extended for three years, from January 2020 to December 2022.
Inclusion and exclusion criteria
All positive results of Cyto Bacteriological Examination of Urine (CBEU) and antibiograms of both hospitalized and outpatient individuals, recorded in the laboratory register during the study period were included. However, any duplicate CBEU from the same patient with the same strain, polymicrobial CBEU, CBEU positive for unidentified germs, as well as any intermediate antibiogram results were excluded from the research.
Data collection
The data collected for this investigation was the patient's gender, age, hospitalization department, residence place, and examination results (CBEU and antibiogram). The laboratory register was the source of data collection for the study.
Data analysis
Statistical analysis was carried out using Sphinx Plus2 software. The χ 2 test assessed the links between the different types of data. All significant variables in the χ 2 test analysis (p<0.05) were considered.
Ethical considerations
Our study was carried out in accordance with local ethical considerations, and namely obtaining the authorizations of the Ministry of Moroccan Health and Social Protection on March 3 th 2020 (Reference Number: 6397-3/3/2020). We rigorously implemented all precautions to respect the anonymity and confidentiality of the patient's information by using a coding system.
Results
Results
Sociodemographic characteristics of patients with a positive CBEU
The results showed that out of 325 positive CBEUs performed, 63.4% were from women and 36.6% were from men, resulting in a sex ratio of 1.73 female per male. The age range of patients was 1 and 94 years old, with a mean age of 49.62±18.9 years. The most impacted age groups in women were those aged of 40 to 49 years and those aged of 60 years and over, whereas, in men, the age range most affected was 60 and over. Regarding the place of residence, 56.8% of patients came from urban areas and 43.2% from rural areas (Table 1 and Table 2).
| Age (years) | Gender | — | — | — | Total |
|---|---|---|---|---|---|
| Women | Men | ||||
| N | % | N | % | ||
| < 20 | 18 | 5.54 | 5 | 1.54 | 23 |
| 20-29 | 12 | 3.69 | 3 | 0.92 | 15 |
| 30-39 | 17 | 3.53 | 4 | 1.23 | 21 |
| 40-49 | 78 | 24 | 34 | 10.46 | 112 |
| 50-59 | 30 | 9.23 | 11 | 3.38 | 41 |
| 60 and over | 51 | 15.69 | 62 | 13.08 | 113 |
| Total | 206 | 63.4 | 119 | 36.6 | 325 |
Table text extracted from the original PDF; superscript letters are shown inline. The original table image is below.
View original table image
| Sociodemographic Characteristics | Patients | — | P-Value |
|---|---|---|---|
| N / Mean ± SD | Percentage | ||
| Gender | 0.0303 | ||
| Men | 119 | 36.6 | |
| Women | 206 | 63.4 | |
| Age | |||
| Mean age (SD) | 49.62 (18.97) | - | 0.6437 |
| < 20 | 23 | 7.08 | |
| 20-29 | 15 | 4.61 | |
| 30-39 | 21 | 6.46 | |
| 40-49 | 112 | 34.46 | |
| 50-59 | 41 | ||
| 60 and over | 113 | ||
| Residence place | |||
| Urban | 185 | 56.92 | 0.7567 |
| Rural | 140 | 43.08 |
Table text extracted from the original PDF; superscript letters are shown inline. The original table image is below.
View original table image
Bacterial isolates from UTIs
The overall prevalence of UTIs was 15.6% (325/2083).
Klebsiella:
The results of this study showed a high degree of resistance of Klebsiella strains to frequently employed β-lactam antibiotics (ampicillin (100%), amoxicillin (100%), Ticarcillin (90.48%), amoxicillin-clavulanic acid (73.81%), mecillinam (57.14%), quinolones (ciprofloxacin and nalidixic acid, respectively, 45.23% and 30.95%), sulfonamides (cotrimoxazole 47.62%), and phenicoles (chloramphenicol (35.71%)). While the lowest level of resistance was obtained with gentamicin (9.52%), ceftazidime (9.52%) and imipenem (7.14%).
Proteus mirabilis
Proteus Mirabilis strains showed 66.67% resistance to cotrimazole, 55.55% to amoxicillin and 44.44% to amoxicillin-clavulanic acid, 33.33% to nalidixic acid and 22.22% to Ticarcillin, ciprofloxacin and chloramphenicol.
Enterobacter cloacae
In general, high rates of resistance in Enterobacter cloacae were observed with β-lactams (cefalotin and Cefoxitin (62.5%), Ticarcillin (50%), amoxicillin (37.5%), and amoxicillin-clavulanic acid (25%)), quinolones (nalidixic acid 37.5%) and ciprofloxacin (25%)). However, these bacteria showed less resistant to Aminoglycosidees (gentamicin (12.5%)).
Discussion
Through our study, we were able to describe the epidemiology of Enterobacteriaceae uropathogenic strains isolated in the CLRH of Beni Mellal city. Additionally, we determined their resistance profile to common antibiotics. Our study showed that of the 2083 patients' CBEUs, the prevalence of UTIs was 16.6%. This prevalence is similar to rates observed in other countries such as Chad (17.4%), Mauritania (18.4%) and Senegal (18.5%) (Hailaji et [7,21,22] . Furthermore, 15.07% of UTIs were of nosocomial origin and 84.93% were of community origin. This finding is consistent with studies conducted by Hailaji et al. (2016) [7] and Amady et al. (2021) [5] , which reported that 82.2% and 74.9%, respectively, were UTIs of community origin. This situation can be explained by the fact that UTIs are one of the most common bacterial infections in the community (Hailaji et al., 2016; Yandai et al., 2021; Seydou, 2021; SPILF, 2015) [7,21,22,23] . The mean age of the patients with UTIs was 49.62 years old. Among women, the age range most impacted were those between 40 to 49 years old and ≥ 60 years old. Among men, the most impacted age group was those ≥ 60 years old. These findings were similar to those of Ouedraogo et al. (2022) [16] , who found that the age groups most impacted were men and aged 55 and over, and women aged between 30-45 and ≥ 55 years old. The tampons use during menstruation, which would raise the urinary tract infection risk, pregnancy, the use of contraceptives, and other occurrences may all contribute to these findings in women. Additionally, the menopausal phenomenon, which would result in a hormone flow imbalance (Lack of oestrogen) and the loss of Lactobacillus in the vaginal flora, would be associated to the high prevalence of UTIs in the age range of 60 years. For males, benign prostatic hypertrophy, or inflammation that stops the bladder from emptying fully, is assumed to be the cause of the increased prevalence of UTIs in the age range of 60 years (Ouedraogo et al., 2022) [16] . In fact, for both sexes, the high prevalence of UTIs in the age range of ≥ 60 years is associated with diminished functional autonomy and a drop in immune system effectiveness (Gaudré et al., 2019) [26] .
Among the positive CBEUs in hospitalized patients, the highest rate (51.85%) came from the surgical departments. This is different from the results of Gaudré et al. (2019) [26] , which showed that 50.2% of positive CBEUs came from the medical departments. This observation can be explained by the presence of the urology service within the surgery department of Regional Hospital of Beni Mellal. The majority of the bacteria responsible for UTIs (89.84%) were isolates of the family Enterobacteriaceae. This prevalence was similar to those reported in Madagascar (85%), in Rwanda (85.4%) and in Senegal (91.92%) (Randrianirina et al., 2007; Muvunyi Arsalane et al., 2014; Amady et al., 2021) [3][4][5] . E. coli was the predominant isolate of the Enterobacteriaceae (71.63%), followed by Klebsiella (12.92%), Proteus mirabilis (3.86%), and Enterobacter (3.43%). This epidemiological profile largely dominated by these 4 bacteria was reported by several studies that focused on UTIs (Dia et [6,7,10,11] . The high colonization of the perineum by digestive-related bacterial strains and the presence of bacterial adhesins that could attach to the urine epithelium can explain the preponderance of Enterobacteriaceae observed in our study (Ferjani et al., 2011; Larabi et al., 2003) [24,25] . Our study confirmed that E. coli remained the most common uropathogen isolated from both community-acquired and nosocomial UTIs. These findings were in agreement with similar surveillance studies (Amadyet [5,7,16,26,27,28] . The pathophysiological mechanism of UTI, which mostly occurs along the ascending route, may help to explain the high frequency of E. coli. Additionally, this bacterium was the most prevalent species in the gut flora and it is simple for it to spread to the urinary tract. Moreover, E. coli found among the faecal coliforms, making it easy for the germs to enter the urinary system when the private parts aren't cleaned properly (Ferjani et al., 2011) [24] . Analysis of the susceptibility of Enterobacteriaceae strains to β-lactams showed variable resistance level. Thus, isolated strains were in 56% resistant to ticarcillin, and to ampicillin in 51.38% of cases. Our results were similar to those of Yandai et al. (2019) [21] in Tchad and were lower to those obtained by Mouanga Ndzime et al. (2021) [28] in Gabon. These high rates of resistance may be the cause of the no longer advised use of carboxypenicillins and aminopenicillins for the probabilistic treatment of UTIs (Benhiba et al., 2015) [29] . The resistance rates of Enterobacteriaceae to amoxicillinclavulanic acid were 48%. This frequency was more than that reported in France (SPILF; 2015) [23] , which ranged between 25 and 35%. But it was compared to that of 50% recorded in Rwanda (Muvunyi Arsalane et al., 2014) [4] . The high prevalence of β-lactams resistance in Enterobacteriaceae strains is mostly a result of the synthesis of β-lactamases, which is a very efficient resistance mechanism. In fact, bacteria that make-lactamases inactivate -lactams by hydrolytic action, making this the most pervasive method of bacterial resistance to antibiotics containing a β-lactam nucleus (Livermore, 1995) [30] . In relation to this, Amady et al. (2021) [5] in their study showed that Extended Spectrum Beta-Lactamase (ESBL) production was observed in 28.3% of Enterobacteriaceae strains.
Furthermore, studies showed that Klebsiella was the bacterium most responsible for ESBL-producing. Thus, Hailaji et al. (2016) [7] and Amandy et al. (2021) [5] in their studies reported that among the ESBL-producing Enterobacteriaceae, Klebsiella accounted for 41.8% and 40.7%, respectively. This funding could explain the high resistance rates of Klebsiella strains to β-lactams: Amoxicillin and ampicillin (100%), ticarcillin (90.48%), and amoxicillin-clavulanic acid (73.81%) in our study. The resistance of Enterobacteriaceae strains to C3G ranged from 8.85 to 32.66%. Our results were compared to those of Mouanga Ndzime et al. (2021) [28] that ranged from 30 to 33% and 29.11% noted by Muvunyi et al. (2011) [27] . This resistance acquired to C3G can be related to the ability of Enterobacteriaceae strains to produce high degree of cephalosporinase (Amady et al., 2021; Gaudré et al., 2019) [5, 26] . Enterobacteriaceae were found to be resistant to cotrimoxazole in 31.69%. This prevalence was similar to these ranging between 20% and 30% noted in France (Lemort et al., 2006) [31] and were lower than 75.67% observed in Burkina Faso (Ouedraogo et al., 2022) [16] . Sulfamides' usage in the treatment plan for HIV patients' opportunistic infections would be the cause of this resistance to them. Thus, this can result in the abuse of antibiotics. In our study, we found that 29.85% and 36.31% of the Enterobacteriaceae strains examined were resistant to nalidixic acid and ciprofloxacin, respectively. These rates were in line with those of 28.6% and 40.6%, respectively, observed by Hailaji et al. (2016) [7] . The appearance of this quinolone resistance may be explained by the first-line usage of fluoroquinolones as a probabilistic therapy of UTIs in our country. In our study, imipenem was the antibiotic that was most effective against 97.14% Enterobacteriaceae strains. These results were similar to those of Ouedraogo et al. (2022) [16] who noted in their study that 91.25% of Enterobacteriaceae strains were susceptible to imipenem. To explain these lower resistance rates, Amandy et al. (2021) [5] reported in their study that only 3.2% of Enterobacteriaceae strains produced the carbapenemase. Aminoglycoside activity was conserved across all Enterobacteriaceae. Therefore, 7.69% of strains were resistant to gentamicin (8.58% for E. coli, 9.52% for Klebsiella, 12.5% for Enterobacter cloacae and 0% for Proteus mirabilis). The resistance to Aminoglycoside observed in our study was compared to these of 14% reported in Mauritania (Hailaji et al., 2016) [7] and 8-14% reported in Morocco (Muvunyi Arsalane et al., 2014) [4] . The apparently preserved efficacy of Aminoglycoside could be explained by their parental administration limiting use. Generally, the highest rates of resistance of Enterobacteriaceae strains to antibiotics observed in our study can be explained by the fact that in our country, the CBEU which is the only element of diagnosis of certainty is only rarely requested in case of suspected UTIs. Afterwards, probabilistic treatment of UTIS is an approach adopted in medical practice. Indeed, Beni Mellal Khénifra region is among the poorest regions in Morocco and most people can only afford generic drugs. Moreover, self-medication is also a common practice of our patients. These factors, among others, led to a strong emergence and dissemination of multi-resistant bacteria.
Study Limitations
This study was retrospective and we did not monitor the urine samples or the progress of the microbiological tests (CBEU and antibiograms) However, we limited ourselves to the data reported in the laboratory register. Our results do not apply to the whole population as our study was conducted in a single hospital center in Morocco.
Conclusion
The study found that the most often implicated bacteria types in UTIs, Enterobacteriaceae, continue to exhibit significant levels of resistance to β-lactam, quinolone, and sulfamide. Our study's findings may help policymakers take steps to curb the spread of resistant bacteria and lower the frequency of urinary tract infections. The best approaches to preventing this phenomenon are antibiotic susceptibility testing before treating patients, compliance with antibiotic prescriptions, and promoting public awareness to discourage self-medication at health center level.
Figures and tables from the paper
| Bacteria strains (N=325) | Isolated bacteria | No. of isolates | — | Total |
|---|---|---|---|---|
| Nosocomial strains | Community strains | |||
| N (%) | N (%) | N (%) | ||
| Enterobacteriaceae (N =292) | E. coli | 33 (14.16) | 200 (85.84) | 233 (71.63) |
| Klebsiella | 8 (19.05) | 34 (80.95) | 42 (12.92) | |
| Proteus mirabilis | 1 (11.11) | 8 (88.89) | 9 (2.76) | |
| Enterobacter cloacae | 2 (25) | 6 (75) | 8 (2.46) | |
| Gram-positive cocci (N =24) | Staphylococci | 7 (2.15) | 9 (2.77) | 16 (4.92) |
| Enterococci | 1 (031) | 3 (0.92) | 4 (1.23) | |
| Streptococcus | 0 (0) | 4 (1.23) | 4 (1.23) | |
| Non-fermentation Gram-negative bacilli (N=9) | Pseudomonas | 3 (0.92) | 4 (1.23) | 7 (2.15) |
| Acinetobacter baumannii | 0 (0) | 2 (0.61) | 2 (0.61) | |
| Total | 55 (16.92) | 270 (83.08) | 325 |
Table text extracted from the original PDF; superscript letters are shown inline. The original table image is below.
View original table image
| Inpatient services | Positive CBEU | — |
|---|---|---|
| N | % | |
| Surgery | 28 | 51.85 |
| Medicine | 11 | 20.37 |
| Maternity | 9 | 16.67 |
| Pediatric | 6 | 11.11 |
| Total | 54 | 100 |
Table text extracted from the original PDF; superscript letters are shown inline. The original table image is below.
View original table image
| Antibiotic tested | E. coli (N=233) | Klebsiella (N=42) | Proteus mirabilis (N=9) | Enterobacter cloacae (N=8) | Total (N=325) |
|---|---|---|---|---|---|
| RN (%) | RN (%) | RN (%) | R N (%) | RN (%) | |
| INN | 92 (39.48) | 24 (57.14) | 0 (0) | 0 (0) | 116 (35.69) |
| AML | 154 (66.09) | 42 (100) | 5 (55.56) | 3 (37.5) | 196 (60.31) |
| AUG | 119 (51,07) | 31 (73.81) | 4 (44.44) | 2 (25) | 156 (48) |
| TCC | 138 (59.23) | 38 (90.48) | 2 (22) | 4 (50) | 182 (56) |
| CF | 118 (50.64) | 16 (38.10) | 0 (0) | 5 (62.5) | 139 (42.77) |
| FOX | 90 (38.63) | 11 (26.12) | 0 (0) | 5 (62.5) | 106 (32.66) |
| AM | 125 (53.65) | 42 (100) | 0 (0) | 0 (0) | 167 (51.38) |
| CTR | 32 (13.73) | 0 (0) | 0 (0) | 0 (0) | 32 (9.85) |
| CAZ | 36 (15.45) | 4 (9.52) | 0 (0) | 1 (12.5) | 41(12.61) |
| IMP | 5 (2.15) | 3 (7.14) | 0 (0) | 0 (0) | 8 (2.46) |
| NA | 78 (3.48) | 13 (30.95) | 3 (33.33) | 3 (37.5) | 97 (29.85) |
| CIP | 95 (40.77) | 19 (45.24) | 2 (22) | 2 (25) | 118(36.31) |
| OFX | 123 (52.79) | 0 (0) | 0 (0) | 0 (0) | 131 (40.31) |
| SXT | 77 (33.05) | 20 (47.62) | 6 (66.67) | 0 (0) | 103 (31.69) |
| C | 28 (12.02) | 15 (35.71) | 2 (22) | 0 (0) | 45 (13.85) |
| GN | 20 (8.58) | 4 (9.52) | 0 (0) | 1 (12.5) | 25 (7.69) |
| CS | 22 (9.44) | 0 (0) | 9 (100) | 0 (0) | 31 (9.54) |
Table text extracted from the original PDF; superscript letters are shown inline. The original table image is below.
View original table image
References
28 in the original paper- Chervet D, Lortholary O, Zahar JR, Dufougeray A, Pilmis B, Partouche H. Antimicrobial resistance in community-acquired urinary tract infections in Paris in 2015. Medecine et Maladies Infectieuses. 2018;48(3):188-192.
- Bertholom C. Épidémiologie des infections urinaires communautaires et nosocomiales. Option/Bio. 2016;27(541-542):23-24.
- Randrianirina F, Soares JL, Carod JF, Ratsima E, Thonnier V, Combe P, et al. Antimicrobial resistance among uropathogens that cause community-acquired urinary tract infections in Antananarivo, Madagascar. Journal of Antimicrobial Chemotherapy. 2007;59(2):309-312.
- Muvunyi Arsalane L, Kamouni Y, Yahyaoui H, Bennouar N, Berraha M, Zouhair S. Profil actuel de résistance aux antibiotiques des souches d'Escherichia coli uropathogènes et conséquences thérapeutiques. Progrès en urologie. 2014;24(16):1058-1062.
- Amady SY, Oumar DIOP, Mbodji M, Faye M, Faye FA, Ndiaye F, et al. Profil de résistance aux bêtalactamines des entérobactéries uropathogènes isolées dans le laboratoire de biologie médicale du Centre Hospitalier Régional de Thiès. Revue Africaine de Médecine Interne. 2021;8(1):39-47.
- Dia ML, Chabouny H, Diagne R. Profil antibiotypique des bactéries uropathogènes isolées au CHU de Dakar. Revue Africaine d'Urologie et d'Andrologie. 2015;1(4):212-217.
- Hailaji NSM, Salem MO, Ghaber SM. La sensibilité aux antibiotiques des bactéries uropathogènes dans la ville de Nouakchott-Mauritanie. Progrès en Urologie. 2016;26(6):346-352.
- Linhares I, Raposo T, Rodrigues A, Almeida A. Frequency and antimicrobial resistance patterns of bacteria implicated in community urinary tract infections: A ten-year surveillance study (20002009). BMC Infections Diseases. 2013;13:1-14.
- Rafik A, Abouddihaj B, Asmaa D, Kaotar N, Mohammed T. Antibiotic resistance profiling of Uropathogenic Enterobacteriaceae. EDP Sciences. 2021;319:01002.
- Sekhsokh Y, Chadli M, El Hamzaoui SA. Fréquence et sensibilité aux antibiotiques des bactéries isolées dans Les urines. Médecine et Maladies Infectieuses. 2008;38(6):324-327.
- Seynabou LO. Sensibilité aux antibiotiques des Entérobactéries isolées d'urines au Centre Hospitalier Régional de Saint Louis (Sénégal) de juin 2011 à juillet 2012. Revue Africaine et Malgache de Recherche Scientifique/Sciences de la Santé. 2015;2(2):25-28.
- Elhani D. Les bêta-lactamases à spectre étendu: Le défi s'accentue. Annales de Biologie Clinique. 2008;70(2):117-140.
- Gupta K, Scholes D, Stamm WE. Increasing prevalence of antimicrobial resistance among uropathogens causing acute uncomplicated cystitis in women. JAMA. 1999;281(8):736-738.
- Kahlmeter G, Menday P. Cross-resistance and associated resistance in 2478 Escherichia coli isolates from the Pan-European ECO• SENS Project surveying the antimicrobial susceptibility of pathogens from uncomplicated urinary tract infections. Journal of Antimicrobial Chemotherapy. 2003;52(1):128-131.
- Ouedraogo S, Kpoda DS, Ouattara LP, Zongo C, Hien YE, Karfo P. Identification of Bacteria Strains Isolated in Urinary Tract Infections and Their Antibiotic Susceptibility at the National Public Health Laboratory, Ouagadougou. Open Journal of Medical Microbiology. 2022;12(3):83-95.
- Nadmi H, Elotmani F, Talmi M, Zerouali K, PerrierGros-Claude JD, Timinouni, M. Profil de résistance aux antibiotiques des entérobactéries uropathogènes communautaires à El Jadida (Maroc). Médecine et Maladies Infectieuses. 2010;40(5):303-305.
- Nejjari C, El Achhab Y, Benaouda A, Abdelfattah C. Antimicrobial resistance among GLASS pathogens in Morocco: An epidemiological scoping review. BMC Infectious Diseases. 2022;22(1):438.
- Berthuin J, Miras M, France BPI. La résistance aux antibiotiques: Un enjeu de santé publique et économique. Bpi France. Servir l'avenir; 2009;42(9):621.
- Tornimbene, Barbara, et al. "Global Antimicrobial Resistance and Use Surveillance System on the African continent: Early implementation 2017-2019." African Journal of Laboratory Medicine. 2022;11(1):1-11.
- Yandai FH, Ndoutamia G, Nadlaou B, Barro N. Profil de prévalence et de résistance d'Escherichia coli et Klebsiella pneumoniae isolés d'infections urinaires à N'Djamena, Tchad. Journal International Des Sciences Biologiques Et Chimiques. 2019;13:2065-2073.
- Ferjani A, Mkaddemi H, Tilouche S, Marzouk M, Hannechi N, Boughammoura L, et al. Caractéristiques épidémiologiques et bactériologiques des bactéries uropathogènes isolées dans un milieu pédiatrique. Archives de Pédiatrie. 2011;18(2):230-234.
- Larabi K, Masmoudi A, Fendri C. Étude bactériologique et phénotypes de résistance des germes responsables d'infections urinaires dans un CHU de Tunis: A propos de 1930 cas. Médecine et Maladies Infectieuses. 2003;33(7):348-352.
- Gaudré N, Drame BS, Poudiougo A, Kassogué A, Koné H, Diarra A. Profil de résistance aux bêta-lactamines des entérobactéries isolées des prélèvements urinaires à l'Hôpital du Mali. 2019;14(2):06-13.
- Muvunyi CM, Masaisa F, Bayingana C, Mutesa L, Musemakweri A, Muhirwa G. Decreased susceptibility to commonly used antimicrobial agents in bacterial pathogens isolated from urinary tract infections in Rwanda: Need for new antimicrobial guidelines. The American Journal of Tropical Medicine and Hygiene. 2011;84(6):923.
- Mouanga Ndzime Y, Onanga R, Kassa Kassa RF, Bignoumba M, Mbehang Nguema PP, Gafou A, et al. Epidemiology of community origin Escherichia coli and Klebsiella pneumoniae uropathogenic strains resistant to antibiotics in Franceville, Gabon. Infection and Drug Resistance. 2021;14:585-594.
- Benhiba I, Bouzekraoui T, Zahidi J. Epidémiologie et antibio-résistance des infections urinaires à entérobactérie chez l'adulte dans le CHU de Marrakech et implication thérapeutique. Revue africaine d'urologie et d'andrologie. 2015;1(4):166-171.
- Livermore DM. Beta-Lactamases in laboratory and clinical resistance. Clinical Microbiology Reviews. 1995;8(4):557-584.
- Lemort ML, Neuville S, Medus M, Gueudet P, Saada M, Aumaître H, et al. Évolution en 2002 et 2004 à l'hôpital de Perpignan. Pathologie Biologie. 2006;54(89):427-30.
Cited by 7
From OpenAlex, OpenCitations and reference lists read by Scinovex
- Microbiological characterization and multidrug resistance mechanisms of uropathogenic enterobacteriaceae isolated from clinical laboratory samples in Beni Mellal, Morocco ↗
Omar Haddad Cherkaoui, Meriem Sabri Kettani, Loubna Bouzid Fassi · Journal of Advances in Microbiology Research · 2026
❝ 0Found by Scinovex - Periodic monitoring of etiological agents of UTI and their resistant pattern against broad spectrum antibiotics in tertiary care Hospital ↗
Shivani Choubey, Shadma Siddiqui · Journal of Advances in Microbiology Research · 2025
Aim: To identify most common microorganisms causing UTI and the percentages of all highly resistance antibiotics.Objectives 1.To find out the most common resistant groups of antibiotics.2. To find out the most common microorganisms causing UTI.In current scenario what kind of antibiotics are working in UTI patient in tertiary care hospital.Introduction: Urinary tract infection is a very common infection in both
- Vector-borne transmission pathways and ecological reservoirs of uropathogenic Enterobacteriaceae strains in community and hospital environments of central Morocco ↗
Yassine Rhazi Benmoussa, Siham Aouane Benali, Abderrahim Lazrak Boukili · Journal of Entomology and Zoology Studies · 2025
Background: The dissemination of uropathogenic Enterobacteriaceae (UPE) beyond clinical settings into community and environmental reservoirs represents an understudied but critical dimension of the global antimicrobial resistance crisis. In Central Morocco, vector-borne transmission pathways and ecological reservoir dynamics may substantially contribute to the community burden of drug-resistant UPE. Objective: To identify and characterise the vector-borne transmission pathways and ecological reservoir types
- Prevalence and antimicrobial resistance profiles of uropathogenic Enterobacteriaceae isolated from urinary tract infection patients at a regional hospital in Beni Mellal, Morocco ↗
Nadia Ouali Hassani, Khalil Bourass Filali · International Journal of Medicine Sciences · 2025
Background: Urinary tract infections (UTIs) caused by Enterobacteriaceae present an escalating antimicrobial resistance challenge worldwide, with limited epidemiological data from Moroccan regional hospitals hampering effective therapeutic management. Objective: To determine the prevalence, distribution, and antimicrobial resistance profiles of uropathogenic Enterobacteriaceae (UPE), with emphasis on ESBL-producing and multidrug-resistant (MDR) strains, at the Regional Hospital of Beni Mellal, Morocco. Methods: A prospective
- Epidemiological trends of antibiotic-resistant uropathogenic enterobacteriaceae in hospital settings: A comprehensive academic review with reference to Moroccan clinical laboratories ↗
Imane Benkiran Alaoui, Rachid Guenbour Benkirane, Souad Tazi El Andaloussi · International Journal of Advanced Academic Studies · 2025
Background: Antimicrobial resistance among uropathogenic Enterobacteriaceae (UPE) is a critical and worsening public health challenge in hospital settings worldwide. In Morocco, the convergence of unregulated antibiotic access, inadequate clinical laboratory infrastructure at regional levels, and the absence of a consolidated national resistance surveillance framework has accelerated resistance trends among uropathogens. Objective: This comprehensive review aimed to synthesise and critically analyse
- Urinary tract infections and antimicrobial resistance: Across sectional study ↗
Ehab Jasim Mohammad, Waleed K. Mohammed, Waleed Nassar Jaffal · International Journal of Surgery Science · 2024
Background: Urinary infections are important microbial diseases common worldwide. Besides, the growth of antibiotic resistance is an ongoing concern for community health, especially in low-income countries. Therefore, this study aimed to identify common urinary pathogens and antibiotic sensitivity pattern in some cases of urinary tract infection (UTI) in Baghdad, the capital of Iraq. Methods: A total of 289 participants with
- Antibiotic sensitivity profiles of uropathogenic E. coli: A prevalence study in UTI patients ↗
Mahmud Javed Hasan, Md. Mahmudul Mujib Ovi · International journal of nephrology research. · 2024
Background: Urinary tract infections (UTIs) are a major global public health problem with Escherichia coli (E. coli) as the most common uropathogen. The issue of antibiotic resistance strains is a major factor that complicates the management of UTI, especially in countries such as Bangladesh. Objective: To assess the proportion of total UTIs due to E. coli and antibiotic susceptibility patterns