
Research article · 2020 · Full text
International Journal of Statistics and Applied MathematicsA Bayesian approach to compare the effect of three drugs used to treat children suffering from malaria
Volume 5(2) · Pages 89–94
Research areasDiverse Scientific Research Studies
Abstract
Author-writtenThe world today has evolved with many and new inventions in areas of medical research. Various drugs have been generated to cure various ailments like Malaria, HiV/Aids, TB, Cholera, Typhoid, Ebola, Hepatitis, Diabetes, Cancer, and Hypertension among others. The treatment for various ailments ranges from a single drug to even five drugs for a particular ailment. The acceptance of a particular drug depends on the efficacy of a particular drug as compared to others. This results to their recommendation by world bodies like World Health Organization for their use among the world population. The study therefore sought to find out among the three treatments administered to children suffering from malaria, which treatment had a longer delay period to the recurrence of Malaria namely; Artesunate (ART), Quinine (QN) and Coartem (AL). This was done by identifying three different groups who were administered the different treatments and applying the survival analysis models on the data. Data was analyzed using R Programming and Advanced Excel Simulation.The results on the efficacy of the three treatments showed Artesunate was more efficacious. The difference in Delay time between Artesunate and Quinine was 3.37 days and between Artesunate and Coartem was 6.59 days. The difference in delay time between Quinine and Coartem was 3.22 days. In all the cases, the difference in delay time for Artesunate was positive in comparison with Quinine and Coartem treatments.
Summary
Source-checkedPlain-language reading of the full paper, prepared with AI and checked against the text. Each point links to the authors' own words.
Why it matters
- Malaria is a deadly vector-borne disease that significantly impacts populations in Africa and many Asian countries. View evidence ↗
- While Artemisinin-based combination therapies (ACTs) are known to be effective, there is a lack of detailed modeling on how long these treatments delay the recurrence of malaria if the initial treatment fails. View evidence ↗
The question
- The study aimed to determine which of three drugs, Artesunate (ART), Quinine (QN), or Coartem (AL), provided the longest delay before malaria recurred in children. View evidence ↗
What they did
- The researchers analyzed data from a 2007 clinical trial at Coast General Hospital involving 138 children under five years of age. View evidence ↗
- The analysis evaluated two distinct timeframes: a 42-day period and an 84-day period. View evidence ↗
- The data analysis was performed using R Programming and Advanced Excel Simulation. View evidence ↗
What they found
- Within the 42-day period, the mean delay time to recurrence was longest for Artesunate (31.20 days), followed by Quinine (27.83 days) and Coartem (24.61 days). View evidence ↗
- Within the 84-day period, Artesunate again showed the longest mean delay time (26.18 days), compared to Quinine (23.01 days) and Coartem (21.85 days). View evidence ↗
- A logrank test (p < 0.05) indicated that there is a statistically significant difference in survival times among the three drugs. View evidence ↗
- A Wilcoxon test confirmed a significant difference in survival times specifically between Artesunate and Coartem. View evidence ↗
- The Wilcoxon test found insufficient evidence to conclude a significant difference in survival times between Artesunate and Quinine. View evidence ↗
- The Wilcoxon test found insufficient evidence to conclude a significant difference in survival times between Quinine and Coartem. View evidence ↗
- Artesunate showed a positive difference in delay time compared to Quinine (3.37 days) and Coartem (6.59 days), while the difference between Quinine and Coartem was 3.22 days. View evidence ↗
What it means
- The authors conclude that Artesunate is the most efficacious of the three treatments for delaying malaria recurrence. View evidence ↗
- The authors note that discrepancies in the Wilcoxon test results may have been caused by a lack of observations at certain treatment stages or variations in the children's immune systems. View evidence ↗
Figures & tables
From the original paper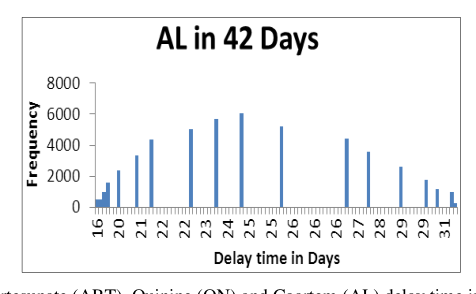 Figure 5
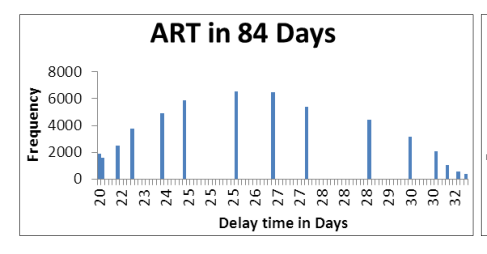 Figure 5
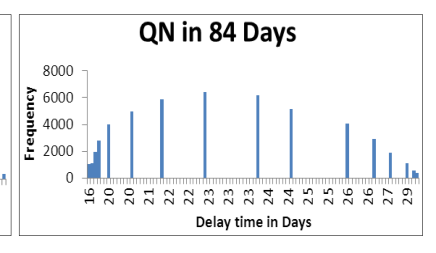 Figure 5
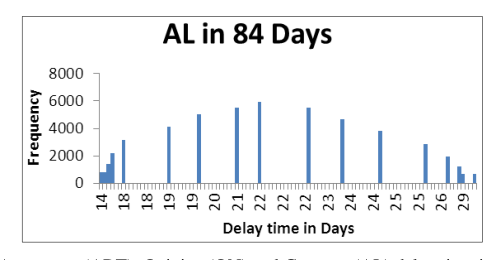 Figure 6
Introduction
In clinical research, the choice of a model to represent a natural phenomenon is not made solely on mathematical grounds but by knowing something about biology, medicine and other disciplines. Survival models are usually triggered by observations from clinical trials or data resulting from other forms of experiments. Clinical trials often lead to time-to-event (survival) data leading to time-to-event analysis known as survival analysis. According to Woodworth (2004) [17] Bayesian methods have become quite popular in modelling survival data. The attractiveness of this technique is the easy interpretation of results and the drawing of conclusions. Information from previous studies can easily be incorporated through an informative prior distribution. In the absence of tangible prior information, Bayesian techniques are applied using vague priors that often yield results similar to classical maximum likelihood methods. In Africa and many Asian countries Malaria is a vector-borne killer disease that is taking the lives of many who live in the infested zones. Transmission of malaria is mainly through infected parasites mainly mosquitoes from one infected person to uninfected person. Treatment of malaria is done by drugs which have been recommended by WHO. Research is on the increase towards getting the best combination therapy that will cure and reduce resistance. Many studies have concluded that ACTs are better treatment therapies in terms of efficacy in treatment of malaria, but in exactly how long the therapies delay reinfection or recrudescence in case of failure has not been given the desired attention in modelling. Some related works in this direction only based their studies on measuring parasitaemia over predefined periods to determine the levels of parasite clearance in the host's system. Many treatment therapies have not been able to obtain a desirable model for determining how long the therapies can delay reinfection or recrudescence in case of failure. Currently no study has been undertaken to determine the efficacy of the three malaria treatments namely: Artesunate (ART), http://www.mathsjournal.com
x Quinine(QN) and Coartem(AL) which are used as third line, second line and first line respectively in the treatment of Malaria. Hence, this research work sought to propose a method to determine which of the three treatments among Artesunate, Quinine and Coartem is more efficacious on malaria treatment, and present a new methodology using statistical models that can be used to estimate how long a treatment can postpone the recurrence of the disease in case of failure.
Methodology 2.1. Study Area
This study focused on three groups of children who were suffering from malaria who were administered the three drugs under study namely; Artesunate, Quinine and Coartem at Coast General Hospital. Their responses to the three was measured to determine which of the three treatments eliminated all the parasites in their blood. R programming and advanced excel simulation was used to analyze the data.
Description of Data
The source of the data was from a clinical trial conducted at Coast General Hospital in the year 2007 to compare the efficacy of the three drugs used in treatment of Malaria in children under five years. The study was done with a total of 138 patients. Children enrolled in these trials were randomly assigned to receive either of these drugs. The children had to meet certain entry requirements; the most important one is having malaria with no other complications and willing to participate in the study. The children were tested again for malaria at days 7,21,28,42 and 84 after the treatment. We made a major assumption that the number of patients who were diagnosed as sick again was due to recrudescence (temporary suppression) and not new infection. We considered two study periods; a period that starts from day 0 to day 42 and the other period that starts from day 0 to 84. The choice of these two periods was motivated by the fact that some clinical trials do last for 42 days, while others do last for 84 days. This is because in the medical field, within 42 days, the effect of the most long-lasting drugs (long elimination half-life) must have become negligible so that most suppressed recrudescence should have had the opportunity to reappear. Meanwhile the 84 days period is to explore if or ensure that the foregoing assumption was correct. We used t max =42 days, since other studies have consistently used that, and 84 days, since there seems to be many cases of recrudescence also after day 42. Some patients never experienced a recurrence of Malaria throughout the study periods. This is the category we considered as having been successfully treated by the drug they received. There were six designated intervals to monitor Malaria symptoms during the whole period of trial to the patients. The interval lengths between the follow-up time are not of equal length. Moreover, intervals between the follow-ups and the duration of trials depend on the nature of the disease under study and should last as long as the duration of the treatment requires. Our methodology takes care of this by assuming that such equidistant points lie on lines joining other adjacent known recurrence rate points. This knowledge provides us with the necessary information for obtaining the conditional survival probability estimates for surviving up to the given time points. The delay time model is conditioned on no first recurrence beyond time t max (the end of the follow up).
Study Models 2.2.1
Cure Rate Model-Let ni, be the number at the start receiving treatment i and let xi be the random variable describing the number of cured patients (without malaria before time tmax, the end of the follow-up). Then the cure rate model is given by xi ~Bin (ni, Πi), where i = ART, QN or AL and Πi is the probability to be cured by treatment i for i = 1, 2 or 3 (type of drug). Then P (x/Π) =( 𝑛 𝑥 ) Π x (1 -Π) n-x ; for x = 0, 1, 2, 3 n.
Recurrence Rate Model at Each Follow-up
Next, suppose that rescreening to determine the presence or absence of the disease was done at fixed time points, t0 =0, t1 ,…, t k = t max where these time points are the same for the three treatments. Let R j , i and Y j , i denote the number of children who had been free from malaria up to time point t j-1 and those who get malaria between time points t j-1 and t j ( i = 1 , 2 or 3), respectively. In particular we have that R j , i + Y j , i = R j-1 ,i . Then for each of these intervals, the children Y j , i witnessing the event of interest can be modelled as: Y j , i ~Bin( R j , Q ji ) where Q ji stands for the conditional probability of becoming sick in this interval for those who have not had any recurrence at or before time t j-1 . Immediately a child witnesses a first recurrence of malaria at any time point, she was censored and no longer considered to be at risk of recurrence for the rest of the time. In the same way as in equation ( 1), the posterior distribution of Q ji is: Beta( α ji + Y j , i , β ji + R j-1 -Y j , i ) , if the prior is Beta distribution with hyperparameters α ji and β ji . We also assume that all binomial distributions and priors are independent for different intervals and treatments. Hence, we equally use the Jeffreys prior, α = β =1/2. for all intervals and all treatments.
3 Survival Rate Model at Each Follow-up
Let the rate of positive response for j th individual be defined as 𝑛𝑗 𝑟𝑗 Then the survival probability (negative response) for j th individual receiving treatment is given by 1-
𝑛𝑗 𝑟𝑗
The survival model at all follow-up time instances for each treatment is given by S ^ ( t j ) = ∏ j k=1 ( 1-
𝑛𝑗 𝑟𝑗
) . Where k represents fixed time points as illustrated by a product limit estimator. The posterior survival probability for Q ji is then S ^ ( t j ) = ∏ k=1 j ( 1-Q ki ) . Where our major assumption is that those who get recurrence between t j-1 and t j at the average get a recurrence at the midpoint of t j-1 + t j /2.
Difference in Delay Time to First Recurrence
Let the random variable T represents the survival time until first recurrence of the disease. Then the survival function is given by: S(t ) =1-F( t ) = ∫t ∞ f( s ) ds. The mean survival time for T with probability density function f (s) is defined as E( T ) =t ∫ 0 ∞ f( s ) ds = ∫ 0 ∞ S( s ) ds . This mean time is given by the area under the survival function.
The test statistics a)
The logrank test statistic used to compare the three drugs Logrank(L)= U T L V -1 ul U L X 2 (d.f=2 ) b) The wilcoxon test statistic between two drugs = 𝑈𝑤2 𝑉𝑤
Results and discussions 3.1 Survival plots
The survival plots are presented in Figure 1 to 2. At the start of the trial, the treatments had equal survival probability of 1, of escaping the event of first recurrence of malaria. These plots show a steady decrease in survival probabilities through the length of study period. We observed more often the plots for Artesunate is above those of Quinine and Coartem which is an indication of its ability to resist a recurrence of the disease. Next, figure 3 and4 represents the truncated survival plots S * (t max) =0. These were the resulting plots obtained when we impose the condition that if a first recurrence is to occur, this must take place within a specified time before the end of each trial period which was within 42 days and within 84 days. These truncated survival plots are important if we are to correctly estimate the posterior distribution of the difference in survival times bearing in mind that it is usually difficult to keep track of events after the trials.
Delay time to Recurrence
The maximum mean delay time by simulation for the three drugs within 42 and 84 days was given by figure 5 and figure 6 respectively. The mean delay time in 42 days for Artesunate, Quinine and Coartem was 31.20, 27.83 and 24.61 days respectively. While their variances for the same period was 9.95, 10.73 and 12.25 days respectively. For 84 days, the mean delay time for Artesunate, Quinine and Coartem was 26.18, 23.01 and 21.85 days respectively. While their variances for the same period was 9.75,10.21 and 12.10 days respectively. The posterior histograms obtained, were fairly Gaussian with great overlapping within the 42 days. We therefore assumed normality in delay time for the mean delay time and the variance for the three treatments.
=2.13
At at α =0.05 and d.f=1 , the chisquare value =3.841 , hence 2.13<3.841 Decision: We do reject the null hypothesis and conclude that there is no sufficient evidence to conclude that the drugs have different survival times.
Conclusion
The researcher has proposed a new methodology that can be used to estimate of how long one of the drugs can postpone or delay the recurrence of a disease using Bayesian approach. The methodology has been applied to data on efficacy of three treatments in a clinical trial. Although we used the malaria data with three treatments, the methodology can be extended to other similar studies. The difference in survival times for the three drugs is confirmed with the logrank test statistic for the three treatments. However, we observed some discrepancies in the results for wilcoxon test statistic between Artesunate and Quinine and between Quinine and Coartem. This might have been due to the scarcity of observation in some stages of treatment or difference in immune system of children which might have contributed to prolonged time to recurrence. The results on the efficacy of the three treatments showed Artesunate was a better treatment. The difference in Delay time between Artesunate and Quinine was 3.37 days and between Artesunate and Coartem was 6.59 days. The difference in delay time between Quinine and Coartem was 3.22 days. In all the cases, the difference in delay time for Artesunate was positive in comparison with Quinine and Coartem treatments. This is a major benefit and contribution to existing knowledge on the efficacy of malaria treatments research studies.
References
19 in the original paper- Chin R, Lee BY. Principles and practice of clinical trial medicine. Academic Press, 2008.
- Fisher LD. Comments on: Bayesian and frequentist analysis and interpretation of clinical trials. Control Clinical Trials. 1996; 17(5):423-34. http://dx.doi.org/10.1016/S0197-2456 (96)00043-8.
- Freedman L. Bayesian statistical methods. 1996; 313(7057):569-70.
- Gelman A, Carlin JB, Stern HS, Rubin DB. Bayesian data analysis. Chapman & Hall/CRC, 2003.
- Greenhouse B, Dokomajilar C, Hubbard A, Rosenthal PJ, Dorsey G. Impact of transmission intensity on the accuracy of genotyping to distinguish recrudescence from new infection in antimalarial clinical trials. AAC. 2007; 51(9):3096-103.
- Gbotosho GO, Okuboyejo TM, Happi CT, Sowunmi A. Recrudescent Plasmodium falciparum infections in children in an endemic area following artemisinin-based combination treatments: Implications for disease control. Asian Pac J Trop Dis. 2011; 1(3):195-202. http://dx.doi.org/10.1016/S2222-1808(11)60027-3.
- Kum CK. Bayesian analysis of two malaria treatments and probability modeling of malaria parasite genotypes, PhD Thesis, Stockholm University, Canada, 2009.
- Kum CK, Thorburn D, Ghilagaber G, Gil P, Björkman A. A Nonparametric Bayesian Approach to Estimating Malaria Prophylactic Effect After Two Treatments. Lifescience Global, 2013.
- Lesaffre E, Lawson AB. Introduction to Bayesian Inference. Bayesian Biostatistics, 2012, 122-124.
- Mutabingwa TK. Artemisinin-based combination therapies (ACTs): Best hope for malaria treatment but inaccessible to the needy. Acta Trop. 2005; 95(3):305-15. http://dx.doi.org/10.1016/j.actatropica.2005.06.009
- Mårtensson A, Strömberg J, Sisowath C, Msellem MI, Gil JP, Montgomery SM, et al, Efficacy of artesunate plus amodiaquine versus that ofartemether-lumefantrine for the treatment of uncomplicated childhood Plasmodium falciparum malaria in Zanzibar, Tanzania. Clin Infect Dis. 2005; 41(8):1079-86. http://dx.doi.org/10.1086/444460.
- Sowunmi A, Adewoye EO, Gbotosho GO, Happi CT, Sijuade A, Folarin OA et al, Factors contributing to delay in parasite clearance in uncomplicated falciparum malaria in children. Malar J. 2010; 9:53. http://dx.doi.org/10.1186/1475-2875-9-53.
- Spiegelhalter DJ, Abrams KR, Myles JP. Bayesian approaches to clinical trials and health-care evaluation. Wiley, 2004, 13.
- Spiegelhalter DJ, Freedman LS, Parmar MKB. Bayesian approaches to randomized trials. J Roy Statist Soc Ser A, 1994, 35716.
- Von Seidlein L, Milligan P, Pinder M, Bojang K, Anyalebechi C, Gosling R et al. Efficacy of artesunate plus pyrimethaminesulphadoxine for uncomplicated malaria in Gambian children: a double-blind, randomised, controlled trial. Lancet. 2000; 355(9201):352-57.
- Woodworth GG. Biostatistics: A Bayesian Introduction, Wiley-Interscience, 2004, 499.
- White NJ. The parasite clearance curve. Malar J, 2011; 10(1):278.
- Zhong M, Hess KR. Mean Survival Time from Right Censored Data. Collection of Biostatistics Research Archives-bepress, 2009.
- Zwang J, Olliaro P, Barennes H, Bonnet M, Brasseur P, Bukirwa H et al. Efficacy of artesunate-amodiaquine for treating uncomplicated falciparum malaria in sub-Saharan Africa: a multi-centre analysis. Malar J. 2009; 8(1):203. http://dx.doi.org/10.1186/1475-2875-8-203.